Related Experiment Video
Updated: Feb 12, 2026


Laparoscopic Non-Mesh Cerclage Pectopexy for Pelvic Organ Prolapse
Published on: September 13, 2022
Postoperative urinary retention after pelvic organ prolapse repair: Vaginal versus robotic transabdominal approach
Junchan J Yune1, Julie W Cheng1, Hillary Wagner1
1Department of Urology, Loma Linda University, Loma Linda, California.

Aims:
Postoperative urinary retention has been reported in 13-32% of patients that undergo pelvic organ prolapse (POP) repair. The purpose of our study was to compare rates of urinary retention between transvaginal and robotic transabdominal approaches and identify risk factors for postoperative urinary retention following POP repair.
Methods:
Medical records of patients that underwent POP repair were reviewed. Surgeries included transvaginal high uterosacral ligament suspension (HUSLS) and robotic-assisted sacral colpopexy (RASCP). All patients underwent a retrograde fill voiding trial (RGVT) postoperatively. Demographics, comorbidities, preoperative urodynamic findings, and surgical procedures were compared between women that passed their RGVT and those that did not.
Results:
Out of 484 patients reviewed, 333 underwent POP repair with a transvaginal HUSLS and 151 underwent RASCP. Postoperative urinary retention was identified in 128 (26.4%) patients where 113 underwent transvaginal HUSLS and 15 underwent RASCP. The odds ratio (OR) of postoperative urinary retention following transvaginal HUSLS was 3.26 (CI 1.72-6.18; P < 0.001) compared to RASCP. Older age was also a risk factor for postoperative urinary retention (OR 1.03, CI 1.01-1.05; P = 0.012). While parity, preoperative post-void residual (PVR), and rates of concomitant transvaginal anterior/posterior repair were significantly higher in patients that developed postoperative urinary retention on univariate analysis, these factors did not demonstrate significance on multivariate analysis.
Conclusions:
Transvaginal HUSLS demonstrates a 3.26 OR for postoperative urinary retention compared to the robotic transabdominal approach. Older age is also a significant risk factor whereas parity, preoperative PVR, and rates of concomitant transvaginal anterior/posterior repair were not significant risk factors on multivariate analysis.
More Related Videos
 03:49
Anogenital Distance and Perineal Measurements of the Pelvic Organ Prolapse POP Quantification System
Published on: September 20, 2018
 07:41
Quantification of Levator Ani Hiatus Enlargement by Magnetic Resonance Imaging in Males and Females with Pelvic Organ Prolapse
Published on: April 17, 2019
Related Concept Videos
 01:36
Mismatch Repair
 02:25
Overview of DNA Repair
Chemically...
 01:27
Mitral Valve Prolapse I: Introduction
 01:54
Base Excision Repair
The first step of...
 01:08
Nucleotide Excision Repair
 01:26
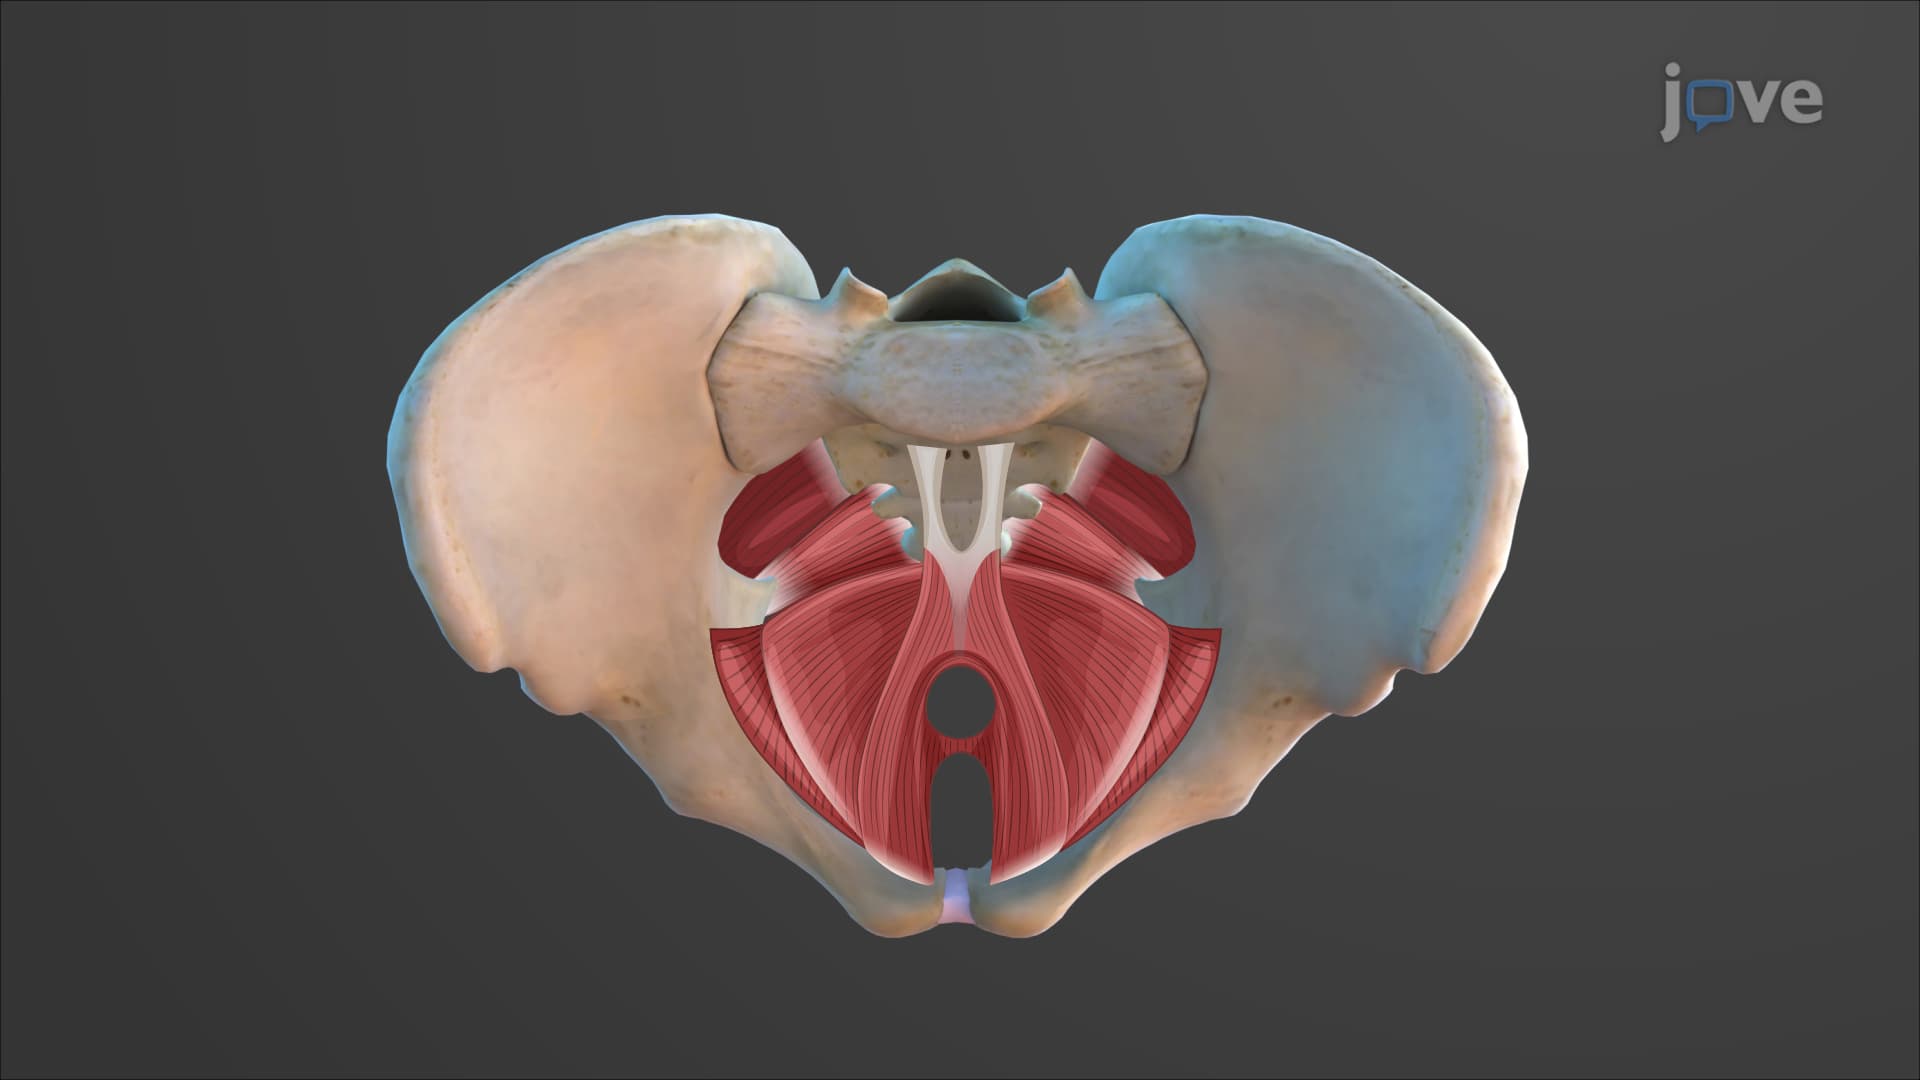
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...