
High on-treatment platelet reactivity and outcome in elderly with non ST-segment elevation acute coronary syndrome -
Roberta De Rosa1, Tullio Palmerini2, Stefano De Servi3
1Department of Cardiology, San Giovanni di Dio e Ruggi d'Aragona University Hospital, Salerno, Italy.

Insights
High on-treatment platelet reactivity (HPR) significantly increases the risk of major adverse cardiac events (MACE) in elderly patients with non-ST-elevated acute coronary syndromes (NSTE-ACS) after percutaneous coronary intervention (PCI). This finding highlights the importance of monitoring platelet function in this vulnerable population.
Area of Science:
- Cardiology
- Geriatric Medicine
- Pharmacology
Background:
- Elderly patients undergoing percutaneous coronary intervention (PCI) for non-ST-elevated acute coronary syndromes (NSTE-ACS) face elevated risks of both ischemic and bleeding events.
- Dual antiplatelet therapy (DAPT) is standard, but managing this risk in older adults remains challenging.
Purpose of the Study:
- To investigate the association between high on-treatment platelet reactivity (HPR) and long-term outcomes in elderly patients with NSTE-ACS who have undergone PCI.
- To determine if HPR is an independent predictor of adverse cardiac events in this specific demographic.
Main Methods:
- A cohort of 1053 NSTE-ACS patients (311 elderly) treated with clopidogrel following PCI were analyzed.
- Platelet reactivity was assessed using the vasodilator-stimulated phosphoprotein (VASP) assay at baseline, discharge, and one month post-PCI.
- Major adverse cardiac events (MACE) were tracked for up to one year.
Main Results:
- Elderly patients with HPR at discharge or one month post-PCI exhibited significantly higher rates of MACE, cardiac death, and myocardial infarction compared to those without HPR.
- HPR in elderly patients was associated with a four-fold increased risk of MACE compared to non-elderly patients with HPR.
- Multivariable analysis confirmed HPR as an independent predictor of one-year MACE in elderly patients.
Conclusions:
- High on-treatment platelet reactivity is an independent risk factor for major adverse cardiac events in elderly patients with NSTE-ACS treated with clopidogrel after PCI.
- Monitoring platelet reactivity may be crucial for optimizing antiplatelet therapy and improving long-term outcomes in this high-risk elderly population.
Background:
Elderly treated with dual antiplatelet therapy after percutaneous coronary intervention (PCI) represent a challenging population because of increased risk of both ischemic and bleeding events. We aimed to investigate the association between high on-treatment platelet reactivity (HPR) and long-term outcome in elderly with non-ST-elevated acute coronary syndromes (NSTE-ACS) undergoing PCI.
Methods:
Platelet reactivity was measured by vasodilator-stimulated phosphoprotein (VASP) assay at three time-points (baseline, discharge, 1 month after PCI) in 1053 NSTE-ACS patients (311 elderly) treated with clopidogrel. Major adverse cardiac events (MACE) were assessed up to 1 year-follow-up.
Results:
Elderly with HPR at discharge showed a significantly higher incidence of overall MACE (13 vs 4%, p = .006), cardiac death (6 vs 0.7%, p = .020), myocardial infarction (MI, 12 vs 4%, p = .031) and a trend for higher stent-thrombosis (5 vs 0.7%, p = .068). Similarly, elderly with 1-month-HPR showed between 1 month and 1 year significantly higher incidence of MACE (10 vs 4%, p = .012), cardiac death (6 vs 0.7%, p = .019) and composite cardiac death/MI (11 vs 4%, p = .014). Up to 1 year, elderly with HPR showed a 4-fold increased risk of MACE compared to both elderly without HPR (for discharge-HPR: p = .005; for 1-month-HPR: p = .01) and non-elderly with HPR (for discharge-HPR: p < .001; for 1-month-HPR: p < .0001). At multivariable analysis, HPR could independently predict 1-year-MACE in elderly (for discharge-HPR: HR = 3.191, CI: 1.373-7.417, p = .007; for 1-month-HPR: HR = 3.542, CI: 1.373-9.137, p = .009).
Conclusions:
In elderly with NSTE-ACS undergoing PCI and treated with clopidogrel, HPR was independently associated with an increased risk of MACE up to 1 year.

Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Acute Coronary Syndrome I: Introduction
 01:26
Acute Coronary Syndrome V: Nursing Management
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 03:12
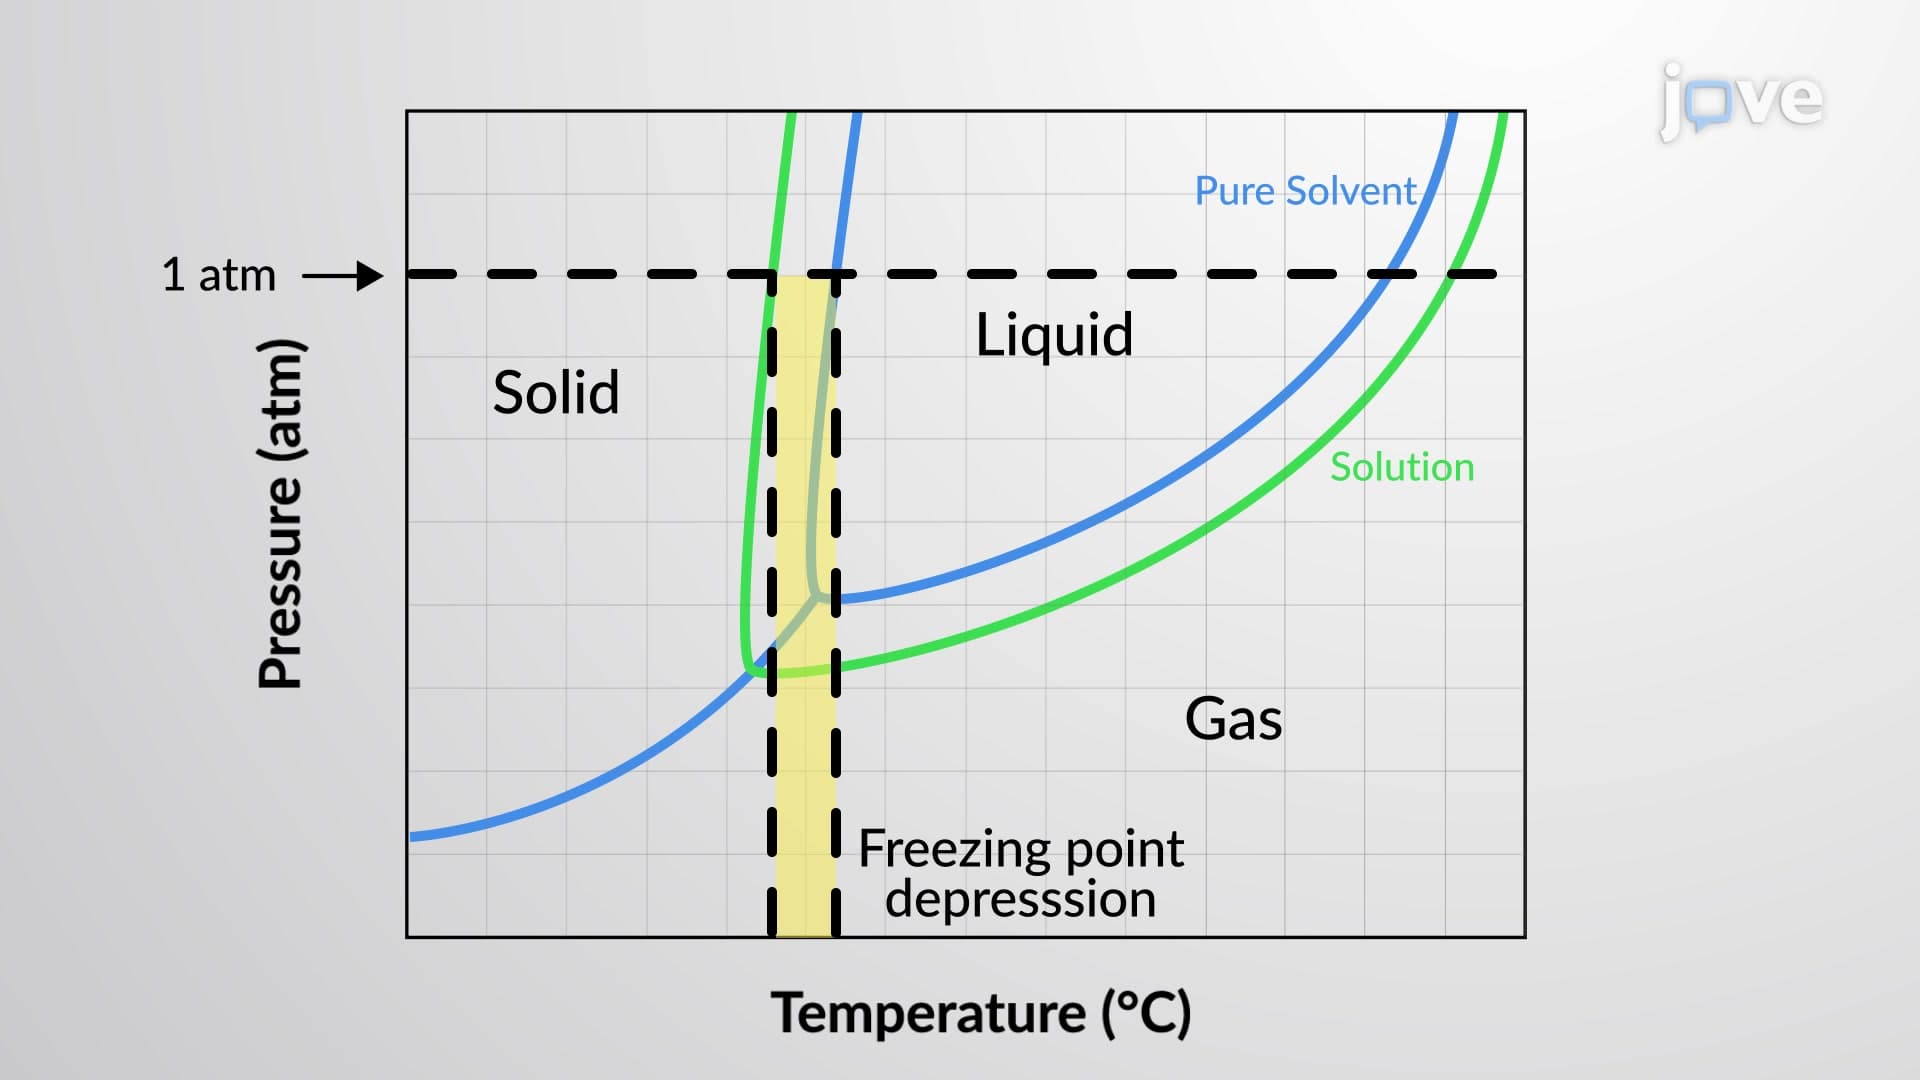
Freezing Point Depression and Boiling Point Elevation
The boiling point of a liquid is the temperature at which its vapor pressure is equal to ambient atmospheric pressure. Since the vapor pressure of a solution is lowered due to the presence of nonvolatile solutes, it stands to reason that the solution’s boiling point will subsequently be increased. Vapor pressure increases with temperature, and so a solution will require a higher temperature than will pure solvent to achieve any given vapor pressure, including one...