Related Experiment Video
Updated: Feb 12, 2026

A Murine Model of Cervical Spinal Cord Injury to Study Post-lesional Respiratory Neuroplasticity
Published on: May 28, 2014
Exploring full cervical dilatation caesarean sections-A retrospective cohort study
Edward M A Corry1, Meenakshi Ramphul1, Ann M Rowan1
1Department of Obstetrics and Gynaecology, National Maternity Hospital, Dublin, Ireland.

Background:
The rate of caesarean sections at full cervical dilatation with their high risk of morbidity continues to rise mirroring the overall increase in caesarean section rates internationally.
Objectives:
The objectives of this study were to determine the rate of full dilatation caesarean section in a tertiary referral unit and evaluate key labour, maternal and fetal factors potentially linked to those deliveries. We also assessed maternal and fetal morbidity at full dilatation sections. Where possible, these were compared with successful operative vaginal deliveries carried out in theatre to determine key differences.
Study Design:
Retrospective cohort study. We reviewed the rate of full dilatation caesarean section over a 10-year period. We analysed deliveries (caesarean sections or operative vaginal deliveries) in single cephalic pregnancies ≥34 weeks with contemporaneously collected data from our unit's electronic database for 2015.
Results:
The rate of full dilatation caesarean section increased by over a third in the ten-year period (56/6947 (0.80%) vs 92/7378 (1.24%), p = 0.01). Of 84 full dilatation caesarean sections who met the inclusion criteria, 63 (75%) were nulliparous and the mean maternal age was 33 (±5) years. Oxytocin was used in the second stage in less than half of second stage caesarean sections (22 out of a recorded 57, 38.6%). There were more fetal head malposition (occipito-posterior, or occipito-transverse) at full dilatation caesarean section compared to successful operative vaginal deliveries (41/46 (89.1%) vs 2/21 (9.5), p < 0.001). The rate of significant postpartum haemorrhage (defined as estimated blood loss ≥1000 ml) was similar in both full dilatation caesarean section and operative vaginal deliveries. There was no difference in the mean birthweight at full dilatation caesarean sections compared to operative vaginal delivery (3.88 kg (2.80-5.33 kg) vs 3.48 kg (1.53-4.40 kg)). There was no difference in neonatal morbidity.
Conclusion:
Fetal head malposition is associated with a higher risk of full dilatation caesarean section. Interestingly, maternal and fetal morbidity were similar between full dilatation caesarean sections and anticipated difficult operative vaginal deliveries carried out in theatre. The management of labour in terms of the decision to use oxytocin judiciously in hope of correcting inefficient uterine contractions and continuous labour ward training, particularly the diagnosis of malposition and its correction may be beneficial in reducing the rate of full dilation caesarean sections.
More Related Videos
 03:05
Influence of Emotional Factors on the Efficacy of Acupuncture Treatment for Overweight Complicated with Hyperlipidemia: A Retrospective Cohort Study
Published on: November 21, 2025
 05:53
Candidate Gene Testing in Clinical Cohort Studies with Multiplexed Genotyping and Mass Spectrometry
Published on: June 21, 2018
Related Concept Videos
 01:50
Cross-Sectional Research
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:30
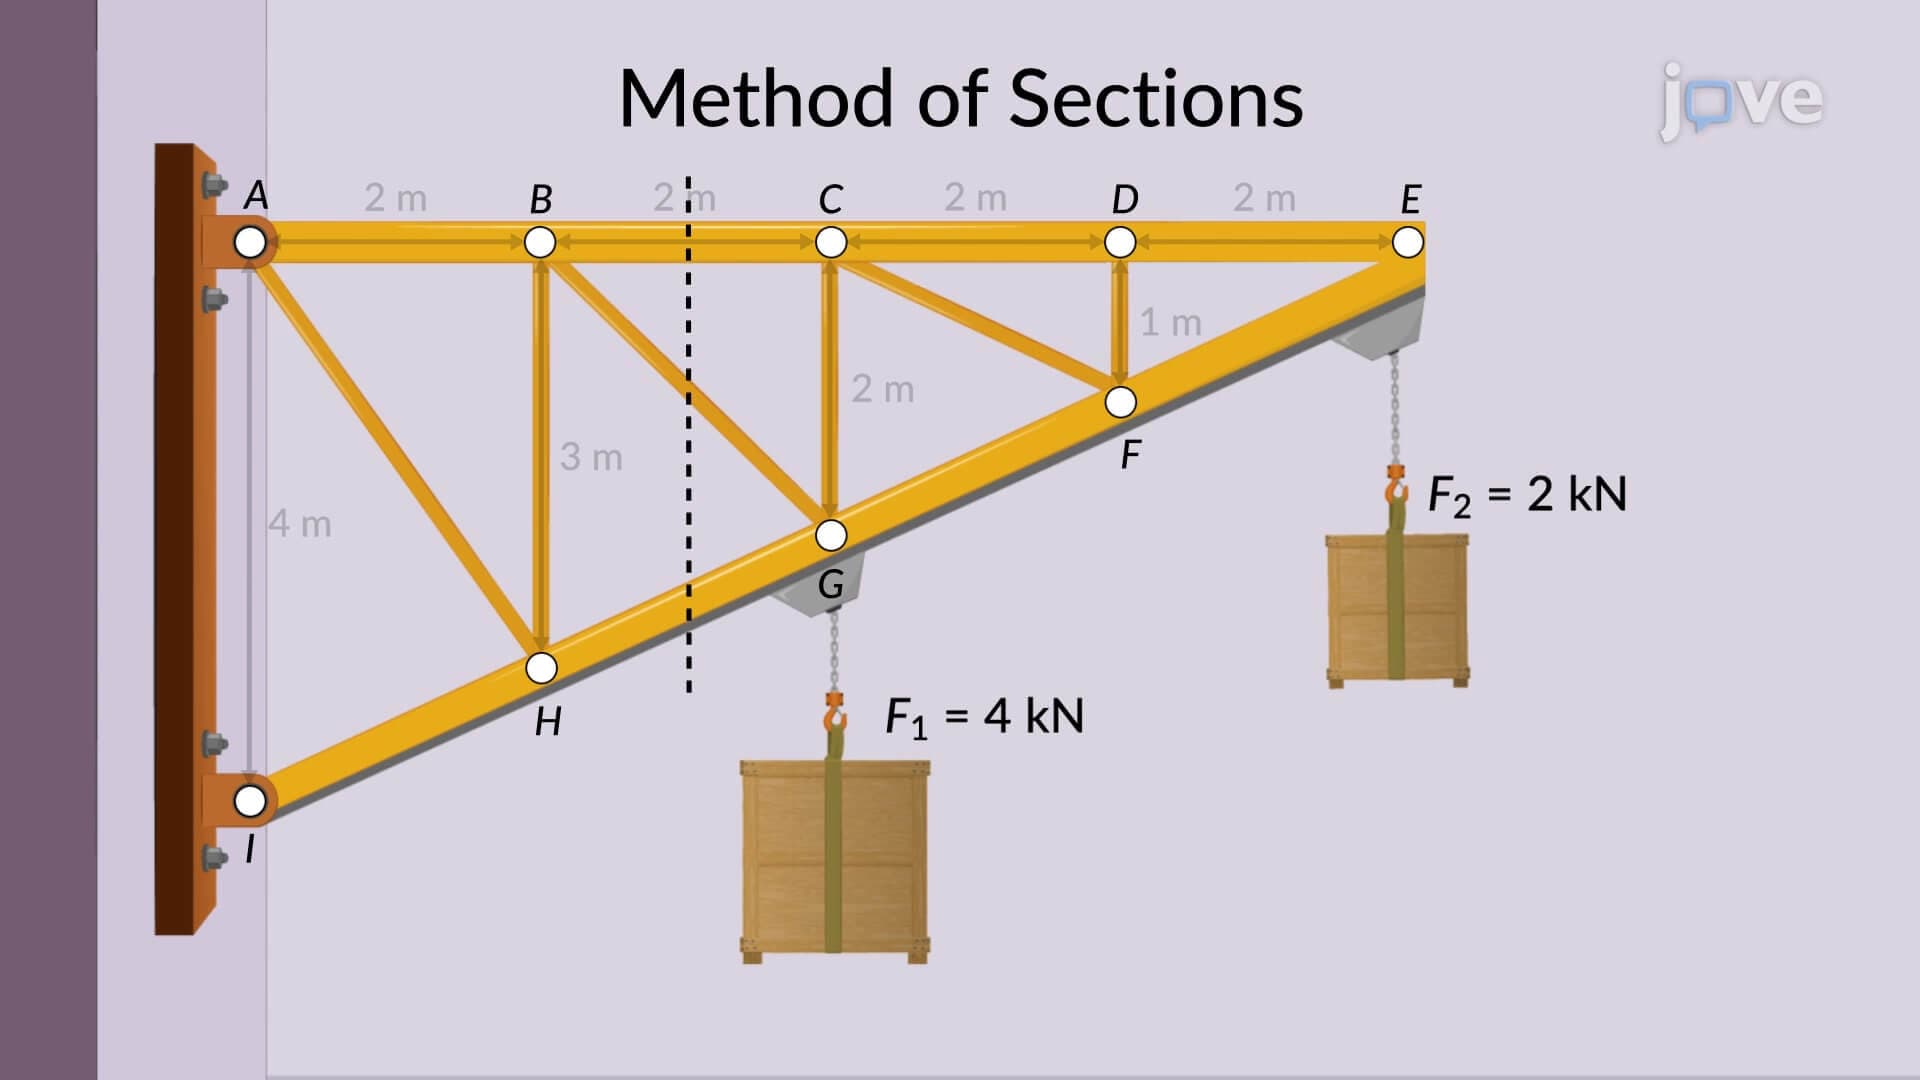
Method of Sections
 01:03
Fixation and Sectioning
The simplest type of preparation is the wet mount, in which the specimen is placed in a drop of liquid on the slide. A liquid specimen can be directly deposited on the slide using a dropper. Solid specimens, such as skin scraping, can be placed on the slide before adding a drop of liquid to prepare the wet mount. Sometimes the liquid is simply water, but stains are often added...
 01:30
Method of Sections: Problem Solving II
 01:27
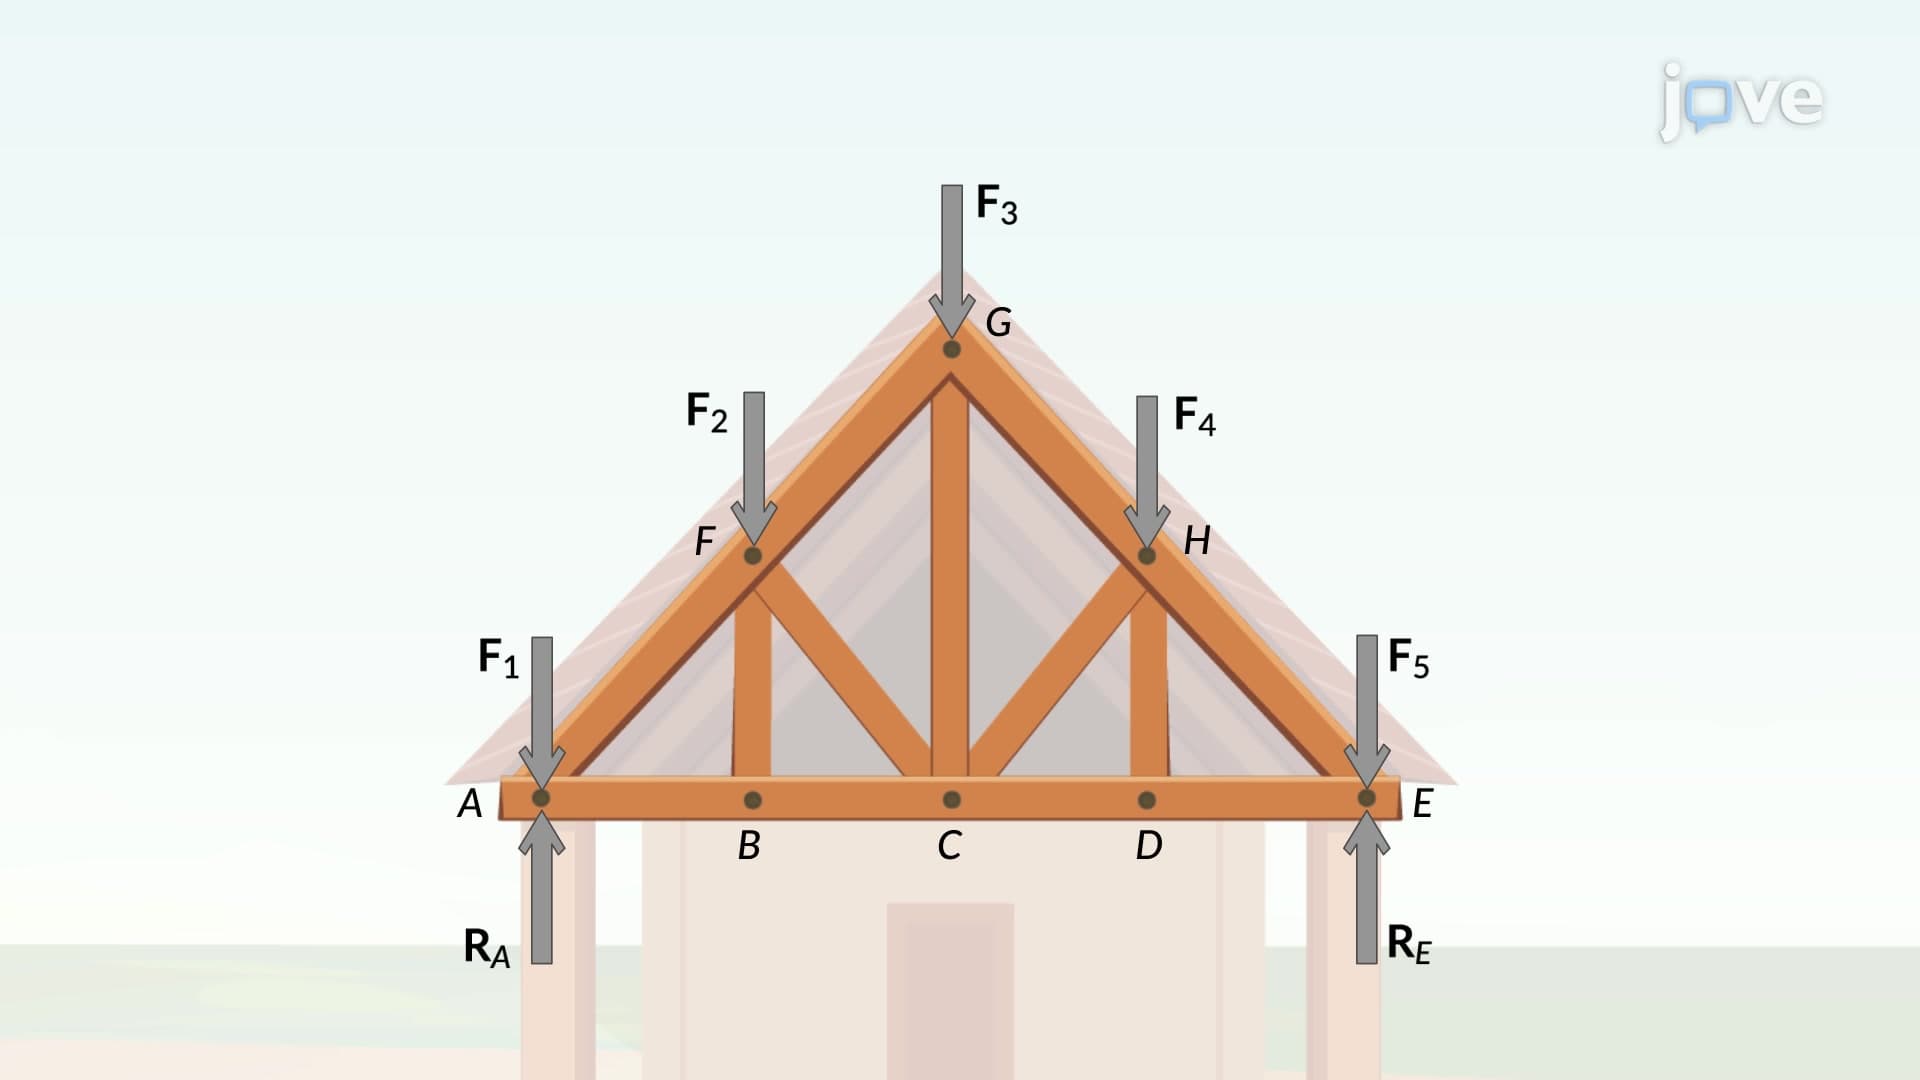
Method of Sections: Problem Solving I