Related Experiment Video
Updated: Feb 12, 2026


Continuous Telemetric In Utero Tracheal Pressure Measurements in Fetal Lambs
Published on: December 22, 2023
In utero Fetal Intubation for a Large Neck Mass: A Minimally Invasive EXIT Option
Ramen H Chmait1, Andrew H Chon2, Dean Anselmo3
1Department of Obstetrics and Gynecology, Division of Maternal-Fetal Medicine, Keck School of Medicine, University of Southern California, Los Angeles, California, USA, chmait@usc.edu.

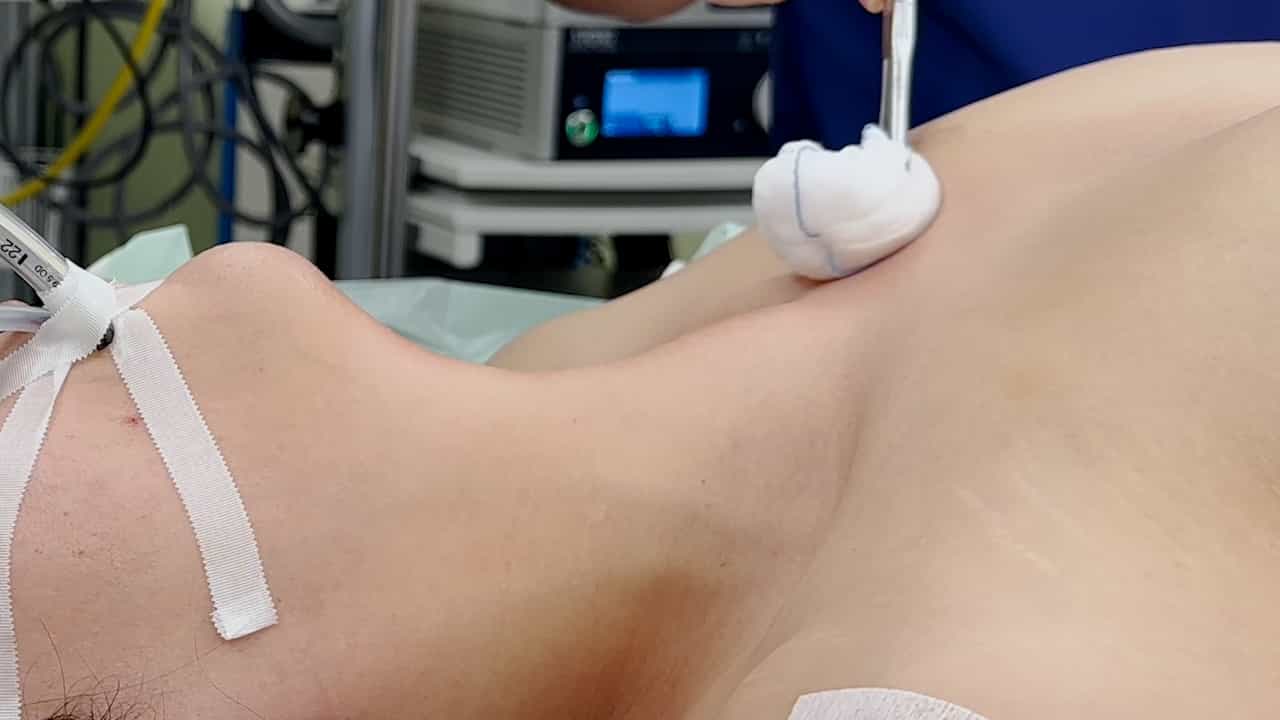
Fetuses with obstructive neck and orofacial lesions have been delivered via an ex utero intrapartum treatment (EXIT) procedure to facilitate securement of the airway while on placental circulation. Pregnancy-related cardiovascular changes and technical issues unique to an EXIT procedure increase fetal and maternal risks relative to a standard cesarean section. In order to circumvent such issues, fetal endoscopic intubation has been proposed. We report a case of a fetus with a large neck mass (mixed solid and multiloculated cystic lesion measuring 9.2 × 5.3 × 8.5 cm, neck hyperextension, protruding tongue, and serial gagging movements) that was successfully intubated in utero and delivered at 36 weeks and 0 days via standard cesarean section, thereby avoiding an EXIT procedure. The risks, benefits, and technical issues of in utero tracheal intubation are reviewed.
Fetuses with obstructive neck and orofacial lesions have been delivered via an ex utero intrapartum treatment (EXIT) procedure to facilitate securement of the airway while on placental circulation. Pregnancy-related cardiovascular changes and technical issues unique to an EXIT procedure increase fetal and maternal risks relative to a standard cesarean section. In order to circumvent such issues, fetal endoscopic intubation has been proposed. We report a case of a fetus with a large neck mass (mixed solid and multiloculated cystic lesion measuring 9.2 × 5.3 × 8.5 cm, neck hyperextension, protruding tongue, and serial gagging movements) that was successfully intubated in utero and delivered at 36 weeks and 0 days via standard cesarean section, thereby avoiding an EXIT procedure. The risks, benefits, and technical issues of in utero tracheal intubation are reviewed.

Related Concept Videos
 01:26
Muscles of the Anterior Neck
 01:26
Arteries of the Head and Neck
The internal carotid arteries supply blood to the anterior portion of the cerebrum. They enter the...
 01:19
Veins of Head and Neck
On the other hand, the vertebral veins, unlike their arterial counterparts, are not primarily responsible for brain drainage. Instead, they drain the cervical vertebrae, spinal cord, and some small...
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:14
Fetal Circulation
Two umbilical arteries transport blood from the fetus to the placenta. At the placenta, the blood absorbs oxygen and nutrients while simultaneously eliminating waste products. This oxygen-enriched and nutrient-rich blood then returns to the fetus through one...
 01:52
Atomic Mass