Related Experiment Video
Updated: Feb 11, 2026


Postconditioning with Lactate-enriched Blood for Cardioprotection in ST-segment Elevation Myocardial Infarction
Published on: May 28, 2019
Value-Based ST-Segment-Elevation Myocardial Infarction Care Using Risk-Guided Triage and Early Discharge
Joseph E Ebinger1, Craig E Strauss1, Ross R Garberich1
1Cedars-Sinai Smidt Heart Institute at Cedars-Sinai Medical Center, Los Angeles, CA (J.E.E., T.D.H.). Minneapolis Heart Institute at Abbott Northwestern Hospital, MN (C.E.S., S.M.B., P.R., I.J.C., A.K.P., T.D.H.). Minneapolis Heart Institute Foundation, MN (R.R.G., S.M.B., B.R.P.).

Insights
Implementing a ST-segment-elevation myocardial infarction (STEMI) risk score enables early discharge for low-risk patients, reducing costs without compromising care quality. This risk-guided approach improves healthcare value for STEMI treatment.
Area of Science:
- Cardiology
- Health Economics
- Clinical Triage
Background:
- Prior studies suggest early discharge for low-risk ST-segment-elevation myocardial infarction (STEMI) patients post-primary percutaneous coronary intervention.
- The study addresses the need to decrease healthcare costs associated with STEMI care while maintaining optimal patient outcomes.
Purpose of the Study:
- To implement and evaluate an STEMI risk score for guiding patient triage and discharge.
- To assess the impact of risk-guided care on healthcare value, including costs and patient outcomes.
Main Methods:
- Retrospective application of the Zwolle Risk Score to 967 patients undergoing primary percutaneous coronary intervention (2009-2011).
- Development and electronic medical record integration of a modified Zwolle Risk Calculator for a fast-track protocol.
- Prospective evaluation of the protocol in 549 STEMI patients.
Main Results:
- Low-risk STEMI patients (62% prospectively) had significantly lower complication rates (8.3% vs 38.7%) and in-hospital mortality (0.4% vs 12.5%) compared to high-risk patients.
- The fast-track protocol for low-risk patients resulted in a shorter median length of stay (2 days vs 3 days) and lower overall costs ($6720 vs $11,783).
- On-protocol low-risk patients demonstrated further reductions in length of stay and costs compared to off-protocol patients and those in the retrospective cohort.
Conclusions:
- Risk-guided triage and early discharge for STEMI patients after primary percutaneous coronary intervention enhance healthcare value.
- The implemented protocol successfully reduced costs without negatively impacting patient outcomes or quality of care.
- The modified Zwolle Risk Calculator effectively supports the fast-track protocol for eligible low-risk STEMI patients.
Background:
Prior studies suggest that low-risk ST-segment-elevation myocardial infarction (STEMI) patients undergoing primary percutaneous coronary intervention can be considered for early discharge. We describe the implementation of an STEMI risk score to decrease cost while maintaining optimal patient outcomes.
Methods And Results:
We determined the impact of risk-guided STEMI care on healthcare value through the retrospective application of the Zwolle Risk Score to 967 patients receiving primary percutaneous coronary intervention between 2009 and 2011. Of these patients, 540 (56%) were categorized as low risk, indicating they may be safely triaged directly to a telemetry unit rather than the intensive care unit and targeted for early discharge. We subsequently developed and implemented a modified Zwolle Risk Calculator into the electronic medical record to support application of the fast-track protocol for low-risk STEMI patients. Among 549 prospective patients with STEMI, 62% were low risk, and the fast-track protocol was followed in 75% of cases. Prospective results confirmed lower rates of complications (low risk 8.3% versus high risk 38.7%; P<0.001) and in-hospital mortality (low risk 0.4% versus High risk 12.5%; P<0.001) in the low-risk cohort. Low-risk patients had a shorter median length of stay (median and [25th, 75th percentiles]: low risk 2 [2, 3] versus high risk: 3 [2, 6]; P<0.001) and lower overall costs (low risk $6720 [$5280-$9030] versus high risk $11 783 [$7953-$25 359]; P<0.001). Low-risk patients treated on-protocol had shorter median length of stay (on-protocol 2 [1, 2] versus off-protocol 2 [2, 3]; P<0.001) and hospital costs (on-protocol $6090 [$4730, $7356] versus off-protocol $11 783 [$7953, $25 359]; P<0.001) than those treated off-protocol. On-protocol low-risk patients in the prospective cohort also had lower costs and shorter length of stay than low-risk patients in the retrospective cohort (P<0.001 for both).
Conclusions:
In our study, risk-guided triage and discharge after primary percutaneous coronary intervention for STEMI improved healthcare value by reducing costs of care without compromising quality of care or patient outcomes.

Related Concept Videos
 03:12
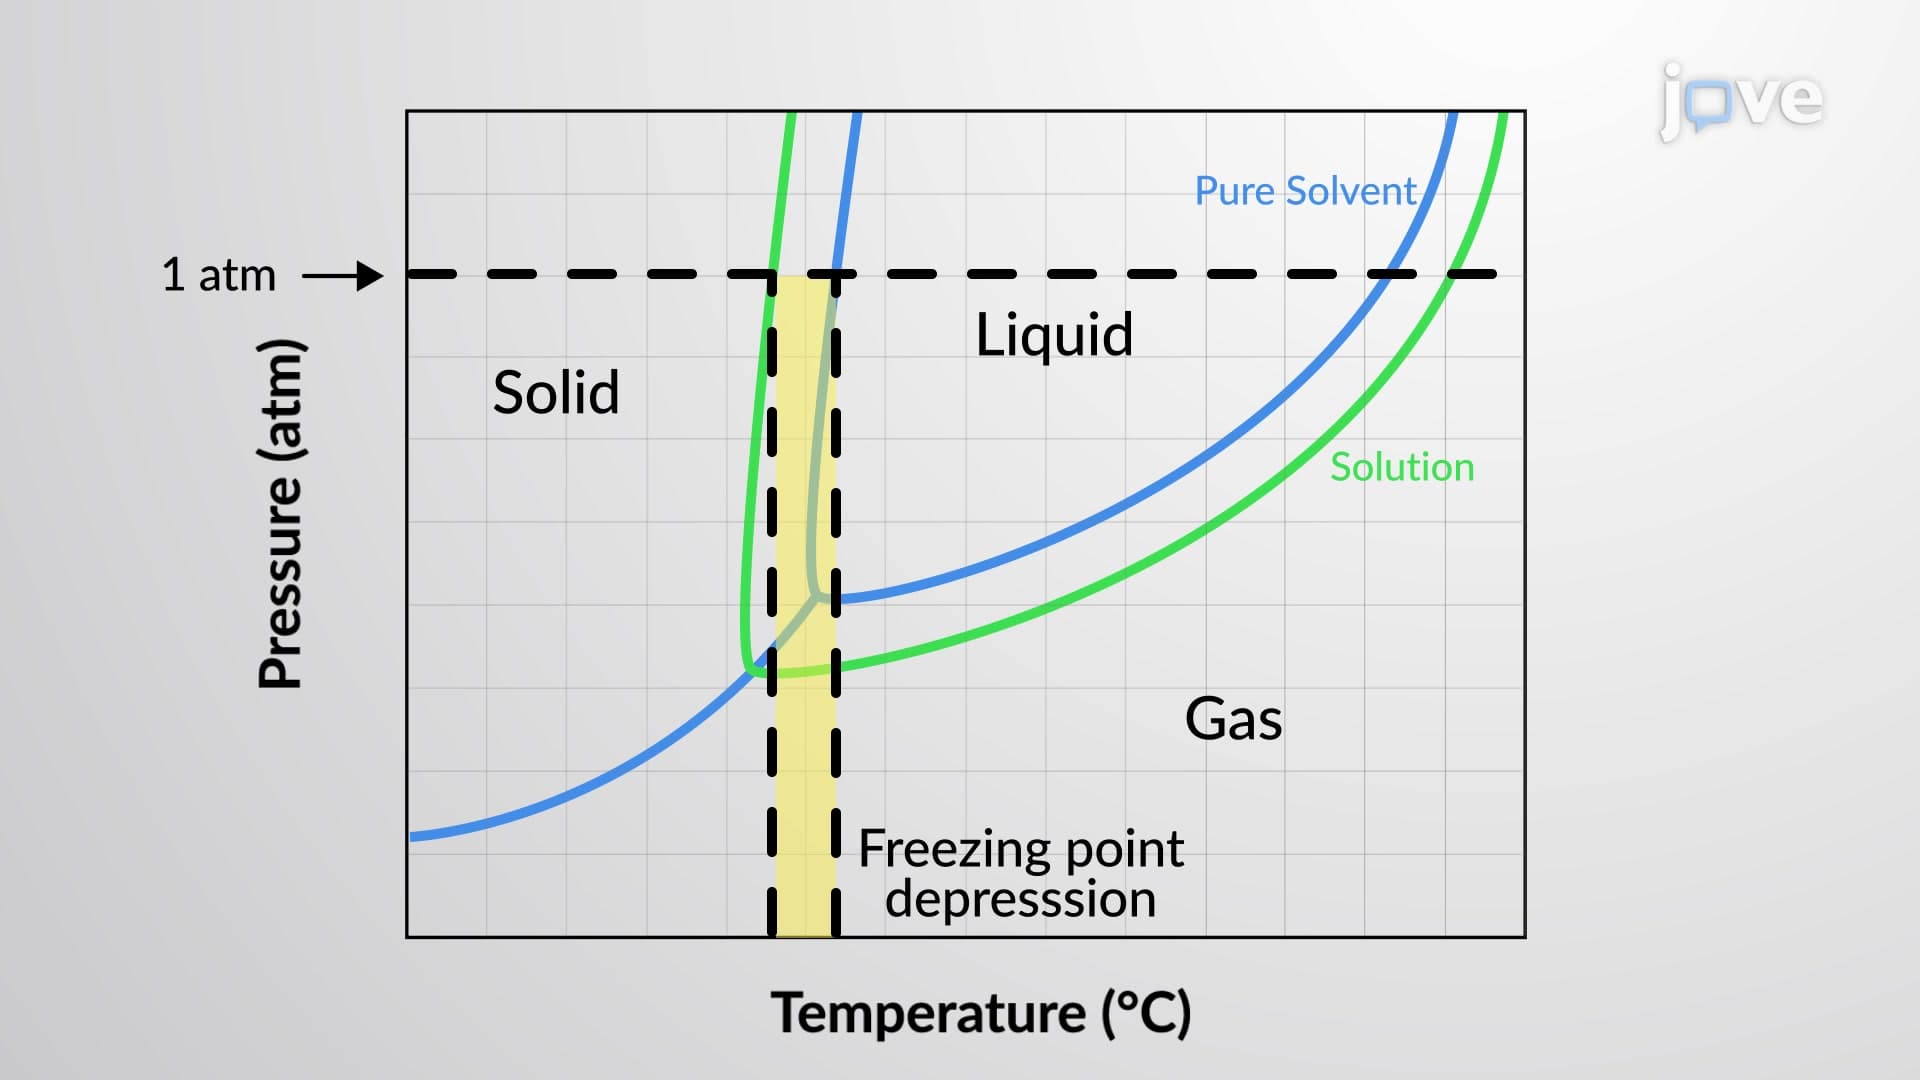
Freezing Point Depression and Boiling Point Elevation
The boiling point of a liquid is the temperature at which its vapor pressure is equal to ambient atmospheric pressure. Since the vapor pressure of a solution is lowered due to the presence of nonvolatile solutes, it stands to reason that the solution’s boiling point will subsequently be increased. Vapor pressure increases with temperature, and so a solution will require a higher temperature than will pure solvent to achieve any given vapor pressure, including one...
 01:31
Discharge Summary Forms
Here's a detailed look at the key components and guidelines for preparing a discharge summary:
 01:27
RC Circuits: Discharging A Capacitor
 01:12
Relative Risk
 01:20
Elevation of Intermediate Points on Vertical Curves
 01:21
Interdisciplinary Care: The Health Care Team-I
Physicians
The physician's primary responsibility is to diagnose illness and direct the medical or surgical treatment of the condition. The authority to admit patients to a healthcare agency or institution and practice care within that setting is granted to physicians by the healthcare agency or institution...