Related Experiment Video
Updated: Feb 11, 2026
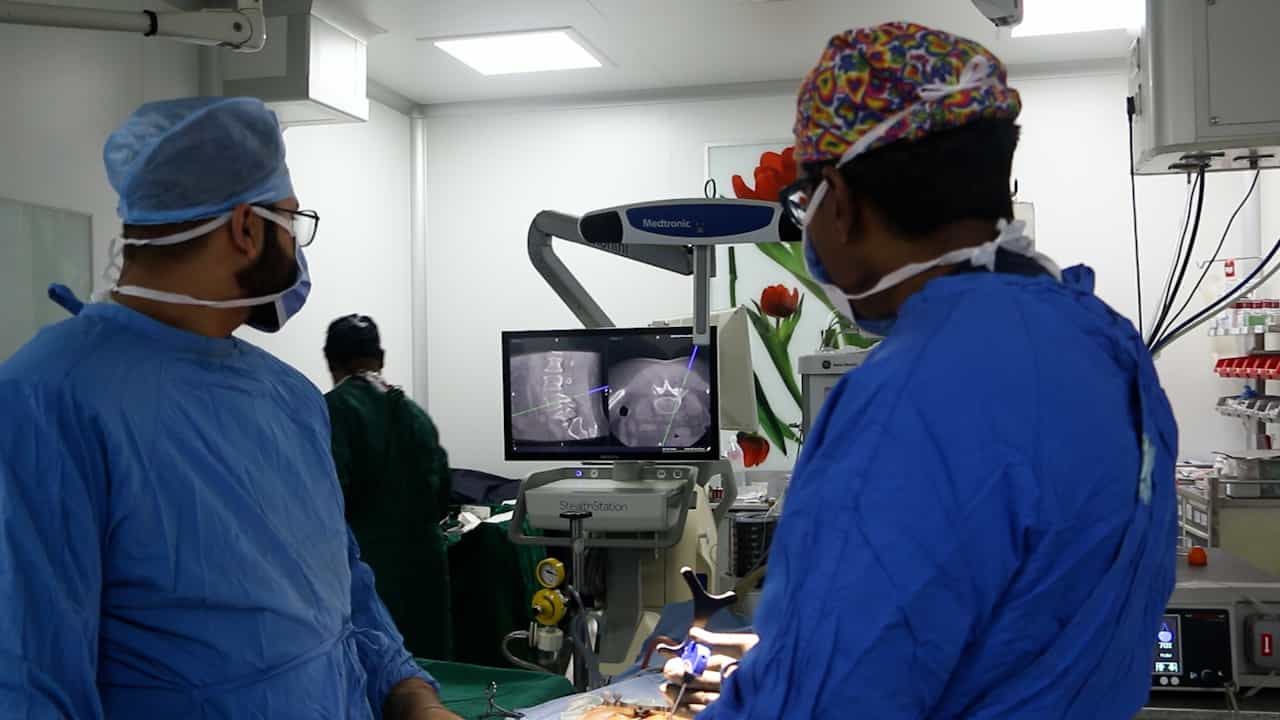
Optimizing Minimally Invasive Spine Surgery: A Fully 3D CT O-Arm Navigated Workflow in MIS TLIF
Published on: October 17, 2025
Comparison between minimally invasive spine stabilization with and without posterior decompression for the management
Hiroshi Uei1, Yasuaki Tokuhashi2, Masafumi Maseda2
1Department of Orthopaedic Surgery, Nihon University School of Medicine, 30-1 Oyaguchi Kami-cho, Itabashi-ku, Tokyo, 173-8610, Japan. uei.hiroshi@nihon-u.ac.jp.

Background:
Posterior decompression and stabilization plays significant roles in palliative surgery for metastatic spinal tumor. However, the indication for addition of posterior decompression have not been examined. The purpose of this study was to investigate a retrospective cohort of outcomes of metastatic spinal tumor treated with minimally invasive spine stabilization (MISt) with or without posterior decompression.
Methods:
The subjects were 40 patients who underwent MISt using percutaneous pedicle screws for metastatic spinal tumor, including 20 patients treated with stabilization alone (group A) and 20 patients with added posterior decompression (group B). We analyzed baseline characteristics, postoperative survival time, and perioperative factors such as neurological outcomes, Barthel Index, VAS, and rate of discharge to home.
Results:
The mean ages were 70 and 66 years old (P = 0.06), the mean revised Tokuhashi scores were 7.2 and 5.8 (P = 0.1), the mean spinal instability neoplastic scores (SINS) were 10.5 and 9.0 (P = 0.04), and the mean Barthel Index for ADL were 65.5 and 41.0 (P = 0.06) in groups A and B, respectively. The median postoperative survival time did not differ significantly between groups A and B (12.0 vs. 6.0 months, P = 0.09). Patients in group A had a significantly shorter operation time (166 vs. 232 min, P = 0.004) and lower intraoperative blood loss (120 vs. 478 mL, P < 0.001). Postoperative paralysis (P = 0.1), paralysis improvement rate (P = 0.09), postoperative Barthel Index (P = 0.06), and postoperative VAS (P = 0.6) did not differ significantly between the groups. The modified Frankel classification improved from D1 or D2 before surgery to D3 or E after surgery in 4 of 10 cases (40%) in group A and 8 of 8 patients (100%) in group B (P = 0.01). Significantly more patients were discharged to home in group A (P = 0.02), whereas significantly more patients died in the hospital in group B (P = 0.02).
Conclusions:
Patients treated without decompression had a shorter operation time, less blood loss, a higher rate of discharge to home, and lower in-hospital mortality, indicating a procedure with lower invasiveness. MISt without decompression is advantageous for patients with D3 or milder paralysis, but decompression is necessary for patients with D2 or severer paralysis.
Related Concept Videos
 02:57
The Sense of Self: Reflected Self-Appraisal and Social Comparison
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 03:18
Nuclear Stability
To hold positively charged protons together...
 01:53
RNA Stability
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:28
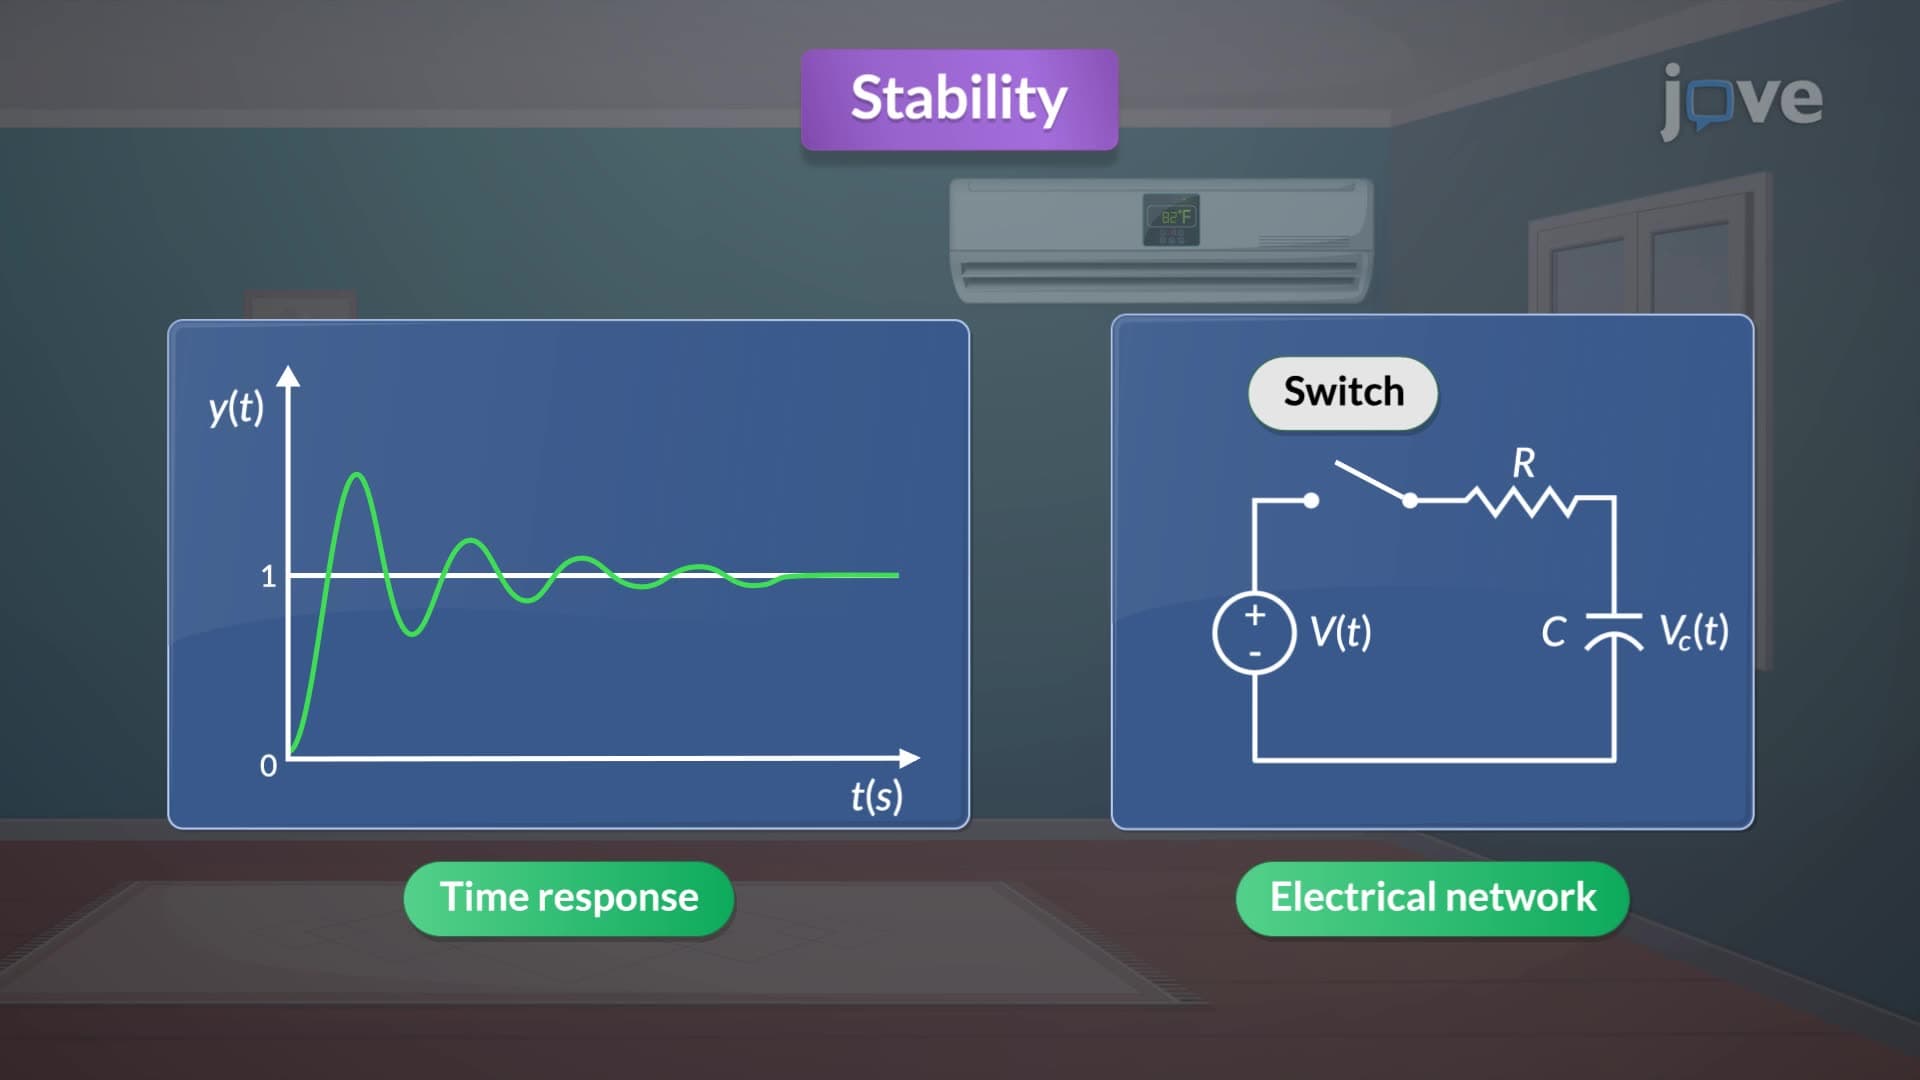
Stability
The stability of an LTI system is determined by the roots of its characteristic equation, known as poles. A system is stable if it produces a bounded...