Related Experiment Video
Updated: Feb 11, 2026
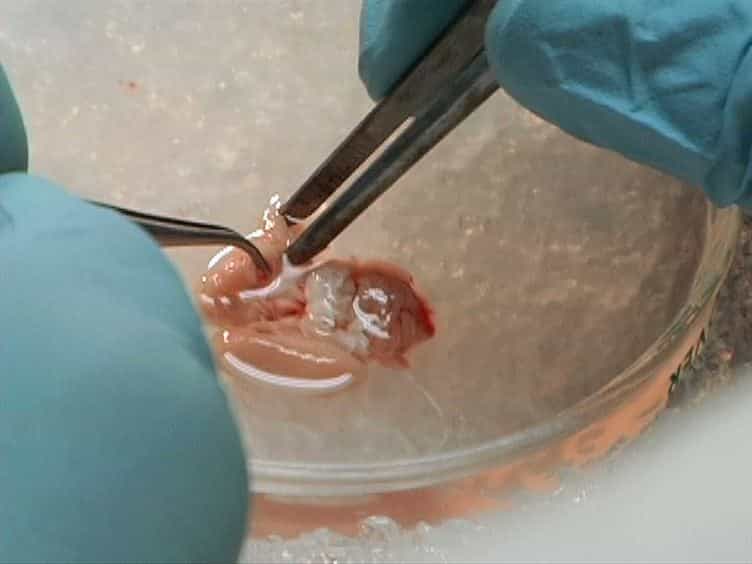

A Visual Description of the Dissection of the Cerebral Surface Vasculature and Associated Meninges and the Choroid Plexus from Rat Brain
Published on: November 14, 2012
Aspergillus sinusitis complicated with meningitis and multiple cerebral infarctions in immunocompetent patient
Ahmad AlHaj Houssen1, Fahad Algreeshah
1Departmentof Neurosurgery, National Care Hospital, Riyadh, Kingdom of Saudi Arabia.

Abstract:
This is a case of a 33-year-old male complaining of severe headache, neck pain, photophobia, vomiting and high-grade fever of several days. He had history of nasal polyp removal and recurrent sinusitis in the last 8 years. On examination: conscious with glasco coma scale (GCS) 15/15 and normal limbs strength but with positive Babinski sign. For further observation, he was admitted and full work-up was done. Even though full empirical antibiotics were started, there was no immediate improvement and he deteriorated dramatically developing ocular deficit, hydrocephalus and lower level of consciousness with multiple infarctions found at different areas in brain. After that point, a decompressive craniectomy was done, and multiple antibiotics and antifungal medications were prescribed. However, he deteriorated to GCS 3/15; cardiopulmonary resuscitations were not successful, as he demised next day. It shall be noted that aspergillosis can lead to difficult complications, so diagnosis and treatments should not be delayed.
Insights
A severe headache and fever case highlights the dangerous complications of invasive aspergillosis. Prompt diagnosis and treatment are crucial to prevent fatal outcomes from this fungal infection.
Area of Science:
- Neurology
- Infectious Diseases
- Mycology
Background:
- This case involves a 33-year-old male with a history of recurrent sinusitis and nasal polyp removal.
- The patient presented with severe headache, neck pain, photophobia, vomiting, and high-grade fever.
Observation:
- Initial examination revealed a Glasgow Coma Scale (GCS) of 15/15 and normal limb strength, but a positive Babinski sign was noted.
- Despite empirical antibiotic treatment, the patient's condition rapidly worsened, showing signs of neurological deterioration.
Findings:
- The patient developed ocular deficits, hydrocephalus, decreased consciousness, and multiple brain infarctions.
- A decompressive craniectomy was performed, and broad-spectrum antibiotics and antifungals were administered.
Implications:
- This case underscores the aggressive nature of invasive aspergillosis and its potential for severe neurological complications.
- Delayed diagnosis and treatment of fungal infections like aspergillosis can lead to catastrophic outcomes, emphasizing the need for timely intervention.

Related Concept Videos
 01:19
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:22
Development of Immunocompetence
The initial cells that migrate from the fetal thymus settle within the skin and epithelial tissues lining the mouth, digestive tract, and in females, the uterus and vagina. These cells, including skin-based dendritic cells, serve as antigen-presenting cells, playing a key role in T cell activation.
Subsequent T...
 01:49
Multiple Allele Traits
 01:24
Hemodialysis II: Procedure and Complications
 01:16
ECG Interpretation of Arrhythmias I: Sinus Arrhythmias
Types of Arrhythmias
Sinus Node Arrhythmias
Sinus Bradycardia: Originating from the sinoatrial (SA) node, sinus bradycardia involves slower impulses, resulting in a heart rate of less than 60 beats per minute (bpm). Causes include sleep, vagal stimulation, beta-blockers, hypothyroidism,...
 01:30
Pneumonia III: Complications and Assessment