Related Experiment Video
Updated: Feb 11, 2026
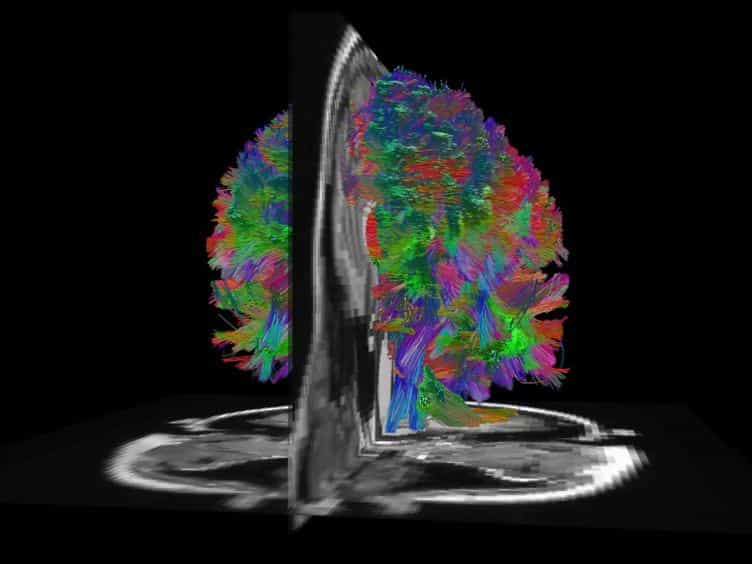

Co-analysis of Brain Structure and Function using fMRI and Diffusion-weighted Imaging
Published on: November 8, 2012
Differentiation of brain infection from necrotic glioblastoma using combined analysis of diffusion and perfusion MRI
Sanjeev Chawla1, Sumei Wang1, Suyash Mohan1
1Department of Radiology, Perelman School of Medicine at the University of Pennsylvania, Philadelphia, Pennsylvania, USA.

Background:
Accurate differentiation of brain infections from necrotic glioblastomas (GBMs) may not always be possible on morphologic MRI or on diffusion tensor imaging (DTI) and dynamic susceptibility contrast perfusion-weighted imaging (DSC-PWI) if these techniques are used independently.
Purpose:
To investigate the combined analysis of DTI and DSC-PWI in distinguishing brain injections from necrotic GBMs.
Study Type:
Retrospective.
Population:
Fourteen patients with brain infections and 21 patients with necrotic GBMs.
Field Strength/Sequence:
3T MRI, DTI, and DSC-PWI.
Assessment:
Parametric maps of mean diffusivity (MD), fractional anisotropy (FA), coefficient of linear (CL), and planar anisotropy (CP) and leakage corrected cerebral blood volume (CBV) were computed and coregistered with postcontrast T1 -weighted and FLAIR images. All lesions were segmented into the central core and enhancing region. For each region, median values of MD, FA, CL, CP, relative CBV (rCBV), and top 90th percentile of rCBV (rCBVmax ) were measured.
Statistical Tests:
All parameters from both regions were compared between brain infections and necrotic GBMs using Mann-Whitney tests. Logistic regression analyses were performed to obtain the best model in distinguishing these two conditions.
Results:
From the central core, significantly lower MD (0.90 × 10⁻³ ± 0.44 × 10⁻³ mm2 /s vs. 1.66 × 10⁻³ ± 0.62 × 10⁻³ mm2 /s, P = 0.001), significantly higher FA (0.15 ± 0.06 vs. 0.09 ± 0.03, P < 0.001), and CP (0.07 ± 0.03 vs. 0.04 ± 0.02, P = 0.009) were observed in brain infections compared to those in necrotic GBMs. Additionally, from the contrast-enhancing region, significantly lower rCBV (1.91 ± 0.95 vs. 2.76 ± 1.24, P = 0.031) and rCBVmax (3.46 ± 1.41 vs. 5.89 ± 2.06, P = 0.001) were observed from infective lesions compared to necrotic GBMs. FA from the central core and rCBVmax from enhancing region provided the best classification model in distinguishing brain infections from necrotic GBMs, with a sensitivity of 91% and a specificity of 93%.
Data Conclusion:
Combined analysis of DTI and DSC-PWI may provide better performance in differentiating brain infections from necrotic GBMs.
Level Of Evidence:
1 Technical Efficacy: Stage 2 J. Magn. Reson. Imaging 2019;49:184-194.
Insights
Combining diffusion tensor imaging (DTI) and dynamic susceptibility contrast perfusion-weighted imaging (DSC-PWI) accurately differentiates brain infections from necrotic glioblastomas (GBMs). This combined approach offers improved diagnostic performance for these challenging conditions.
Area of Science:
- Neuroimaging
- Radiology
- Oncology
Background:
- Differentiating brain infections from necrotic glioblastomas (GBMs) can be challenging using standard MRI, diffusion tensor imaging (DTI), or dynamic susceptibility contrast perfusion-weighted imaging (DSC-PWI) alone.
- Morphologic MRI and individual advanced imaging techniques may not provide sufficient accuracy.
Purpose of the Study:
- To evaluate the combined diagnostic utility of DTI and DSC-PWI in distinguishing between brain infections and necrotic GBMs.
- To identify imaging parameters that best differentiate these conditions.
Main Methods:
- Retrospective analysis of 3T MRI data from 14 patients with brain infections and 21 with necrotic GBMs.
- Quantitative analysis of DTI parameters (mean diffusivity, fractional anisotropy, anisotropy coefficients) and DSC-PWI parameters (relative cerebral blood volume) in the central core and enhancing regions of lesions.
- Logistic regression modeling to determine the optimal combination of parameters for differentiation.
Main Results:
- Significantly different values for mean diffusivity, fractional anisotropy, and planar anisotropy were observed in the central core between infections and GBMs.
- Relative cerebral blood volume and its maximum percentile were significantly lower in the enhancing regions of infections compared to GBMs.
- A classification model using fractional anisotropy from the central core and maximum relative cerebral blood volume from the enhancing region achieved 91% sensitivity and 93% specificity.
Conclusions:
- The combined analysis of DTI and DSC-PWI demonstrates superior performance in differentiating brain infections from necrotic GBMs compared to individual techniques.
- Specific DTI and DSC-PWI parameters from distinct lesion regions can reliably distinguish between these pathologies.
More Related Videos


Related Concept Videos
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this...
 01:30
Radiological Investigation II: MRI and Ventilation Perfusion Scan
Magnetic Resonance Imaging (MRI) and Ventilation Perfusion Scans are two radiological investigations that offer detailed diagnostic images of the body, particularly lung structures.
MRI
MRI uses magnetic fields and radiofrequency signals to distinguish between normal and abnormal tissues. This technology provides a more detailed diagnostic image than CT scans, enabling it to characterize pulmonary nodules, stage bronchogenic carcinoma, and evaluate inflammatory activity in...
 01:12
Diffusion
 01:21
Diffusion
 01:16
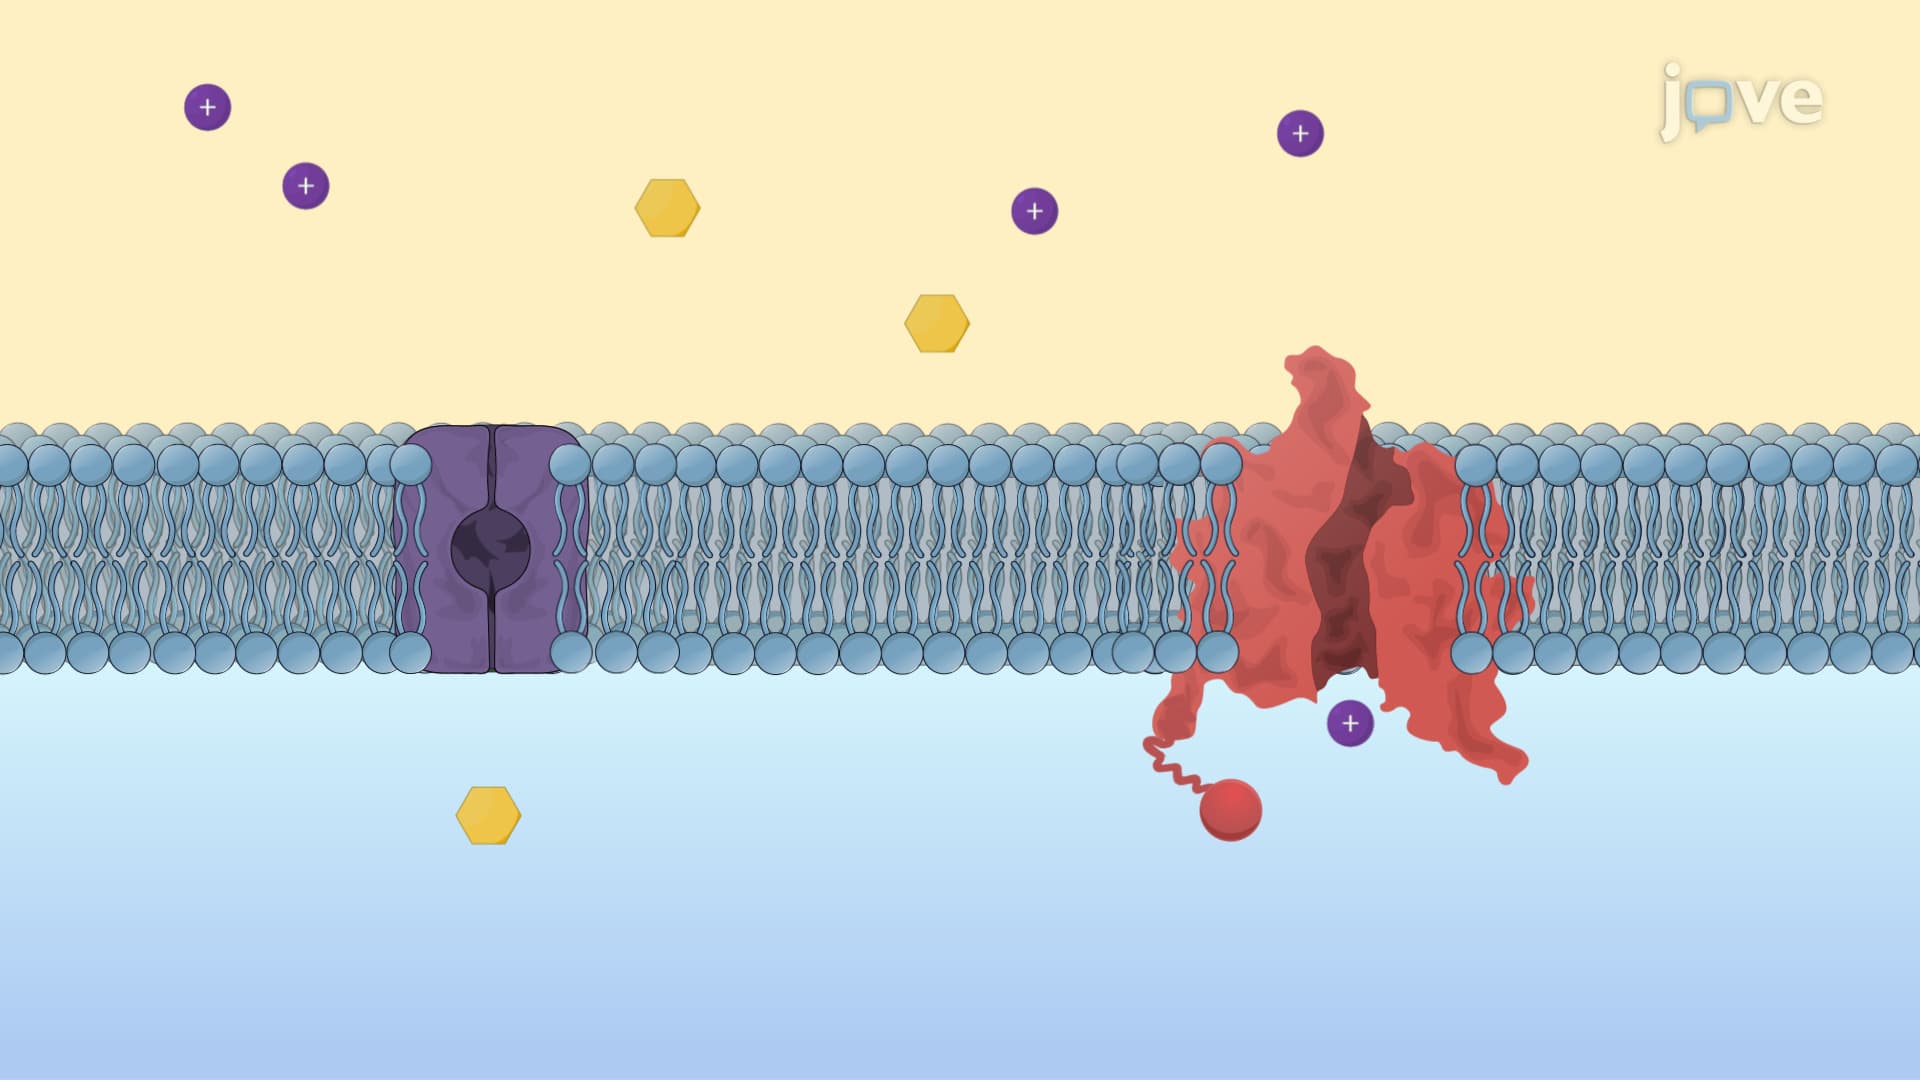
Facilitated Diffusion
In this process, substrates such as organic compounds and ions interact with a transporter on one side, triggering conformational changes in proteins that enable...
 03:48
Behavior of Gas Molecules: Molecular Diffusion, Mean Free Path, and Effusion