Related Experiment Video
Updated: Feb 11, 2026


Sentinel Lymph Node Mapping and Biopsy for Endometrial Cancer at Early Stage with Laparoscopy
Published on: August 19, 2021
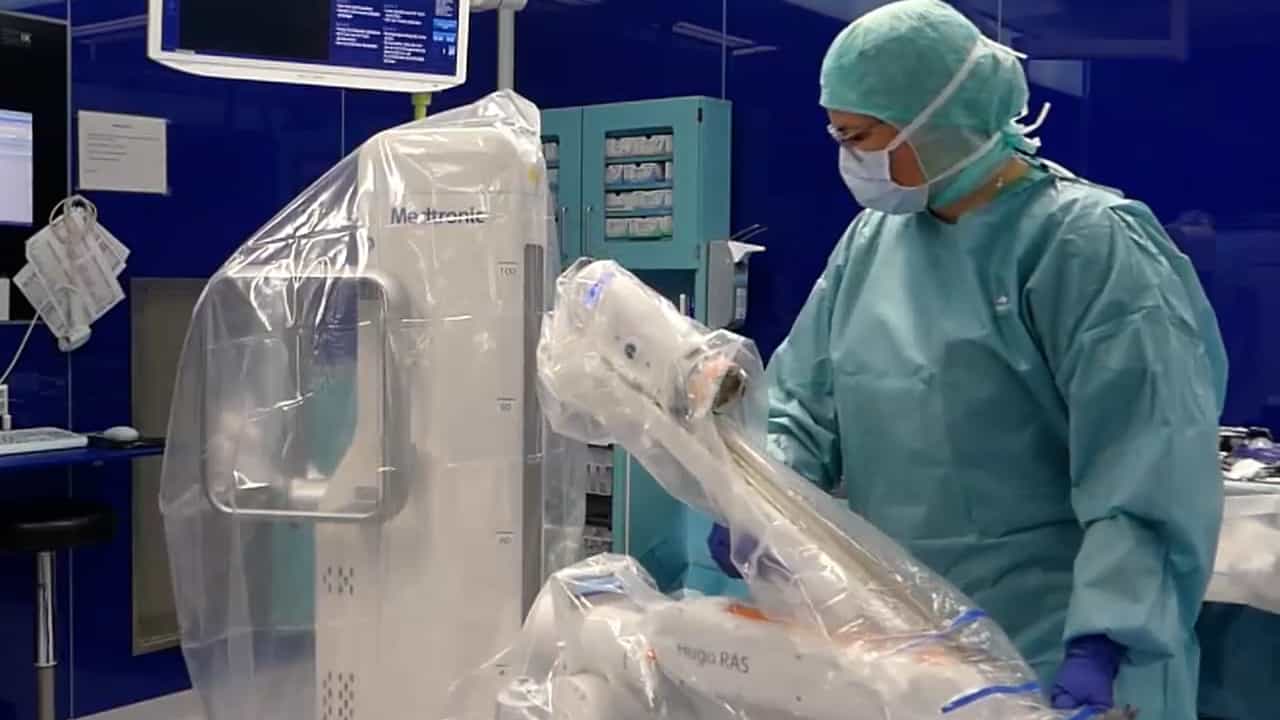
Dual docking robotic surgical staging for high risk endometrial cancer
Cécile Loaec1, Anne-Sophie Bats2, Charlotte Ngo2
1Chirurgie Cancérologique Gynécologique et du Sein, Hôpital Européen Georges-Pompidou, Paris, France.

Objective:
The standard of care for patients with high intermediate and high risk endometrial cancer is surgical staging including total hysterectomy with bilateral salpingo-oophorectomy, and pelvic and para-aortic lymphadenectomy. Over the past decade, laparoscopic or robot-assisted minimally invasive surgery has showed many benefits in the management of endometrial cancer. Few studies have specifically assessed the use of minimally invasive surgery for staging of high risk endometrial cancer. The objective of this study was to evaluate the feasibility, the morbidity and oncologic outcomes of dual docking robot-assisted surgical staging of high risk endometrial cancer.
Methods:
We conducted a retrospective observational study from January 2014 to March 2016 in patients with high risk endometrial cancer who underwent dual docking robotic hysterectomy with pelvic and paraaortic lymphadenectomy (± omentectomy). Patients' demographics, operative time, conversion rate, intra and postoperative complications, pathologic results, length of stay and survival were analyzed.
Results:
Twenty patients met the inclusion criteria. Staging surgical procedure was performed robotically with a dual docking in 18 patients. Two patients were converted to laparotomy (1 for bladder extension, 1 for exposure reasons) and no patient had a laparoconversion for complication (conversion rate 10%). One patient was post operatively re-operated within 30 days because of port hernia. In one case, paraaortic lymphadenectomy was not performed because of hemorrhage risk. When the procedure was performed with robot-assisted surgery, the median number of paraaortic nodes was 19.5 (3-45). The median operative time was 240 min (180-300). Eighty-five percent (17/20) of patients were discharged at day 4 or before. The median time to start adjuvant treatments, when indicated, was 5.5 weeks. With a median follow up of 8 months (1-18 months), no tumor recurrence was reported.
Conclusion:
Robotic surgical staging with dual docking in women with high risk endometrial cancer seems to be feasible with few complications. More studies are required to assess the safety of robotic surgery and its impact on survival.
Related Concept Videos
 01:12
Relative Risk
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:26
Stages of Infection
 01:22
Stages of Sleep
Before sleep begins, in wakefulness, the brain exhibits primarily beta waves, which are high in frequency and low in amplitude, indicating alertness...
 01:22
Stages of General Anesthesia
 01:16
Psychosexual Stages of Personality: Oral
Weaning, typically occurring...