Related Experiment Video
Updated: Feb 11, 2026
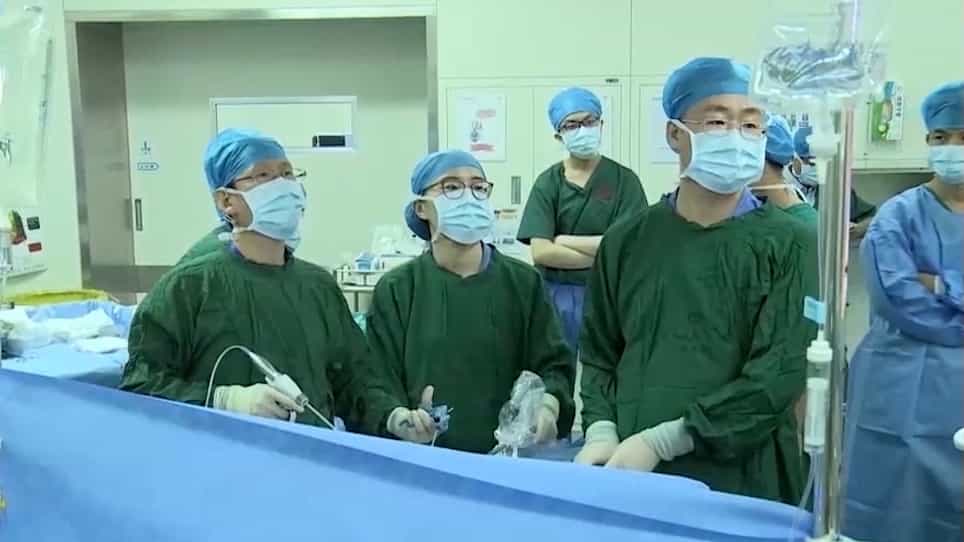

Laparoscopy-endoscopy Cooperative Surgery for the Treatment of Gastric Gastrointestinal Stromal Tumors
Published on: February 19, 2022
Surgery for metastatic gastrointestinal stromal tumor: to whom and how to?
Hirotoshi Kikuchi1, Yoshihiro Hiramatsu1, Kinji Kamiya1
1Second Department of Surgery, Hamamatsu, Japan.

Abstract:
Although imatinib is a standard treatment for metastatic or recurrent gastrointestinal stromal tumors (GISTs), acquired c-kit mutations reportedly cause secondary resistance to imatinib. Sunitinib is a tyrosine kinase inhibitor (TKI) that can be used as second-line therapy in imatinib-resistant or -intolerant GISTs. For sunitinib-resistant or -intolerant GISTs, regorafenib is a standard third-line treatment. Although TKI therapies have revolutionized the treatment of recurrent or metastatic GISTs, they cannot cure GISTs. Therefore, in the era of TKIs, role of cytoreductive surgery for recurrent or metastatic GISTs has been discussed. Retrospective studies of treatment strategies with front-line surgery prior to imatinib have shown that initial cytoreduction confers no benefit in cases of advanced or recurrent GIST, and administering imatinib is the principle treatment. Most retrospective studies report cytoreductive surgery to be feasible in patients with metastatic GIST whose disease is stable or responsive to imatinib. Cytoreductive surgery may be indicated in limited disease progression refractory to imatinib when complete resection is possible, but case selection is critical. Cytoreductive surgery for metastatic GIST treated with sunitinib seems less feasible because of high rates of incomplete resections and complications. The role of cytoreductive surgery for metastatic GISTs would be difficult to establish in a prospective study; individualized treatments need to be carefully designed based on c-kit and platelet-derived growth factor receptor alpha (PDGFRA) mutations and other factors.
Insights
Cytoreductive surgery is not beneficial for advanced gastrointestinal stromal tumors (GISTs) before imatinib treatment. Surgery may be considered for limited progression in GISTs responsive to imatinib, but is less feasible with sunitinib.
Area of Science:
- Oncology
- Surgical Oncology
- Gastrointestinal Cancer
Background:
- Imatinib is a standard treatment for metastatic or recurrent gastrointestinal stromal tumors (GISTs).
- Acquired c-kit mutations can lead to secondary resistance to imatinib.
- Sunitinib and regorafenib are used as second- and third-line therapies, respectively, for imatinib-resistant GISTs.
Purpose of the Study:
- To evaluate the role of cytoreductive surgery in the era of tyrosine kinase inhibitors (TKIs) for recurrent or metastatic GISTs.
- To determine the feasibility and benefit of cytoreductive surgery in different lines of TKI therapy for GISTs.
Main Methods:
- Review of retrospective studies on treatment strategies for metastatic or recurrent GISTs.
- Analysis of the impact of cytoreductive surgery in conjunction with TKI therapies (imatinib, sunitinib).
- Consideration of factors influencing surgical outcomes, including tumor response and mutational status (c-kit, PDGFRA).
Main Results:
- Front-line surgery prior to imatinib offers no benefit for advanced or recurrent GISTs.
- Cytoreductive surgery may be feasible for metastatic GISTs with limited progression refractory to imatinib, provided complete resection is possible.
- Surgical intervention with sunitinib is associated with higher rates of incomplete resection and complications, suggesting reduced feasibility.
Conclusions:
- Cytoreductive surgery is not recommended as an initial treatment for advanced GISTs.
- Individualized treatment decisions for cytoreductive surgery in metastatic GISTs should consider tumor response to TKIs, specific mutations (c-kit, PDGFRA), and the potential for complete resection.
- The role of cytoreductive surgery in sunitinib-treated GISTs requires further investigation due to feasibility concerns.


Related Concept Videos
 01:26
Anatomy of the Gastrointestinal System
Here's a detailed walkthrough of this complex system:
 01:20
Gastrointestinal Motility Disorders
 01:20
Histology of the Gastrointestinal (GI) Tract
The mucosa is sometimes called a mucous membrane due to its mucus-secreting features. This membrane is composed of epithelium, which directly interacts with ingested substances, and the lamina propria, a layer...
 01:22
Physiology of the Gastrointestinal System I: Ingestion and Propulsion
 01:22
Physiology of the Gastrointestinal System II: Digestion and Absorption
Digestion begins in the mouth, where food undergoes mechanical breakdown by chewing and combines with saliva. Salivary amylase, an enzyme in saliva, starts the breakdown of starches into maltose. The food then travels down the esophagus to the stomach.
In the stomach, a...
 01:26
Physiology of the Gastrointestinal System III: Elimination