Related Experiment Video
Updated: Feb 11, 2026

Minimal Invasive Resection of Large Retrosternal Thyroid Goiter
Published on: September 20, 2024
Minimally Invasive Resection of Deep-seated High-grade Gliomas Using Tubular Retractors and Exoscopic Visualization
Rajiv Iyer1, Kaisorn L Chaichana2
1Department of Neurosurgery, Johns Hopkins University, Baltimore, Maryland, United States.

Background And Study Aims/Objective:
Deep-seated high-grade gliomas (HGGs) represent a unique surgical challenge because they reside deep to critical cortical and subcortical structures and infiltrate functional areas of the brain. Therefore, accessing and resecting these tumors can often be challenging and associated with significant morbidity. We describe the use of minimally invasive approaches to access deep-seated HGGs to achieve extensive resections while minimizing surgical morbidity.
Materials And Methods:
All patients who underwent resection of a deep-seated intraparenchymal HGG with the use of a tubular retractor with exoscopic visualization from January 2016 to May 2017 were identified prospectively at a single institution. Variables evaluated included tumor location, pre- and postoperative neurologic function, extent of resection, and length of hospital stay.
Results:
Overall, 14 patients underwent resection of an HGG (11 glioblastomas, 3 anaplastic astrocytomas) with a tubular retractor under exoscopic visualization. Seven tumors (50%) involved the thalamus, three (21%) the motor corticospinal tract, two (14%) the inferior frontal occipital fasciculus, one (7%) each the basal ganglia and optic pathway. The median preoperative Karnofsky Performance Score (KPS) was 70 (interquartile range: 55-80), where the major presenting symptom was motor weakness in seven (50%). The average plus or minus the standard error of the mean percentage resection was 97.0 ± 1.2%. The median hospital stay was 4 days (range: 2-7). At 1 month postoperatively, median postoperative KPS (within 30 days) was 87 (range: 77-90), where eight (57%) were improved, five (36%) were stable, and one (7%) was worse postoperatively.
Conclusions:
Deep-seated HGGs can be accessed, visualized, and resected using tubular retractors and exoscopic visualization with minimal morbidity.

Related Concept Videos
 01:19
Graded Potential
Graded potentials fall into two categories: depolarizing and hyperpolarizing. Depolarizing graded potentials typically occur when sodium (Na+) or...
 01:45
Vesicular Tubular Clusters
With the help of motor proteins such...
 01:28
Tubular Reabsorption and Secretion
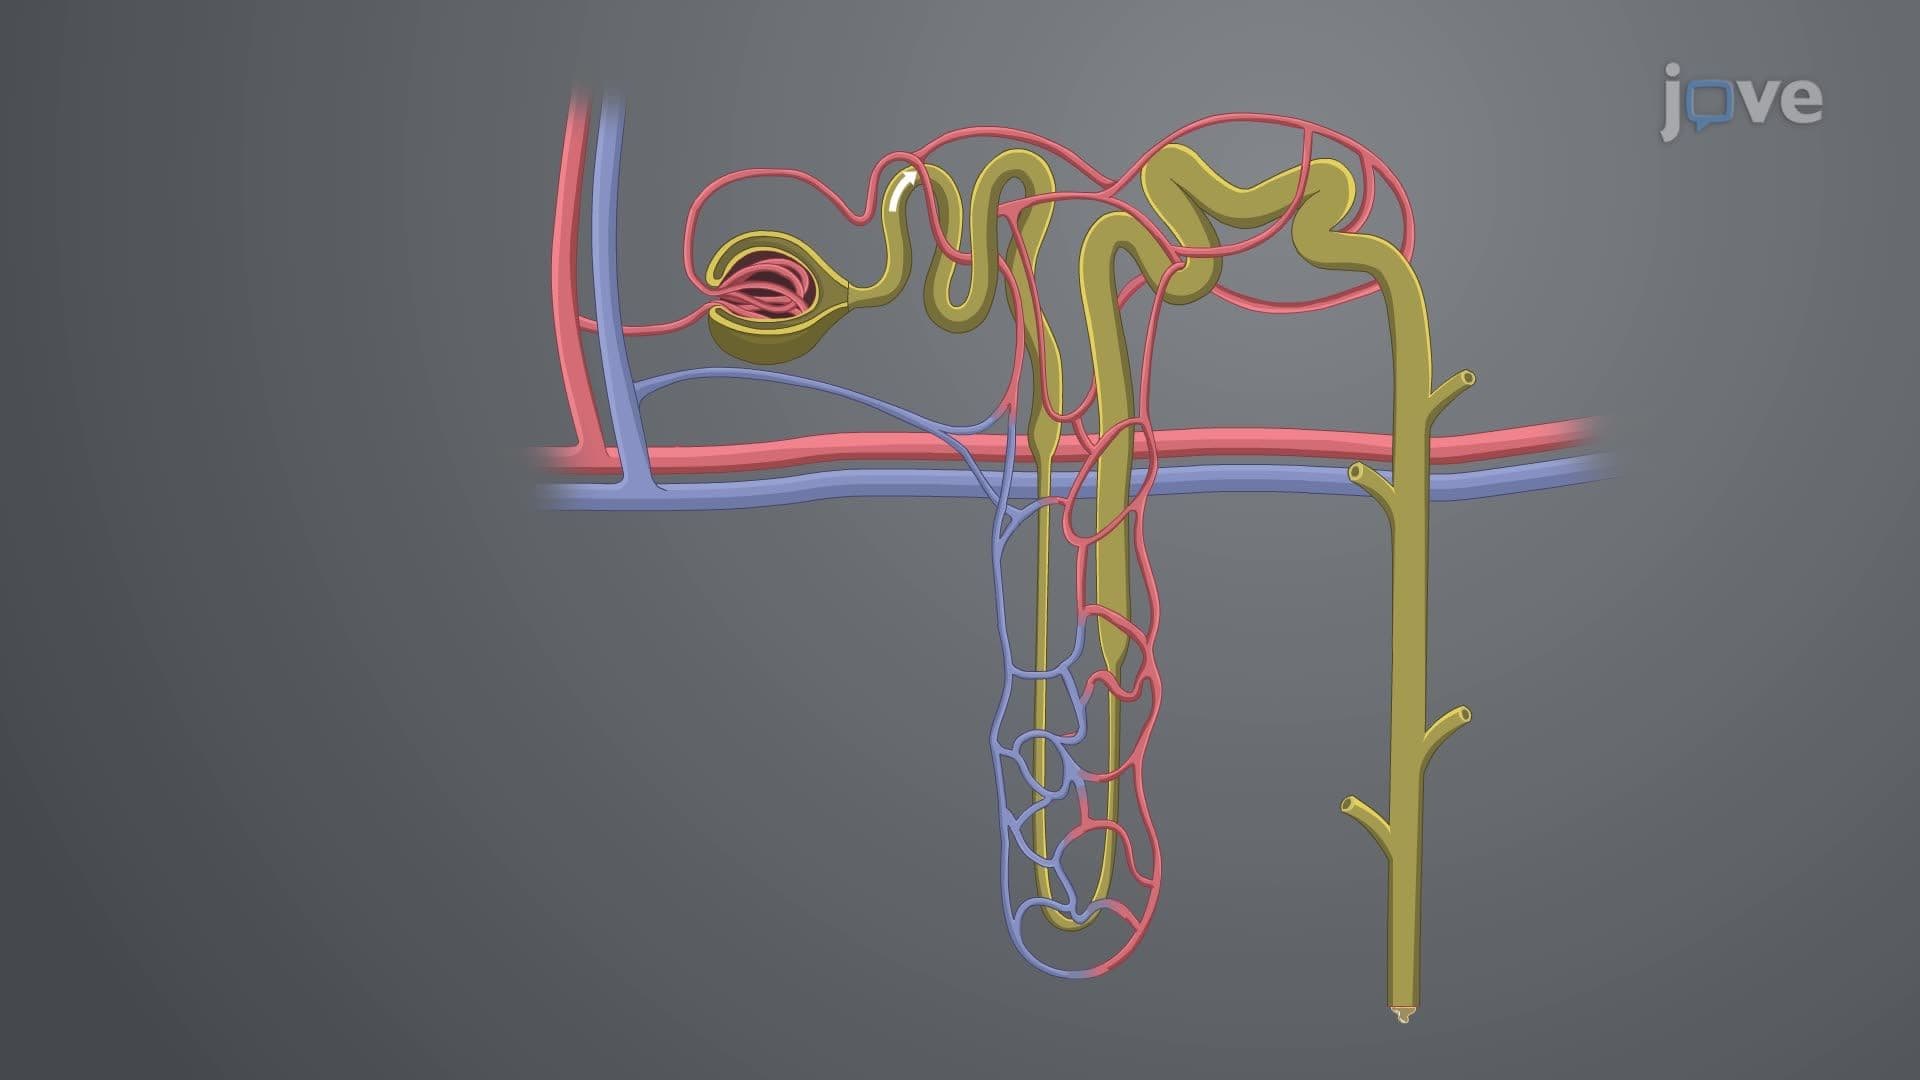
Tubular reabsorption is a selective process that starts when the filtrate enters the proximal tubules. It involves substances traveling through the transcellular route (through the tubule cell and peritubular...
 01:15
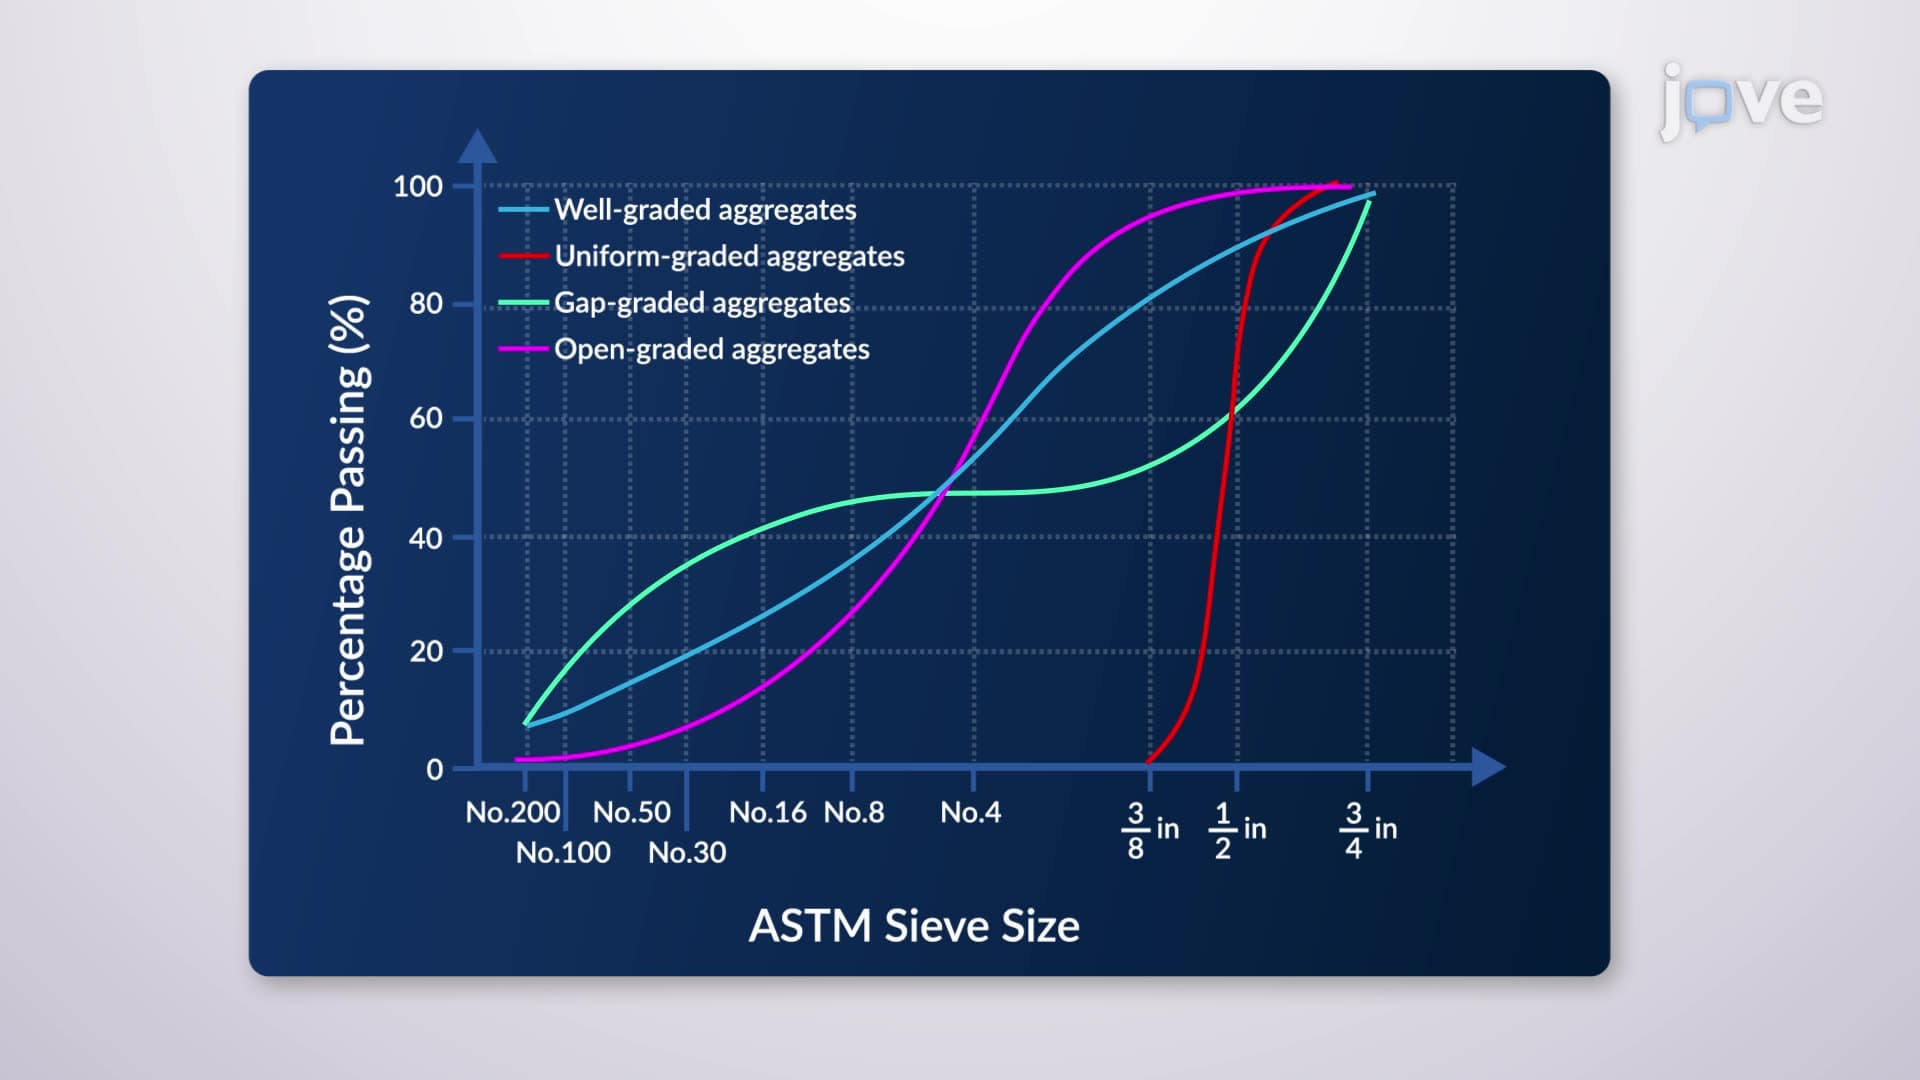
Types of Aggregate Grading
Well-graded aggregates include a complete range of necessary size fractions that fit together to create a dense matrix with minimal voids, represented by a smooth, continuous gradation curve. This type of grading ensures good...
 01:19
Sieve Analysis and Grading Curves
 01:22
Physiology of the Genitourinary System II: Tubular Reabsorption and Secretion