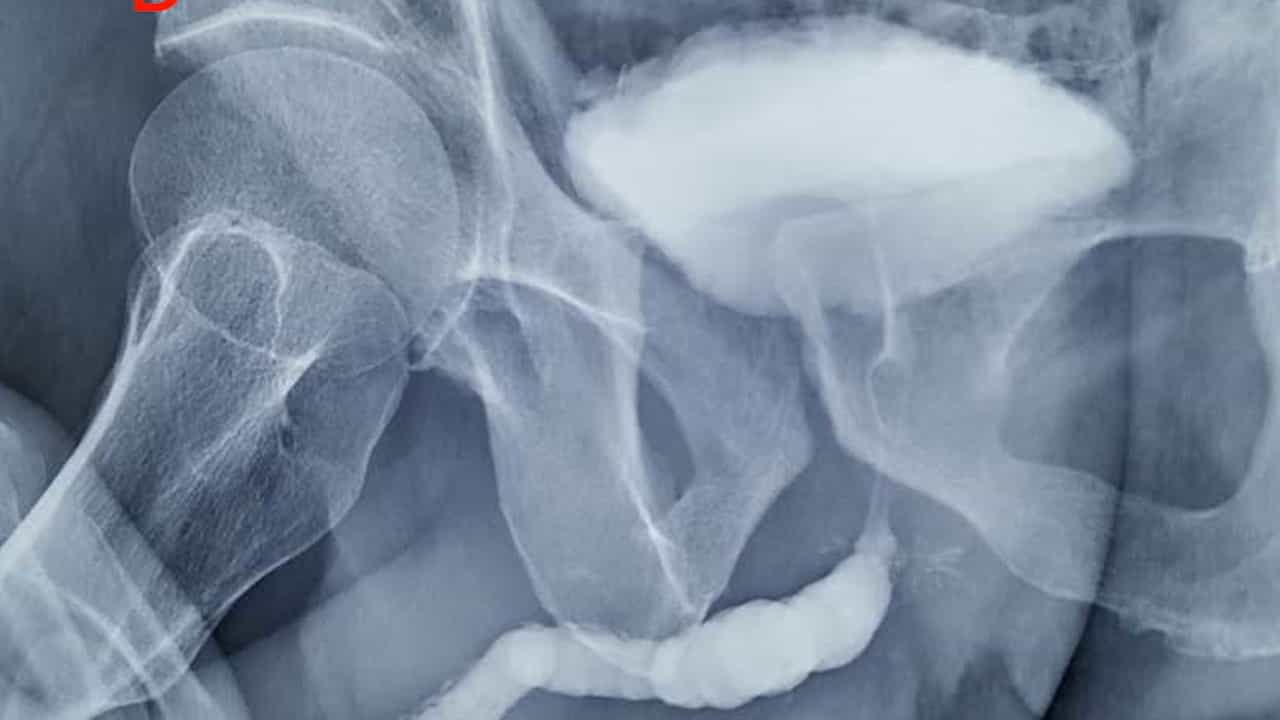

Management of a postbulbar duodenal ulcer and stricture causing gastric outlet obstruction: A case report
Maxwell D Mirande1, Raul A Mirande2
1OMS II at Western University of Health Sciences, College of Osteopathic Medicine of the Pacific-Northwest, 200 Mullins Drive, Lebanon, OR 97355, United States.

Introduction:
Peptic ulcer disease has significantly decreased over the past several decades making the need for definitive surgical intervention an infrequent occurrence.
Presentation Of Case:
A 44-year-old Caucasian female was sent to the emergency department by her primary care physician for right upper quadrant abdominal pain which had been intermittent for the past two months but acutely worsened over the last five days. During this time, she was unable to tolerate oral intake with intractable nausea and vomiting. Upper GI endoscopy revealed a tight stricture in the second part of the duodenum and antral biopsy was Helicobacter pylori negative. Patient underwent two rounds of balloon dilation with short lived symptomatic relief. An open pylorus-preserving duodenal stricturoplasty using a Heineke-Mikulicz technique was then performed. The operation was successful and the patient has had no reoccurrence of her symptoms.
Discussion:
Gastric outlet obstruction is an uncommon complication of peptic ulcer disease in respect to chronic nonsteroidal anti-inflammatory drug use. The unique location of the patient's stricture and her desire to minimize post-operative GI alterations demanded a review of surgical options and identified the benefits of maintaining the patient's original anatomy versus choosing an extra-anatomic approach.
Conclusion:
This case presented a unique challenge and demonstrated the need for definitive surgical interventions in the treatment of peptic ulcer induced gastric outlet obstruction. This case adds support for the direct anatomic treatment of duodenal strictures when conservative measures fail and perhaps promotes further development of laparoscopic management of gastric outlet obstruction in the future.
More Related Videos
 05:50
Author Spotlight: Point-of-Care Ultrasound for Gastric Content Assessment and Risk Stratification in Perioperative Care
Published on: September 22, 2023
 05:57
ADSC-sheet Transplantation to Prevent Stricture after Extended Esophageal Endoscopic Submucosal Dissection
Published on: February 10, 2017
Related Concept Videos
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
 01:29
Chronic Obstructive Pulmonary Disease-V: Management
Smoking Cessation
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:30
Chronic Obstructive Pulmonary Disease-V: Nursing Management
Assessment