Related Experiment Video
Updated: May 11, 2026


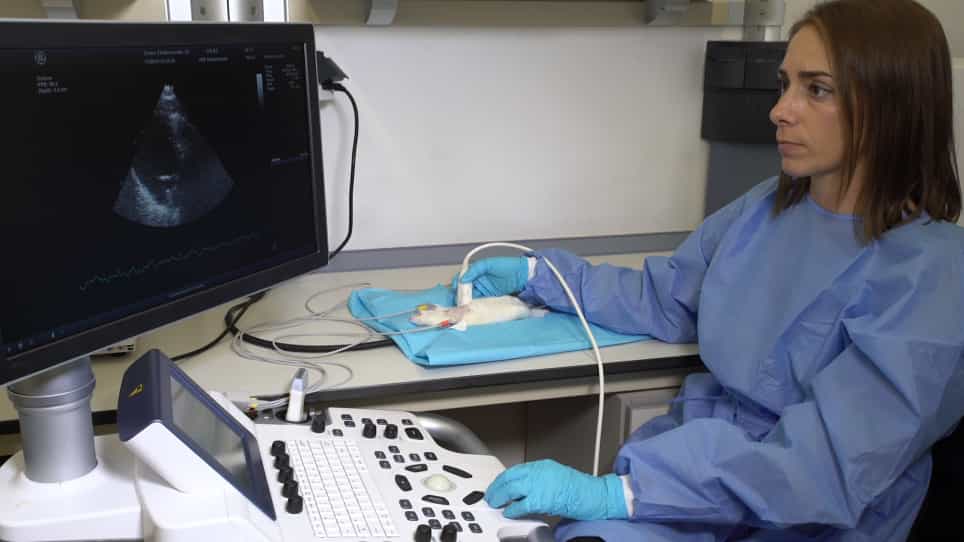
Echocardiographic Approaches and Protocols for Comprehensive Phenotypic Characterization of Valvular Heart Disease in Mice
Published on: February 14, 2017
Left ventricular systolic function in aortic stenosis
H P Krayenbuehl1, O M Hess, M Ritter
1Division of Cardiology, University Hospital, Zürich, Switzerland.

Insights
In aortic valve stenosis, left ventricular hypertrophy can be inadequate, leading to increased wall stress. This, along with reduced contractility, can lower ejection fraction, impacting patient outcomes.
Area of Science:
- Cardiology
- Cardiovascular Physiology
Background:
- Aortic valve stenosis (AVS) causes concentric left ventricular (LV) hypertrophy.
- Hypertrophy is considered appropriate when the radius-to-wall thickness ratio (r/h) and LV systolic pressure product remain constant, indicating normal wall stress.
Purpose of the Study:
- To investigate the relationship between LV hypertrophy, ejection fraction, and outcomes in aortic valve stenosis.
- To determine if ejection fraction is a reliable indicator of systolic myocardial function and a predictor of postoperative survival.
Main Methods:
- Literature review of 23 studies examining LV angiographic mass, ejection fraction, and myocardial structure.
- Analysis of preoperative LV angiographic mass and end-systolic volume as predictors of postoperative outcomes.
Main Results:
- An increased (r/h) x LV systolic pressure product signals inadequate LV hypertrophy and increased wall stress.
- An inverse relationship (r = -0.59) exists between ejection fraction and LV angiographic mass.
- Normal ejection fraction may be maintained by preload reserve despite reduced contractility.
- Myocardial structure analysis showed no differences between normal and depressed ejection fraction groups.
- Markedly increased preoperative LV mass and end-systolic volume predict poor postoperative outcomes.
Conclusions:
- Inadequate LV hypertrophy and reduced contractility can depress ejection fraction in AVS.
- Preoperative ejection fraction is a poor predictor of survival; LV mass and end-systolic volume are better indicators of prognosis.
Abstract:
In aortic valve stenosis, concentric hypertrophy develops which is characterized by a reduced end-diastolic radius-to-wall thickness ratio (r/h) with an essentially normal cavity shape. As long as the product of (r/h) and LV systolic pressure remains constant, hypertrophy is appropriate. An increase in the product, which represents an increase in wall stress signals inadequate LV hypertrophy. Although at first glance, massive LV hypertrophy appears favourable for the maintenance of a normal LV ejection fraction in aortic stenosis, data from 23 studies of the literature have shown an inverse relationship between ejection fraction and LV angiographic mass m-2 (r = -0.59). Both a degree of hypertrophy inadequate to keep systolic wall stress within normal limits and a reduction of LV contractility may explain the depression of ejection fraction when LV angiographic mass is sizeably increased. Conversely, a normal ejection fraction in aortic stenosis may not be indicative of normal systolic myocardial function under all circumstances. In the presence of mildly reduced contractility, a normal ejection fraction may be maintained by the use of preload reserve. Assessment of myocardial structure from LV endomyocardial biopsies revealed no differences in muscle fibre diameter, interstitial fibrosis and volume fraction of myofibrils between patients with aortic stenosis having a normal and those with a depressed ejection fraction. Preoperative ejection fraction is a poor predictor of postoperative survival, whereas markedly increased preoperative angiographic mass and end-systolic volume have been reported to predict an unsatisfactory postoperative outcome characterized by either death or poor LV function.

Related Concept Videos
 01:22
Mitral Stenosis I: Introduction
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:15
Aortic Regurgitation I: Introduction
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:25
Aortic Regurgitation III: Medical Management
 01:29
Heart Failure II: Pathophysiology