Related Experiment Video
Updated: Feb 11, 2026


Reproducable Paraplegia by Thoracic Aortic Occlusion in a Murine Model of Spinal Cord Ischemia-reperfusion
Published on: March 3, 2014
Fluctuations in Spinal Cord Perfusion Pressure: A Harbinger of Delayed Paraplegia After Thoracoabdominal Aortic
Harleen K Sandhu1, Jonathan D Evans1, Akiko Tanaka1
1Department of Cardiothoracic and Vascular Surgery, McGovern Medical School at The University of Texas Health Science Center at Houston (UTHealth), Houston, Texas.

Abstract:
Delayed paraplegia (DP) following thoracoabdominal or descending thoracic aortic (TAA/DTA) repair is a dreaded complication. We reviewed our experience with the management of DP using our previously described COPS protocol (blood-pressure stabilization, cerebrospinal-fluid (CSP) draining and O2-delivery). Complete documentation of hourly CSP pressures and detailed hemodynamic variables were available since 2000. A case-control design was used to analyze the extensive hourly data in the perioperative period. Data were analyzed by contingency-tables, t test, and regression analysis, as appropriate. Between 2000 and 2011, we performed 1059 TAA/DTA repairs. Of these, 47 (4.4%) had DP and 31 (2.9%) had immediate neurologic deficit. Postoperatively, renal replacement therapy and drain complications were significantly associated with DP. Variation in systolic blood pressure (SBP) was also highly predictive. Similarly, spinal-cord perfusion pressure (SCPP = SBP ? SP) showed increased risk with greater variability closer to event day (OR 1.3, P = 0.009). Fluctuation of more than 15 mmHg in SBP in a 24-hour period was associated with 3.2-fold increased odds of DP (P = 0.004). In all, 8/47 (17%) made a full recovery, whereas 19 (40%) had partial recovery by discharge. The 30-day mortality was 18/47 (38%) in DP and 7/55 (13%) in controls (P < 0.001). Long-term survival was significantly lower among DP cases (5-year survival of 28% vs. 75%, P < 0.001). DP occurs infrequently and is predictably associated with intraoperative loss of MEP, postoperative renal replacement therapy, drain complications and unstable systolic and spinal-cord perfusion pressures. Increased vigilance is recommended for patients who experience any of these events.


Related Concept Videos
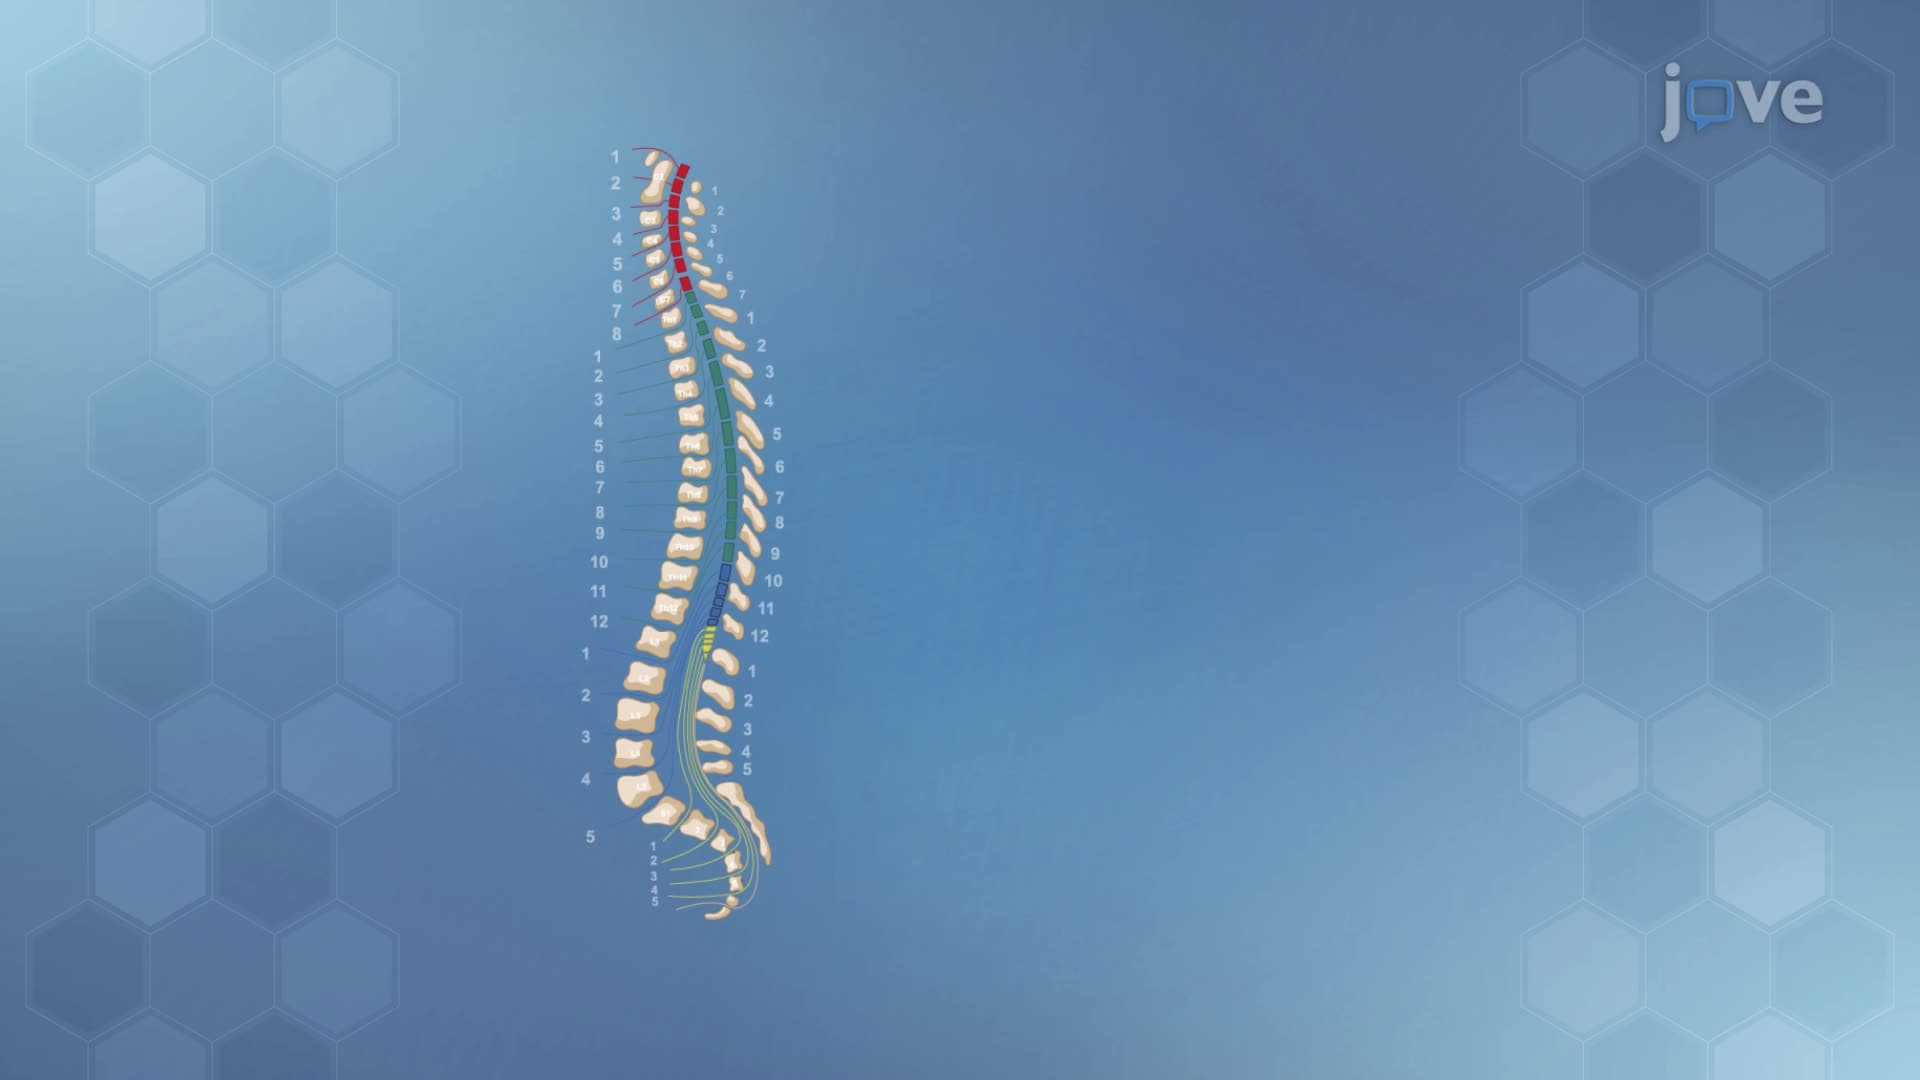 01:26
Spinal Cord
 01:54
The Spinal Cord
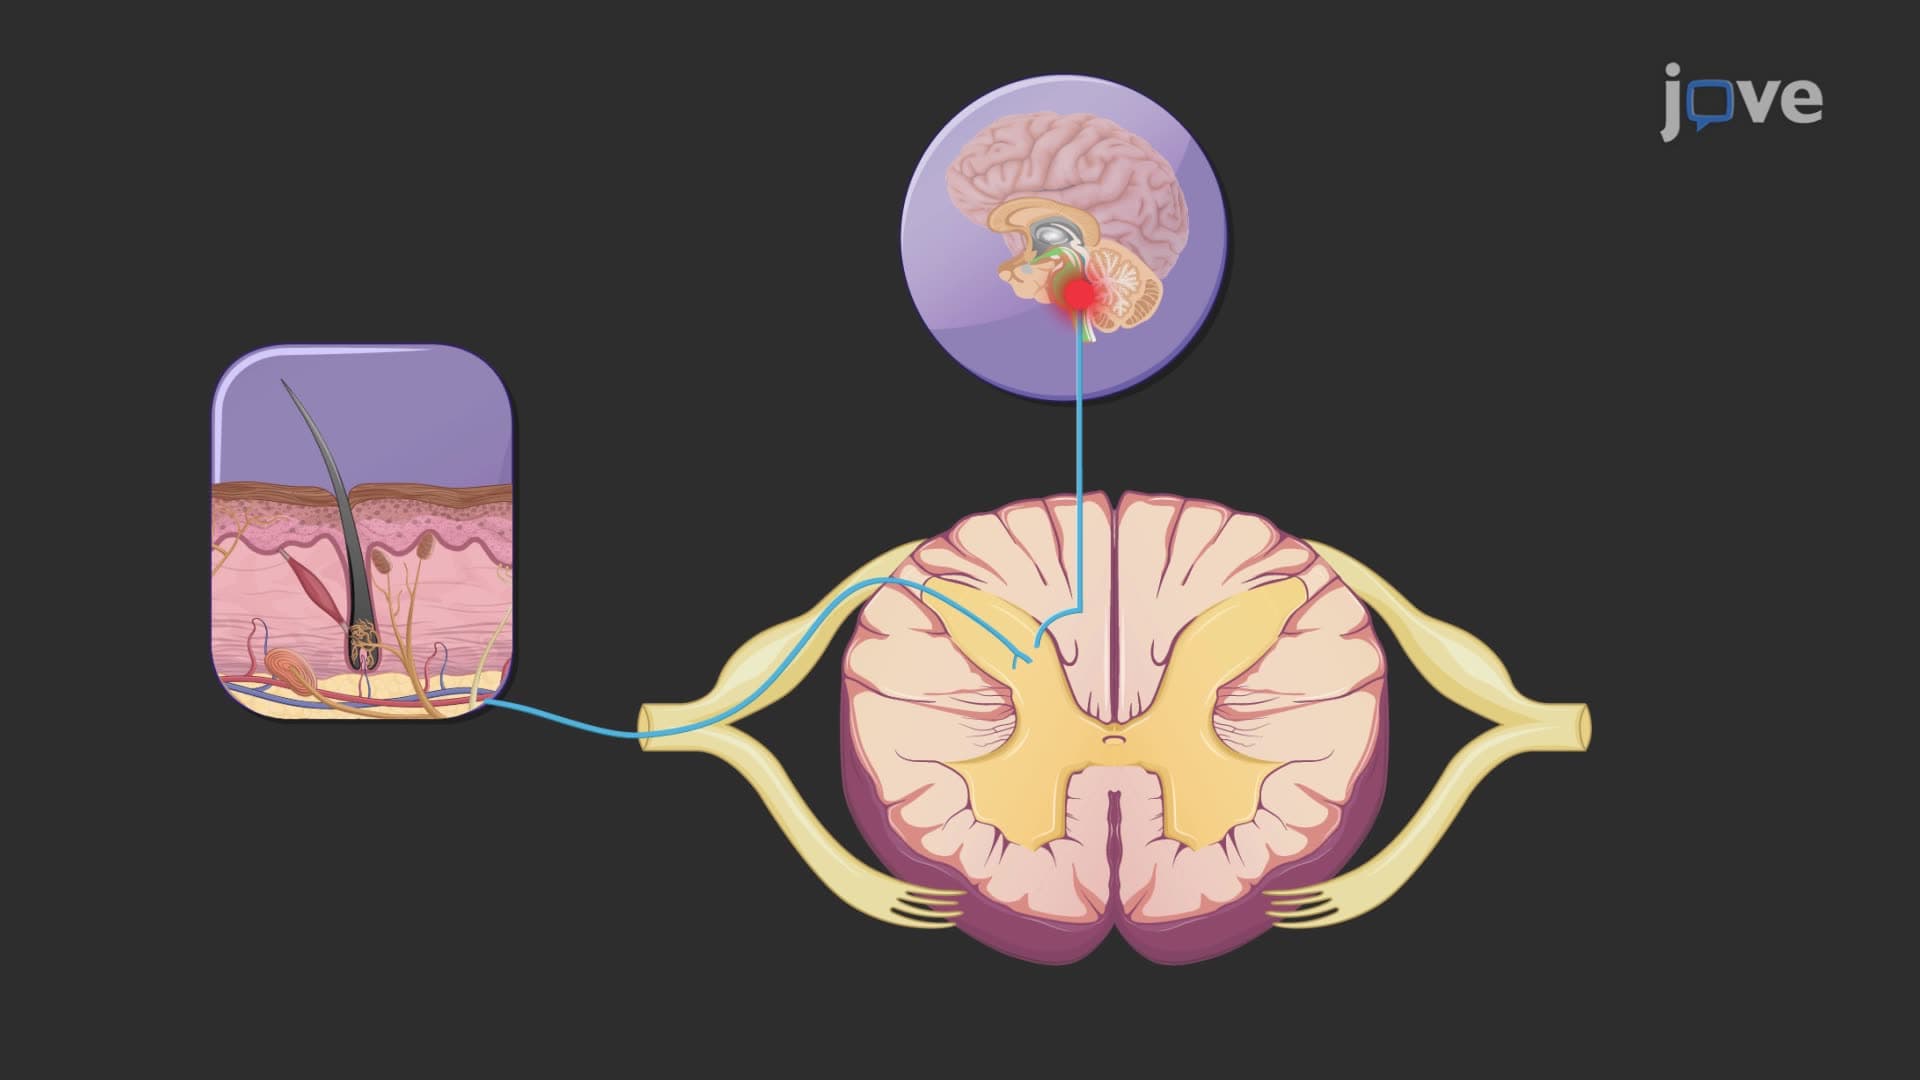 01:10
Spinal Cord: Information Processing
Sensory Information Processing
Sensory information processing begins at the sensory receptors located in the skin and other tissues, which detect somatic sensory stimuli such as touch, temperature, or pain. These receptors function as catalysts, initiating...
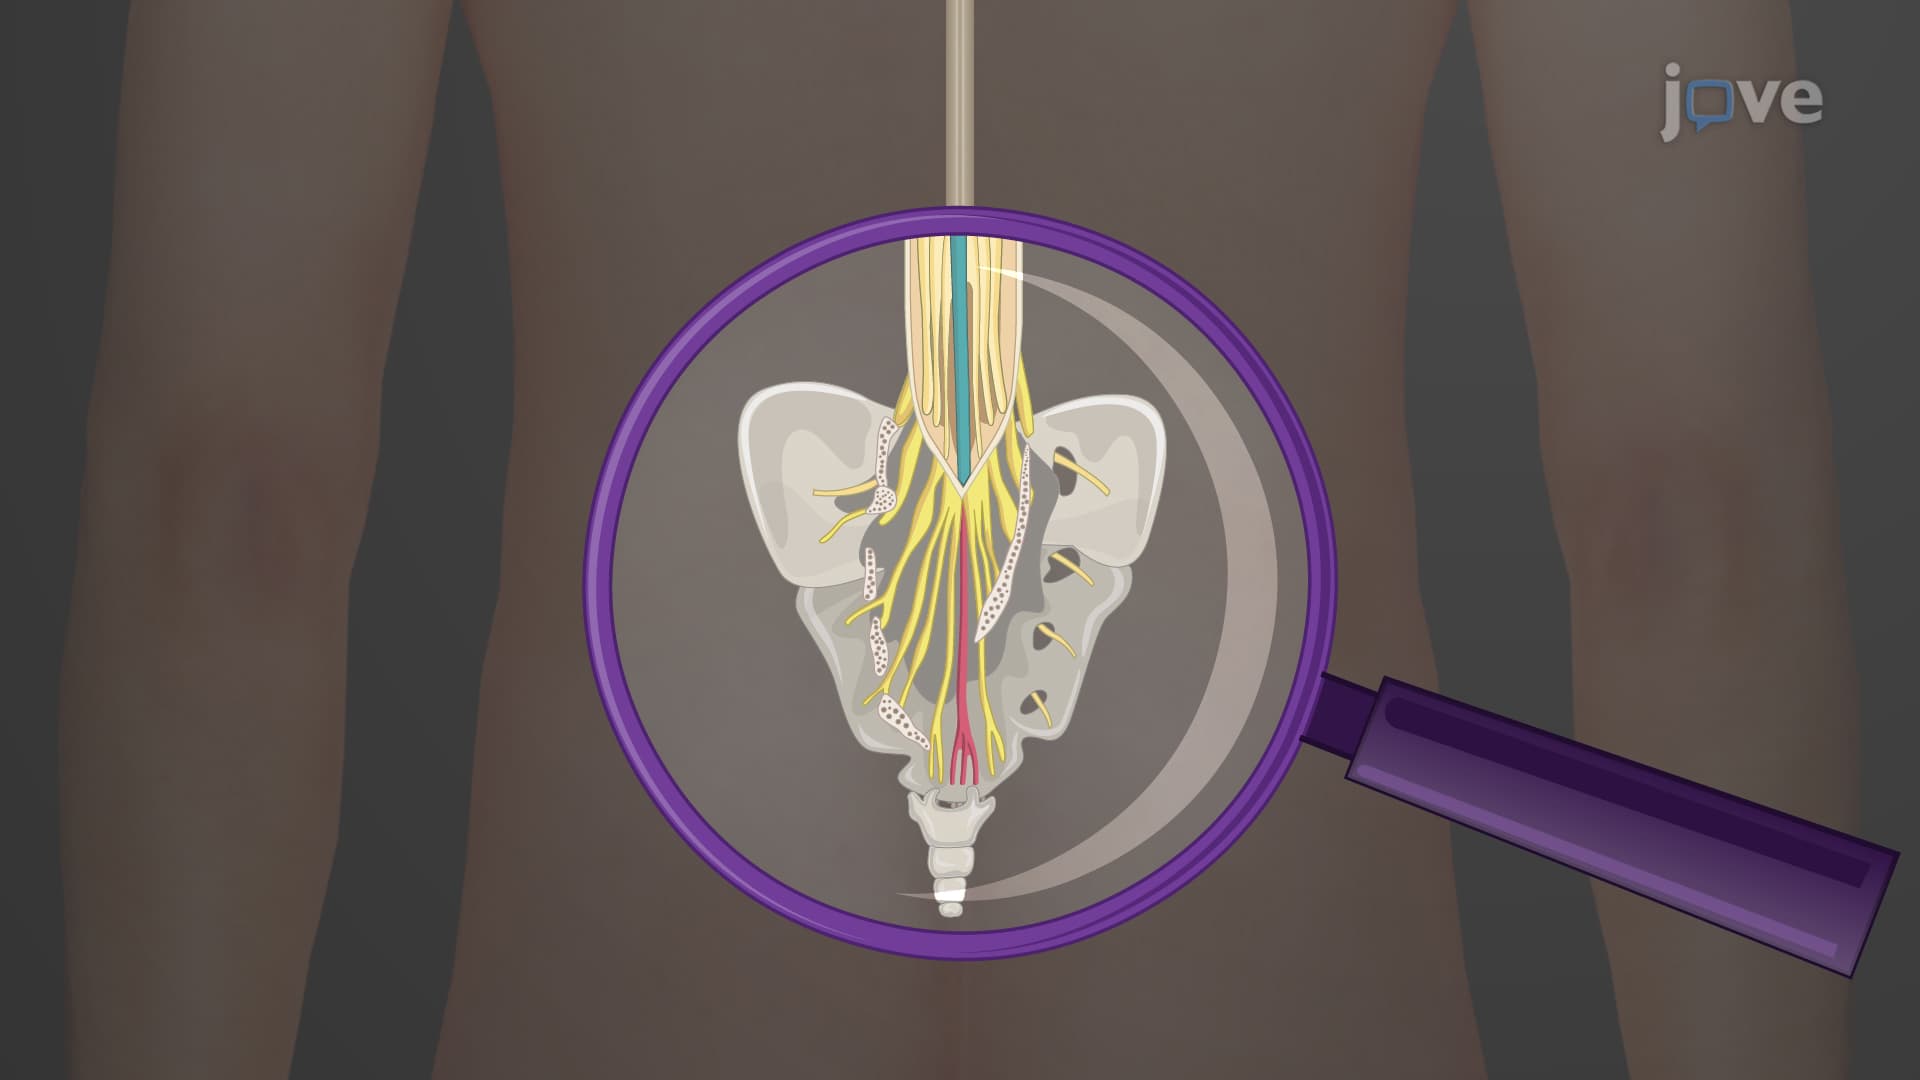 01:15
Spinal Cord: Gross Anatomy
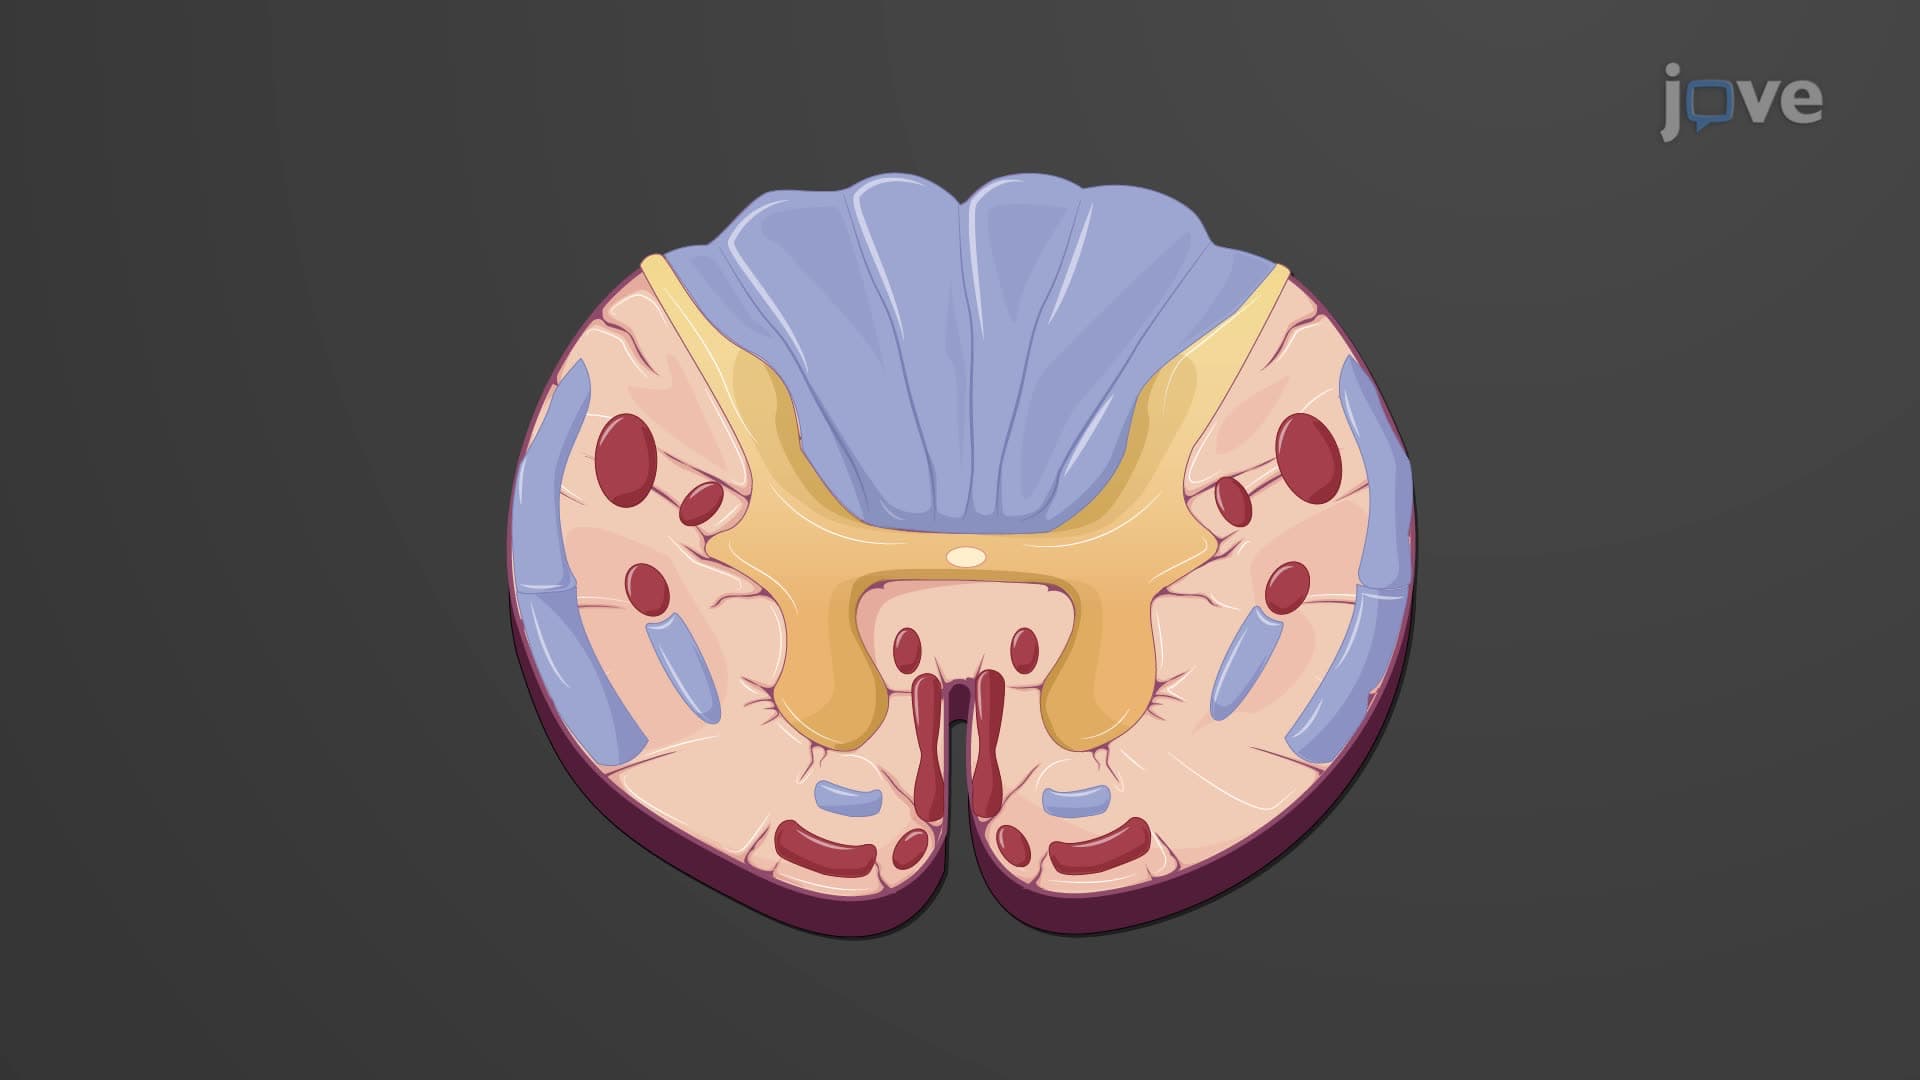 01:16
Spinal Cord: Cross-sectional Anatomy
Gray Matter and its Components
Central to the gray matter is...
 01:36
Mismatch Repair