Related Experiment Video
Updated: Feb 11, 2026
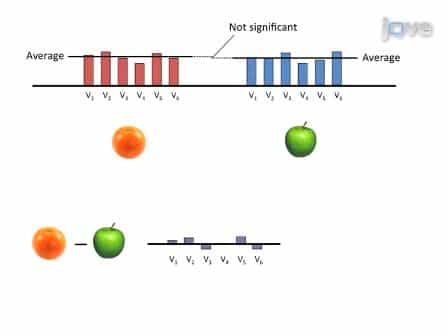
Cross-Modal Multivariate Pattern Analysis
Published on: November 9, 2011
Use of weighted multivariate estimates in trials of multi-serotype vaccines to simplify interpretation of treatment
Merryn Voysey1,2, Andrew J Pollard2,3, Rafael Perera1
1Nuffield Department of Primary Care Health Sciences, University of Oxford, Oxford, United Kingdom.

Background:
Many vaccines contain multiple components. Licensed pneumococcal conjugate vaccines (PCV) contain polysaccharides from 7, 10, or 13 different serotypes of Streptococcus pneumoniae. The main outcomes in randomised trials of pneumococcal vaccines are serotype-specific antibody measures. Comparisons are made between groups for each serotype, resulting in multiple separate comparisons of treatment effects which can be complicated to interpret. We investigated methods for computing the overall difference between vaccine groups across all serotypes.
Methods:
Pneumococcal antibody concentrations were obtained from a randomised controlled trial of ten-valent pneumococcal vaccine, conducted in Kathmandu, Nepal. Infants received either 2 priming doses of vaccine at 6 and 14 weeks of age followed by a booster (2+1), or 3 priming doses at 6, 10, and 14 weeks of age with no booster (3+0). The overall difference between vaccine schedules across all serotypes was computed at each visit using a multivariate linear model with equal weights for each serotype. Alternative weights were derived from invasive pneumococcal disease cases in Nepal, Bangladesh and Pakistan, and from estimates of the relative invasiveness of each serotype and used in sensitivity analyses.
Results:
When 10 separate estimates of treatment differences were computed the ratio of antibody responses for each serotype in the 2+1 group compared with the 3+0 group at 10 months of age varied greatly, with serotype-specific GMRs ranging from 2.80 for serotype 14, to 9.14 for serotype 18C. Using equal weights for each serotype, the overall geometric mean ratio (GMR) was 5.02 (95% CI 4.06-6.22) at 10 months of age, and 1.46 (95% CI 1.14-1.88) at 3 years of age. Using weights based on disease incidence gave GMRs ranging from 5.15 to 6.63 at 10 months of age, and 1.47 to 1.78 at 3 years of age. Using weights based on relative invasiveness gave estimates of 6.81 and 1.59, at 10 months and 3 years respectively.
Conclusion:
PCV clinical trial data have a multivariate structure with correlated outcomes for different serotypes. When analysing each serotype separately, the multiple estimates of the treatment effect can complicate the interpretation of trial results. Reporting a single overall estimate which accounts for the correlation between outcomes can simplify such interpretation. Treatment effects can be weighted equally or alternative weights derived from independent data can be used. Many modern vaccines have multiple components, such as quadrivalent meningococcal group ACWY vaccine or four-component group B meningococcal vaccine, thus these methods are widely applicable.
Related Concept Videos
 01:51
Vaccinations
 00:57
Weighted Mean
For example, consider the number of goals scored in the matches of a tournament. While computing the average number of goals scored in the tournament, it may be more important to...
 01:12
Trial and Error and Algorithm
 01:11
Clinical Trials: Overview
 01:16
Clinical Trials
There are four phases in a clinical trial. A phase one...
 01:06
What are Estimates?
The estimate for the mean of a sample is denoted by ͞x, whereas the mean of the population is designated as μ. Further, parameters such...