Related Experiment Video
Updated: Feb 11, 2026


Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
Analysis of Rothman Index Data to Predict Postdischarge Adverse Events in a Medical Intensive Care Unit
Deepa Bangalore Gotur1, Faisal Masud1, Jaya Paranilam1
1Department of Medicine, Houston Methodist Hospital, Houston Methodist, Fannin, Houston, Texas, USA.

Objective:
Currently, there are no objective metrics included in the intensive care unit (ICU) discharge decision making process. In this study, we evaluate Rothman Index(RI) data for a possible metric as part of a quality improvement project. Our objectives were to determine whether RI could predict adverse events occurring within 72 hours of ICU discharge decision, the optimal clinical cutoff value for this metric, and to determine whether there is a relation between the RI warning alert 24 hours prior to discharge and adverse events postdischarge.
Design:
Retrospective observational study.
Setting:
Single center tertiary hospital.
Patients:
Adult medical ICU patients discharged from the ICU between January 20, 2015 and March 14, 2015.
Interventions:
None.
Measurements And Main Results:
A total of 194 patients were studied with mean age of 62.74 (18.37) years. Data collection included RI at the time of decision-making for ICU discharge and the presence of any warning signals in the previous 24 hours. A 72-hour follow-up chart review recorded any adverse events, including readmission to a higher level of care, discontinuation of discharge due to clinical status change, emergency department visit if discharged home, rapid response activation, or cardiopulmonary arrest postdischarge. Adverse events after ICU discharge were observed in 31 (16%) patients with 9 events being ICU readmission (4.6%). Based on an age-adjusted multivariate model, a higher RI was associated with lower odds of an adverse event (odds ratio [OR] = 0.969, P = .006, confidence interval [CI]: 0.9487-0.9911). An RI value ≥ 50 was associated with 72% lower odds of an adverse event (OR = 0.2887, 95% CI = 0.1278-0.6517 and P = .003) compared to RI < 50. This RI cutoff value was associated with the largest decrease in odds of events. As expected, patients with a very high-risk warning alert had a higher proportion of adverse events compared to patients who did not. (31.75% vs 12.65%, P = < .02).
Conclusions:
Patients who have an RI < 50 or a very high-risk warning alert have a higher risk of adverse events postdischarge from the ICU. Rothman Index may be a useful metric for ICU discharge decision-making.
Related Concept Videos
 03:38
Measurement: Standard Units
 03:02
Measurement: Derived Units
 01:12
Analysis of Population Pharmacokinetic Data
 02:27
Predicting Molecular Geometry
 01:13
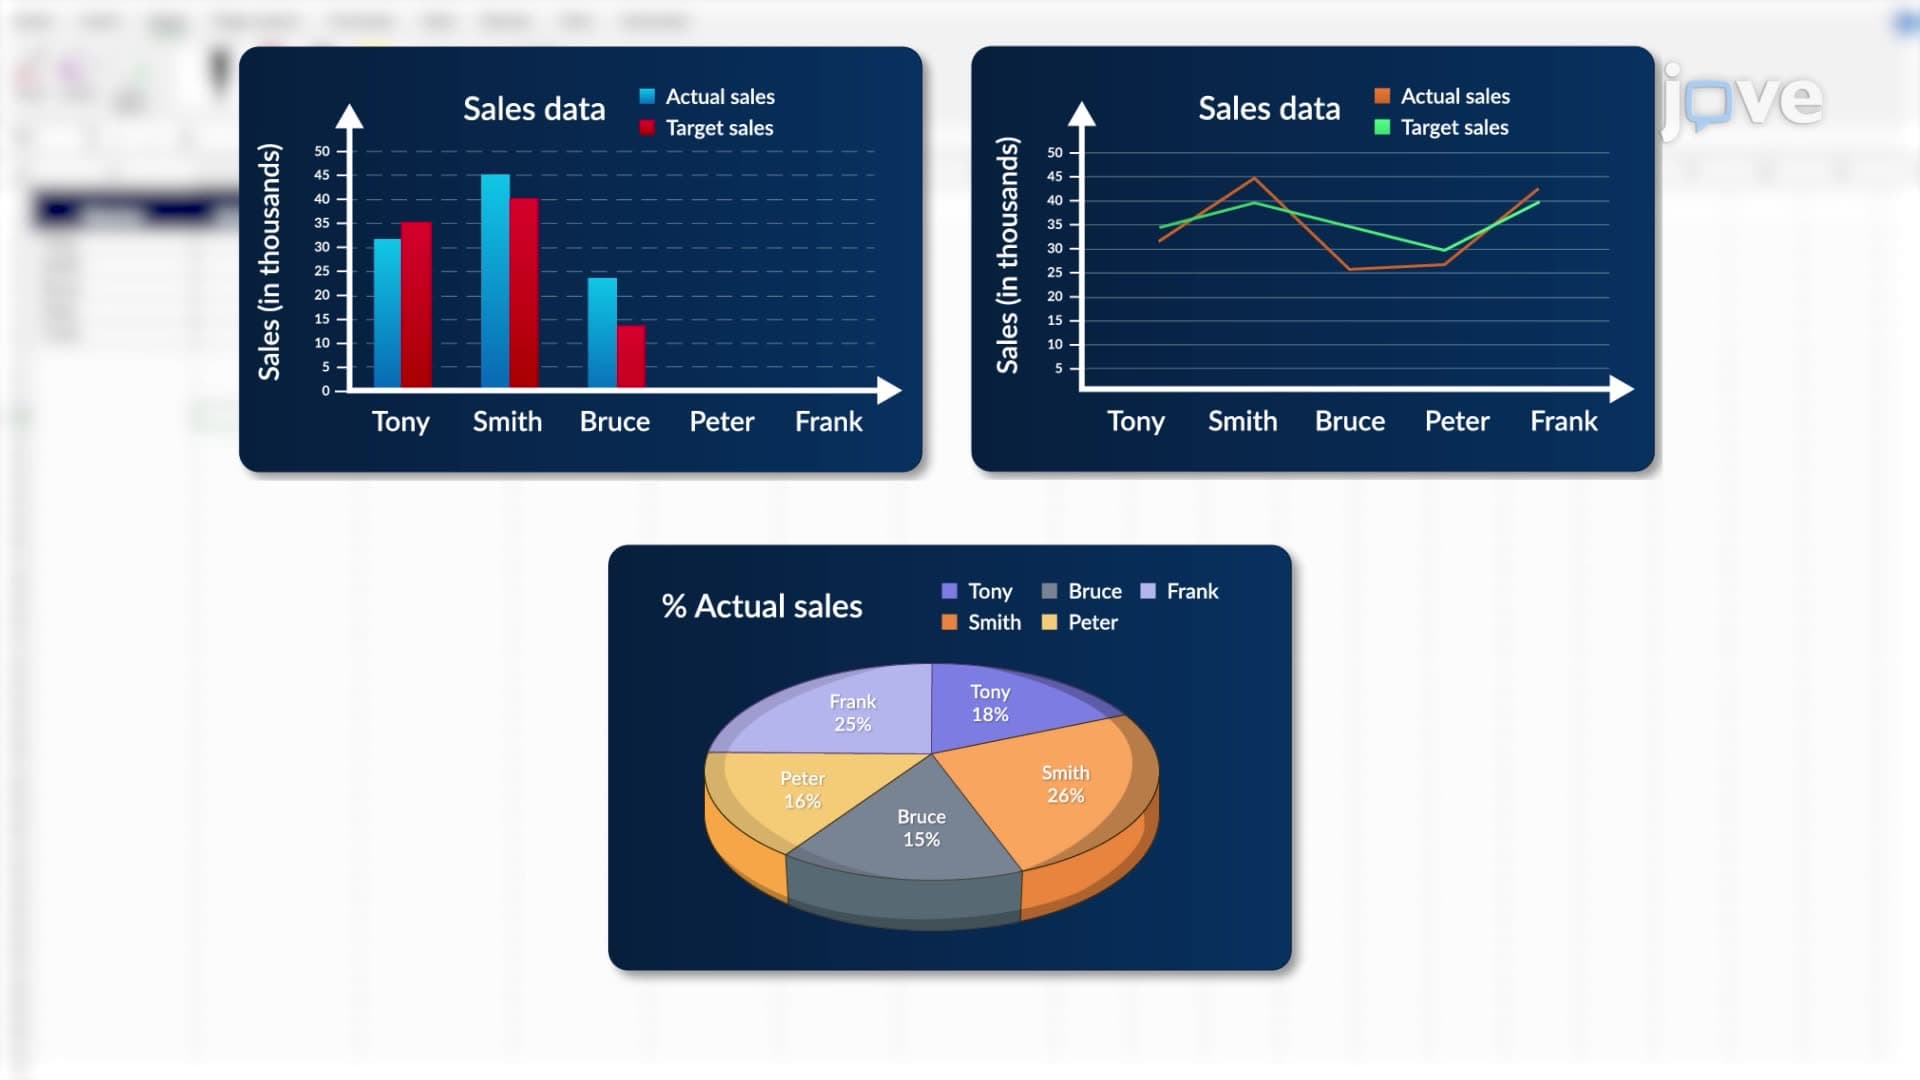
Overview of Microsoft Excel as a Data Analysis Tool
 00:58
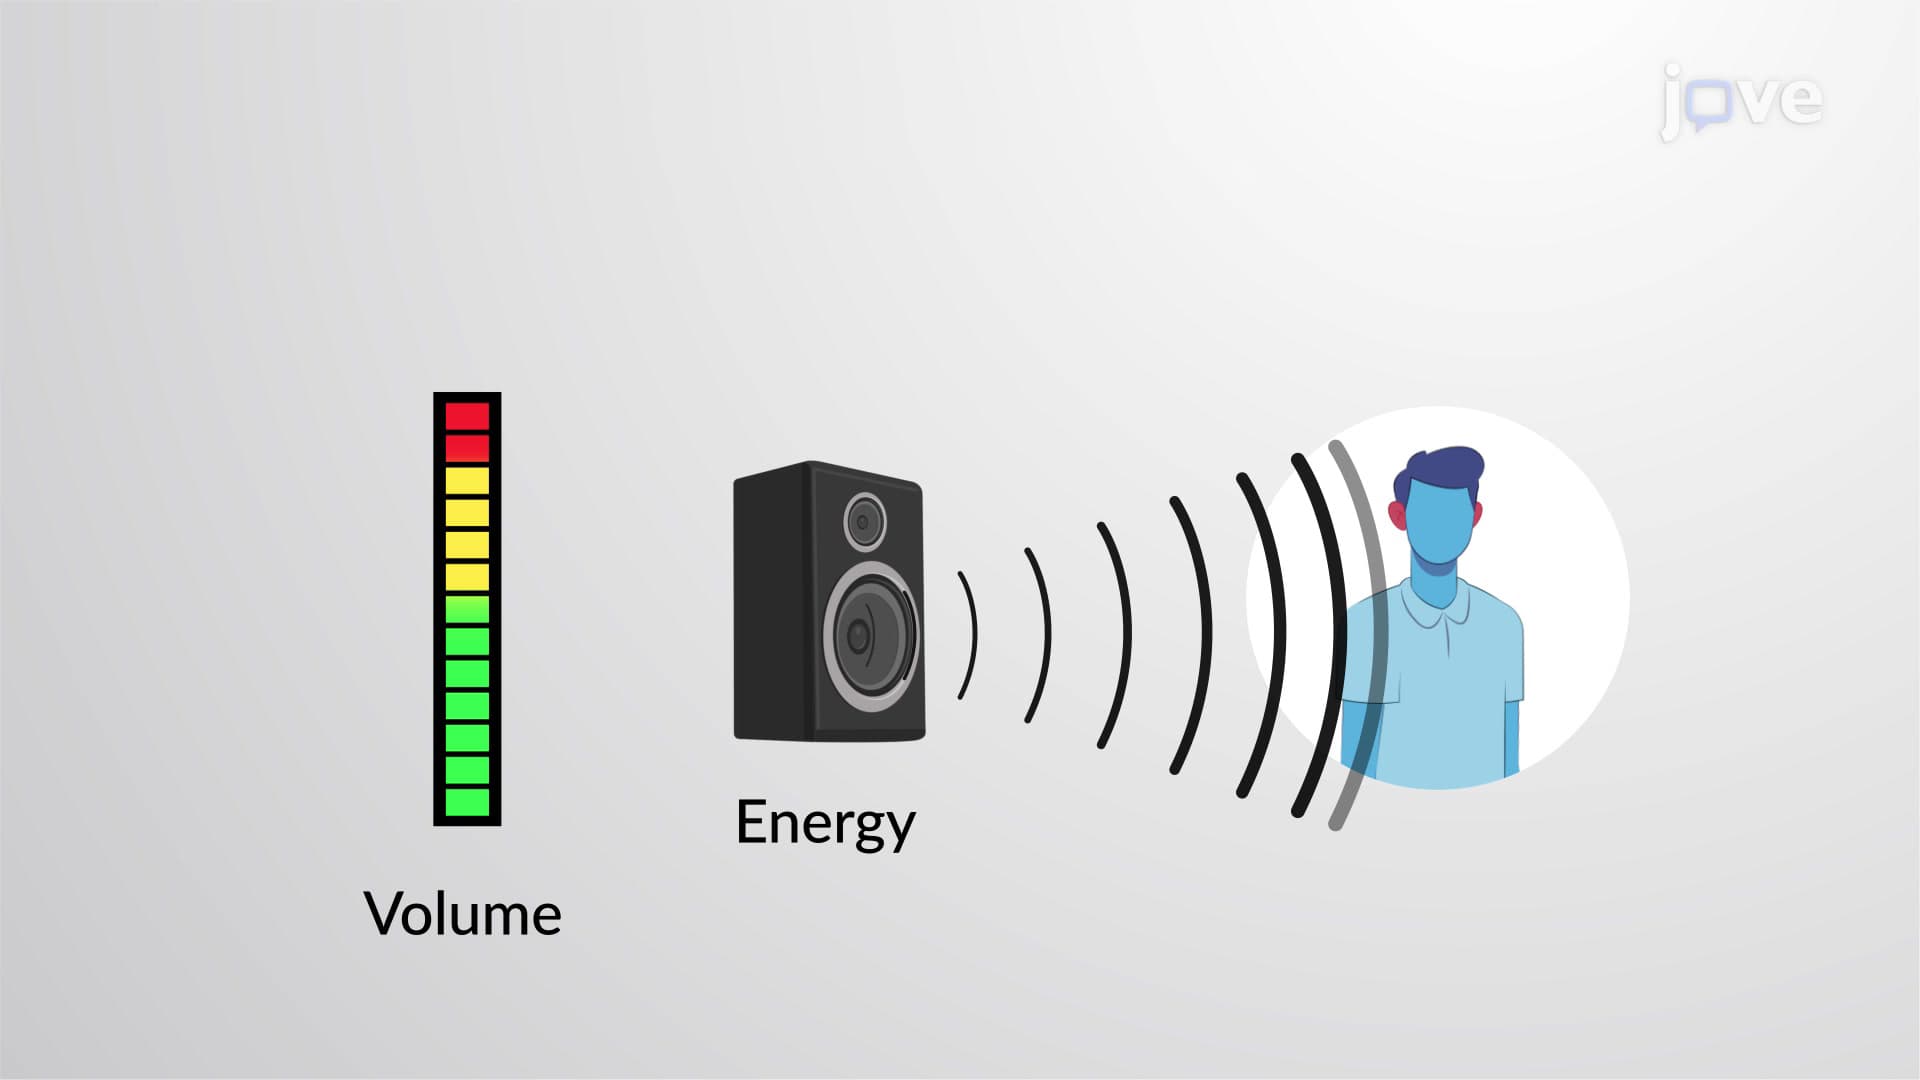
Sound Intensity