Related Experiment Video
Updated: Feb 11, 2026

Rapid Deletion Production in Fungi via Agrobacterium Mediated Transformation of OSCAR Deletion Constructs
Published on: June 12, 2017
Acquired thrombotic thrombocytopenic purpura with isolated CFHR3/1 deletion-rapid remission following complement
Martin Bitzan1, Rawan M Hammad2, Arnaud Bonnefoy3
1Division of Nephrology, Department of Pediatrics, Montreal Children's Hospital, McGill University Health Centre, Room B RC.6651, Montreal, Québec, H4A 3J1, Canada. martin.bitzan@mcgill.ca.

Background:
Thrombotic thrombocytopenic purpura (TTP) is caused by the abundance of uncleaved ultralarge von Willebrand factor multimers (ULvWF) due to acquired (autoantibody-mediated) or congenital vWF protease ADAMTS13 deficiency. Current treatment recommendations include plasma exchange therapy and immunosuppression for the acquired form and (fresh) frozen plasma for congenital TTP.
Case-Diagnosis/Treatment:
A previously healthy, 3-year-old boy presented with acute microangiopathic hemolytic anemia, thrombocytopenia, erythrocyturia and mild proteinuria, but normal renal function, and elevated circulating sC5b-9 levels indicating complement activation. He was diagnosed with atypical hemolytic uremic syndrome and treated with a single dose of eculizumab, followed by prompt resolution of all hematological parameters. However, undetectably low plasma ADAMTS13 activity in the pre-treatment sample, associated with inhibitory ADAMTS13 antibodies, subsequently changed the diagnosis to acquired TTP. vWF protease activity normalized within 15 months without further treatment, and the patient remained in long-term clinical and laboratory remission. Extensive laboratory workup revealed a homozygous deletion of CFHR3/1 negative for anti-CFH antibodies, but no mutations of ADAMTS13, (other) alternative pathway of complement regulators or coagulation factors.
Conclusions:
This case, together with a previous report of a boy with congenital TTP (Pecoraro et al. Am J Kidney Dis 66:1067, 2015), strengthens evolving in-vitro and ex-vivo evidence that ULvWF interferes with complement regulation and contributes to the TTP phenotype. Comprehensive, prospective complement studies in patients with TTP may lead to a better pathophysiological understanding and novel treatment approaches for acquired or congenital forms.
Related Concept Videos
 01:29
Neuromuscular Junction And Blockade
 01:27
Complement System
 00:49
Complementation Tests
Organisms heterozygous for different mutations are crossed pairwise in all combinations. If present on different genes, the mutations can complement each other by providing the missing...
 02:15
SN1 Reaction: Stereochemistry
In the first step of an SN1 reaction, the bond between the electrophilic carbon and the leaving group ionizes to generate the carbocation intermediate. The second step of the mechanism is the nucleophilic attack.
In the formed carbocation, the positively charged carbon is sp2 hybridized with a trigonal planar geometry. As all the three substituents lie on the same plane, a plane of symmetry for the...
 02:05
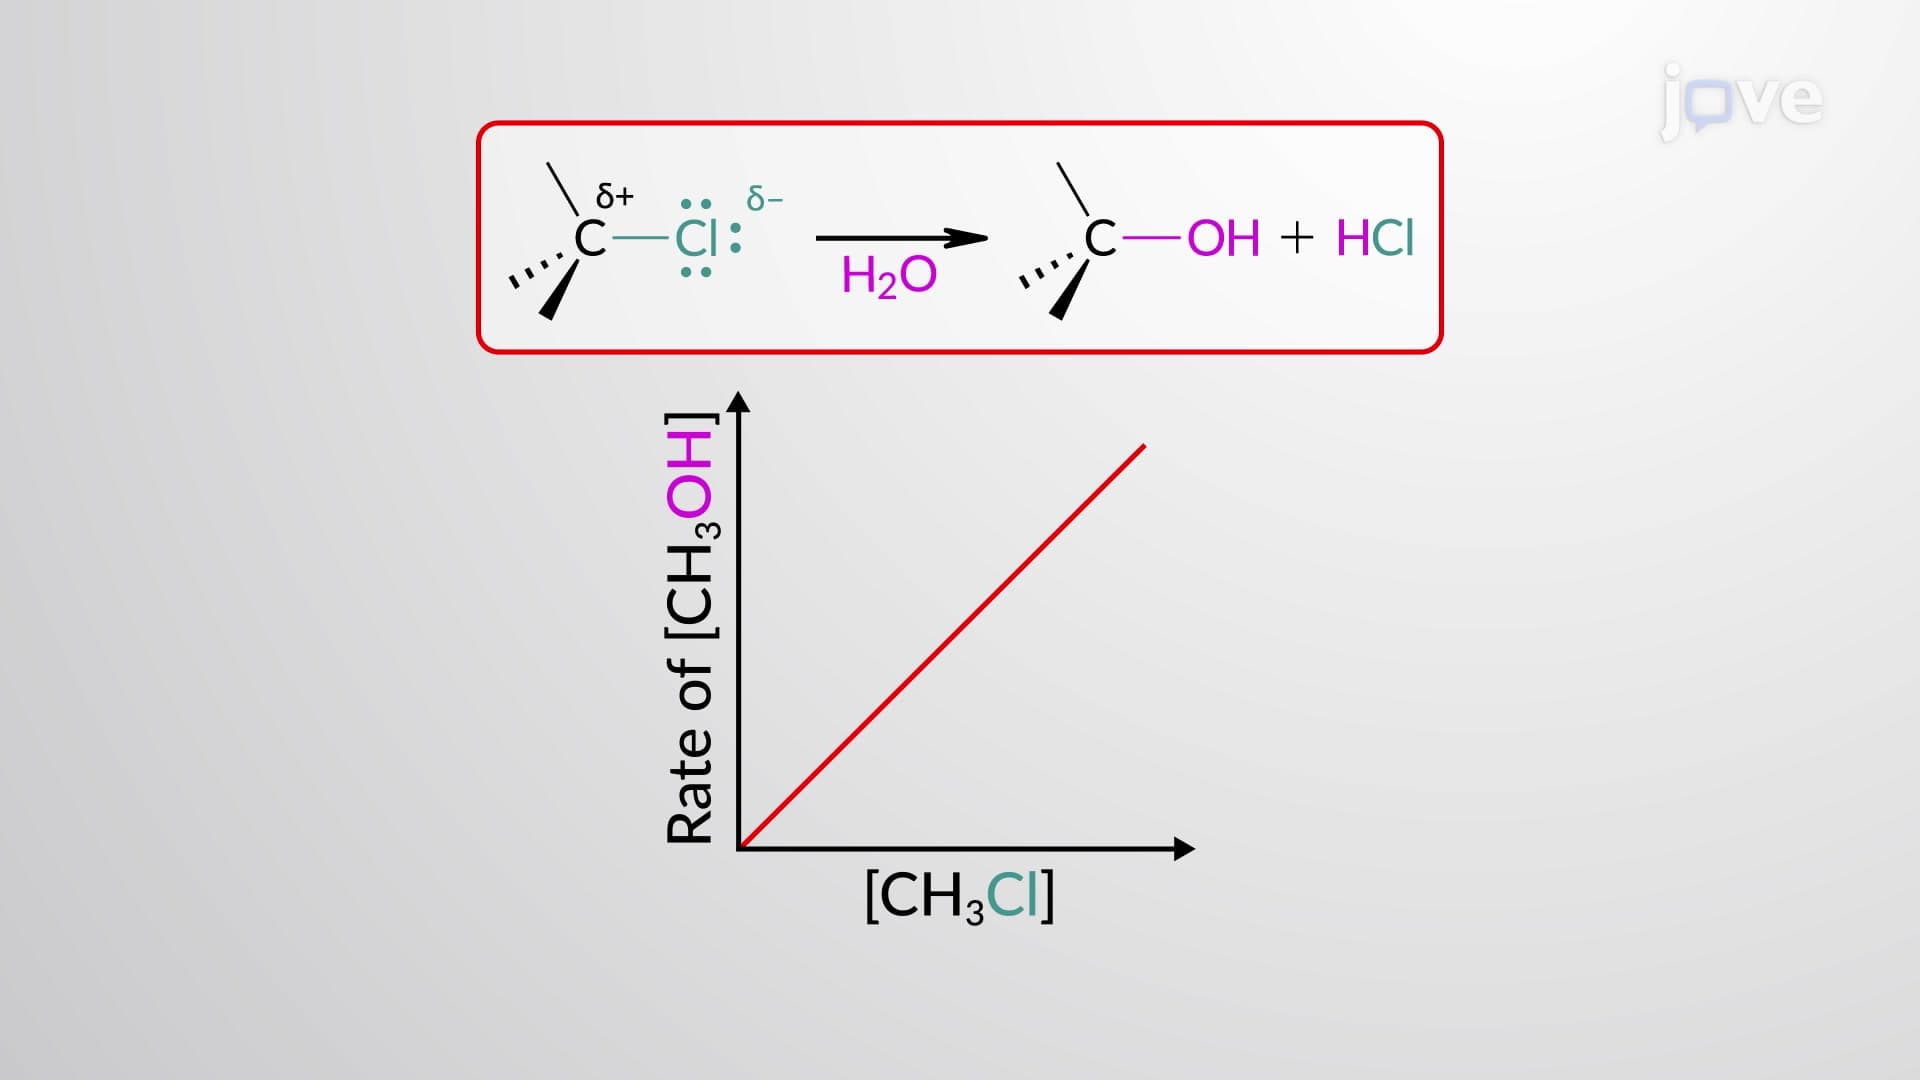
SN1 Reaction: Kinetics
However, Sir Christopher Ingold and Edward D. Hughes, who studied the kinetics of various nucleophilic substitution reactions, noticed that a tertiary alkyl halide does undergo a nucleophilic substitution reaction in the presence of a weak nucleophile. While studying the substitution...
 02:25
SN1 Reaction: Mechanism
Firstly, the haloalkane ionizes to generate a carbocation intermediate and a halide ion. This heterolytic cleavage is highly endothermic with large activation energy. The ionization of the substrate, facilitated by a...