Related Experiment Video
Updated: Feb 11, 2026
Author Spotlight: Cutting-Edge Robotic Heller Myotomy Protocol for Treatment of Achalasia
Published on: February 16, 2024
Genesis of Esophageal Pressurization and Bolus Flow Patterns in Patients With Achalasia Esophagus
Subum Park1, Ali Zifan2, Dushyant Kumar2
1Department of Internal Medicine, Pusan National University School of Medicine, Pusan National University Yangsan Hospital, Yangsan, South Korea; Department of Medicine, Division of Gastroenterology, University of California, San Diego, California.

Background & Aims:
In patients with achalasia esophagus, swallows induce simultaneous pressure waves known as esophageal pressurization. We studied the mechanism of esophageal pressurization and bolus flow patterns in patients with type 2 or type 3 achalasia.
Methods:
We recorded high-resolution manometry with impedance and intraluminal ultrasound images concurrently in patients with type 2 achalasia (n = 6) or type 3 achalasia (n = 8) and in 10 healthy subjects (controls) during swallows of 5 mL of 0.5N saline. For each swallow, the ultrasound image was aligned with the pressure and impedance tracings to determine cavity and contact pressure, bolus arrival, bolus dwell time, and changes in muscle thickness at 5 cm and 10 cm above the lower esophageal sphincter.
Results:
In patients with type 2 achalasia, esophageal pressurization was associated with an increase in the muscle thickness and luminal narrowing but not complete luminal closure (ie, cavity pressure). Bolus arrival time in the distal esophagus after the onset of a swallow was delayed in patients with type 3 achalasia compared with control individuals because of early luminal closure. The early luminal closure was associated with a decrease in the muscle thickness. The bolus dwell time was shorter in patients with type 3 achalasia compared with control individuals. In patients with type 3 achalasia, the onset of simultaneous pressure wave was always a cavity pressure, but during contraction there were different periods of cavity and contact pressures in association with increases in muscle thickness that resulted in bolus segmentation.
Conclusions:
We observed distinct mechanisms of esophageal pressurization and bolus flow patterns in patients with type 2 or type 3 achalasia esophagus compared with control individuals. These findings will increase our understanding of the mechanisms of dysphagia.

Related Concept Videos
 01:24
Esophagus
The movement of edibles from the pharynx into the esophagus is facilitated by the upper esophageal sphincter, which is formed primarily by the...
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more...
 01:24
Esophageal Varices-I: Introduction
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:18
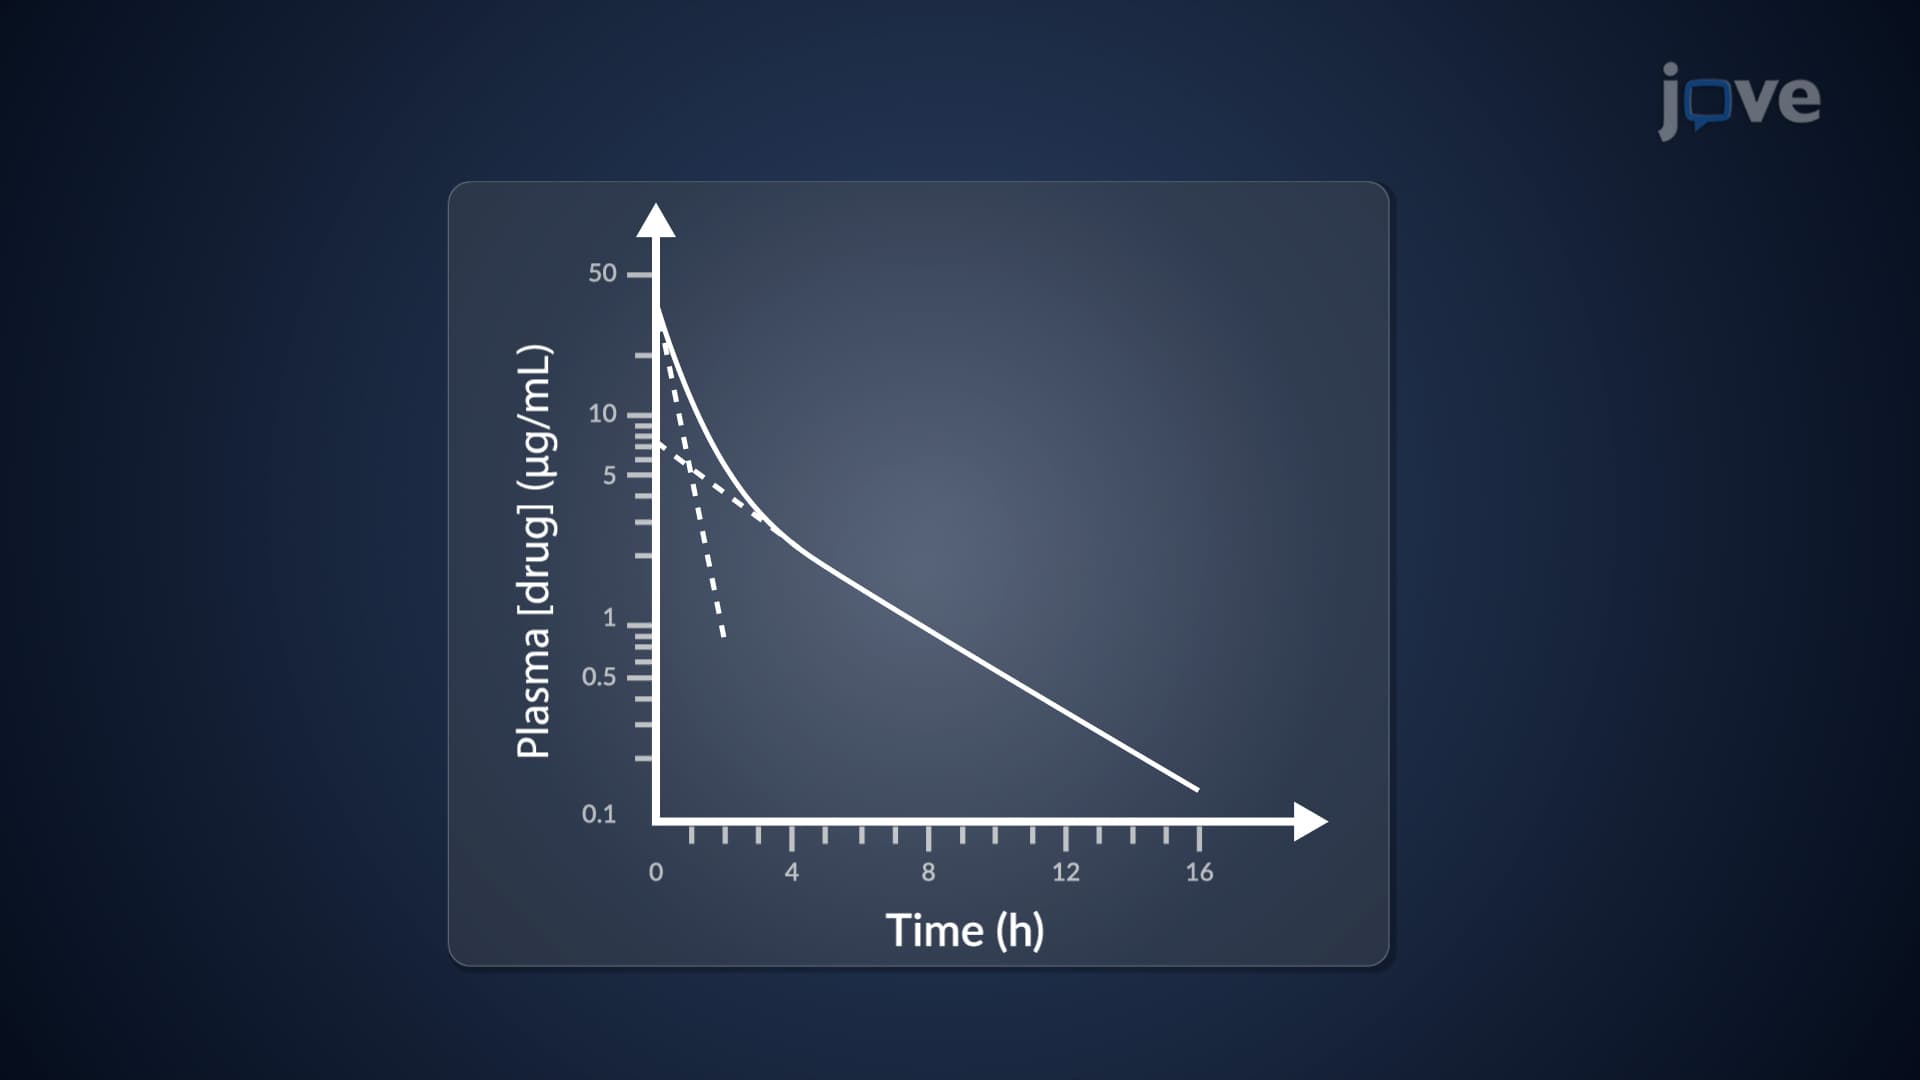
Two-Compartment Open Model: IV Bolus Administration
The disparity between drug input and the sum of drug transfer rates between...