Related Experiment Video
Updated: Feb 10, 2026


Postconditioning with Lactate-enriched Blood for Cardioprotection in ST-segment Elevation Myocardial Infarction
Published on: May 28, 2019
Modifiable factors associated with prolonged door to balloon time in patients with ST-segment elevation myocardial
Masahiko Noguchi1,2, Junya Ako3, Takeshi Morimoto4
1Department of Cardiology, Tokyo Bay Urayasu Ichikawa Medical Center, 3-4-32 Todaijima, Urayasu, Chiba, 279-0001, Japan. m_nogu_18@yahoo.co.jp.

Insights
Reducing door to balloon time is crucial for ST-segment elevation myocardial infarction (STEMI) patients. Key modifiable factors include ECG to puncture time, door to ECG time, and puncture to balloon time.
Area of Science:
- Cardiology
- Interventional Cardiology
- Emergency Medicine
Background:
- Door to balloon (D2B) time is a critical determinant of clinical outcomes for ST-segment elevation myocardial infarction (STEMI) patients undergoing primary percutaneous coronary intervention (PCI).
- While numerous factors influence D2B time, modifiable factors require further investigation to optimize treatment pathways.
Purpose of the Study:
- To identify specific, modifiable factors contributing to prolonged D2B times in STEMI patients.
- To provide insights for improving treatment efficiency and patient outcomes in primary PCI settings.
Main Methods:
- Retrospective analysis of 239 consecutive STEMI patients treated with primary PCI between April 2013 and September 2016.
- Comparison of patients with D2B time >90 minutes versus D2B time ≤90 minutes.
- Multivariable logistic regression to identify modifiable factors associated with prolonged D2B time.
Main Results:
- The median D2B time was 69 minutes, with 24% of patients exceeding 90 minutes.
- Significant modifiable factors for prolonged D2B time (>90 min) included: ECG to puncture time >50 min (OR 96.0), door to ECG time >10 min (OR 49.8), and puncture to balloon time >30 min (OR 48.5).
- ECG to puncture time >50 minutes emerged as the most impactful modifiable factor.
Conclusions:
- Optimizing the time from ECG acquisition to arterial puncture is paramount for reducing D2B times in STEMI patients.
- Targeting specific procedural delays, such as door to ECG and puncture to balloon times, can significantly improve primary PCI efficiency.
- Streamlining inter-departmental workflows and communication is essential for minimizing D2B delays and enhancing STEMI care.
Abstract:
Door to balloon (D2B) time was reported an important factor of the clinical outcome of patients with ST-segment elevation myocardial infarction (STEMI) treated with primary percutaneous coronary intervention (PCI). D2B time is influenced by various factors; however, modifiable factors have not been adequately evaluated. The purpose of this study was to identify modifiable factors associated with prolonged D2B time. We historically included 239 consecutive STEMI patients who visited emergency department and underwent primary PCI between April 2013 and September 2016. We evaluated baseline characteristics, mode and timing of hospital arrival, symptoms and signs, treatment times and angiographic characteristics. Patients with D2B time > 90 min were compared with those with D2B time ≤ 90 min. Modifiable factors associated with prolonged D2B time (> 90 min) were analyzed by multivariable logistic regression model. The median D2B time for the entire cohort was 69 min (interquartile range 54-89) and 24% had a D2B time of > 90 min. Modifiable factors associated with prolonged treatment time (D2B time > 90 min) were electrocardiogram (ECG) to puncture time > 50 min [odds ratios (OR) 96.0, 95% confidence intervals (95% CI) 25.1-652.5, P < 0.0001), door to ECG time > 10 min (OR 49.8, 95% CI 11.8-357.5, P < 0.0001), and puncture to balloon time > 30 min (OR 48.5, 95% CI 12.0-333.8, P < 0.0001). ECG to puncture time > 50 min was the most important modifiable factor associated with prolonged D2B time in STEMI patients.
More Related Videos
 18:11
A Research Method For Detecting Transient Myocardial Ischemia In Patients With Suspected Acute Coronary Syndrome Using Continuous ST-segment Analysis
Published on: December 28, 2012
 05:52
Myocardial Infarction by Percutaneous Embolization Coil Deployment in a Swine Model
Published on: November 4, 2021
Related Concept Videos
 01:29
Factors Affecting Protein-Drug Binding: Patient-Related Factors
Age stands as a key determinant in protein-drug binding. Neonates, characterized by low albumin content, experience heightened concentrations of unbound drugs such as phenytoin and...
 03:12
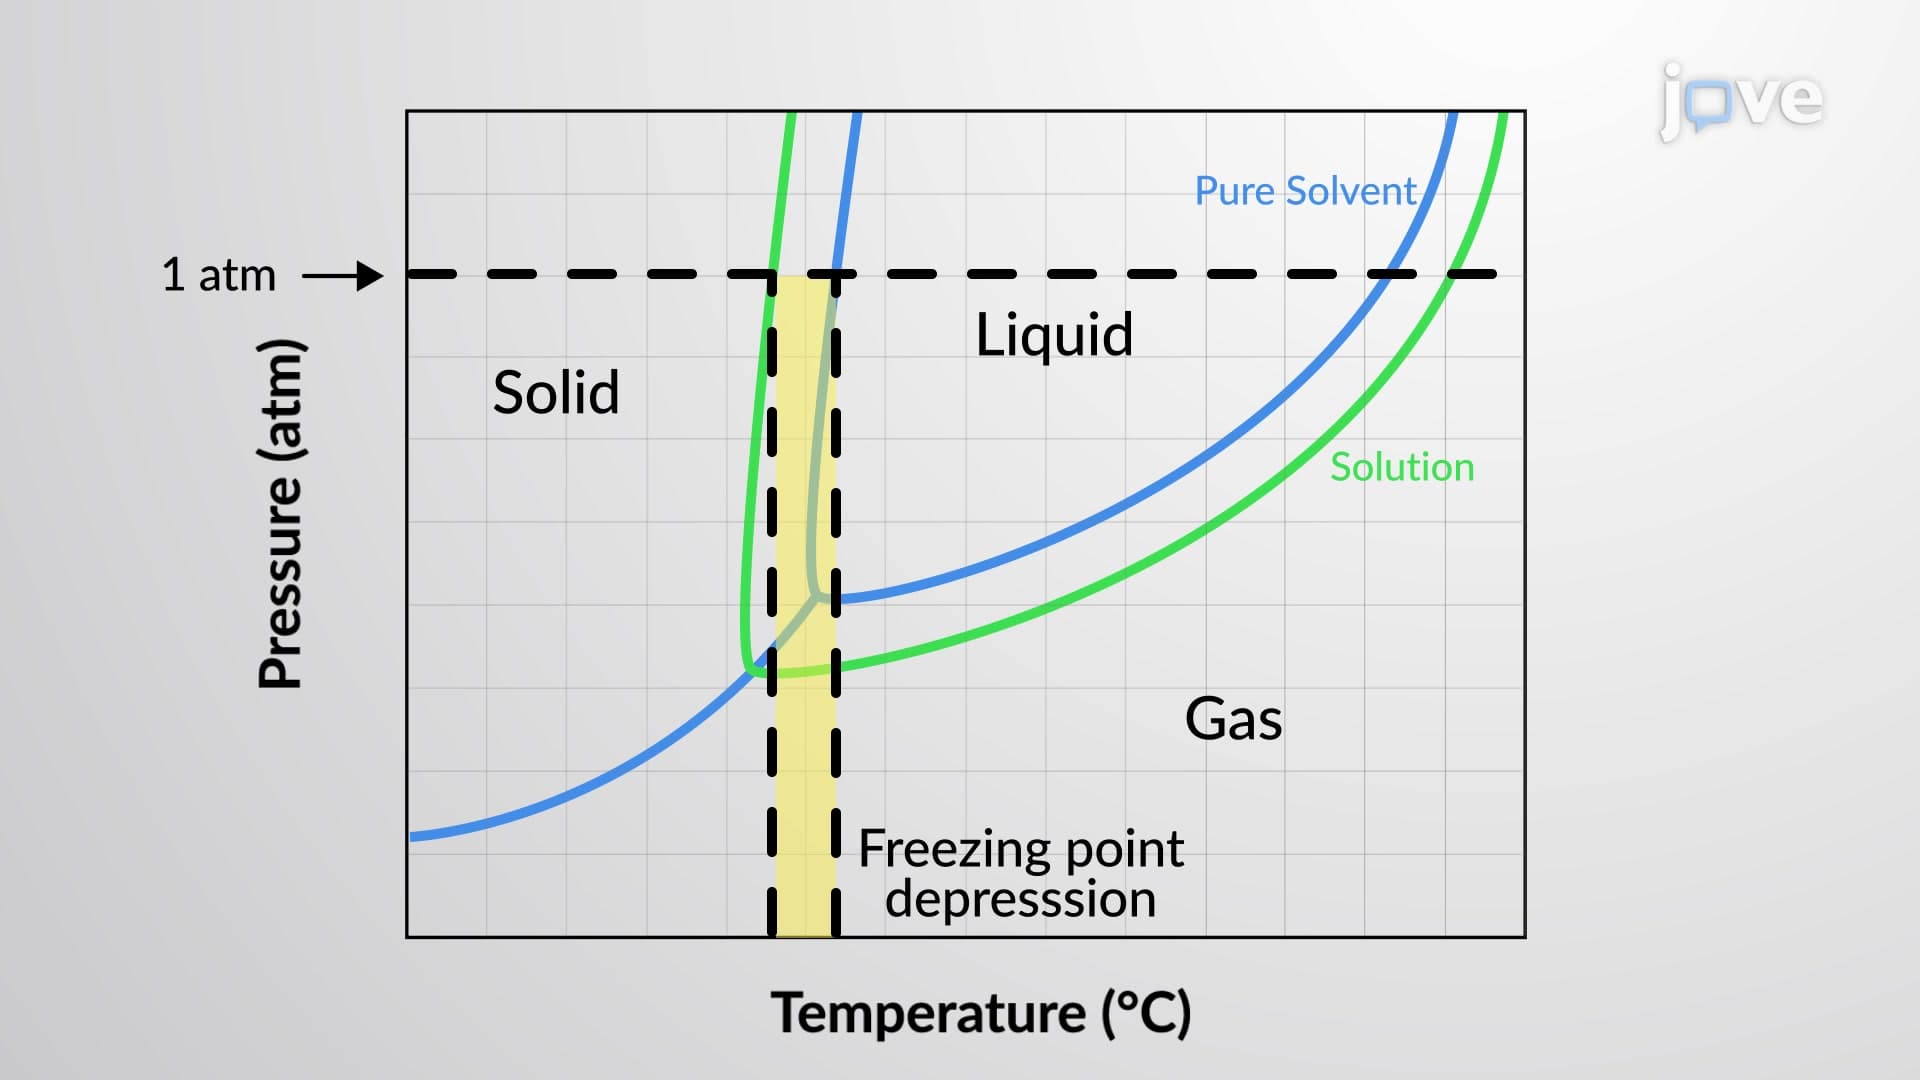
Freezing Point Depression and Boiling Point Elevation
The boiling point of a liquid is the temperature at which its vapor pressure is equal to ambient atmospheric pressure. Since the vapor pressure of a solution is lowered due to the presence of nonvolatile solutes, it stands to reason that the solution’s boiling point will subsequently be increased. Vapor pressure increases with temperature, and so a solution will require a higher temperature than will pure solvent to achieve any given vapor pressure, including one...
 01:03
Nursing Interventions I: Taxonomy of Nursing Interventions
A nursing intervention is a treatment or action based on scientific concepts and knowledge from the nursing, behavioral, and physical sciences. Identifying and prioritizing nursing interventions based on the desired outcome...
 01:29
Nursing Interventions II: Selecting and Classifying the Nursing Interventions
 01:20
Elevation of Intermediate Points on Vertical Curves
 01:21
Coronary Circulation
Coronary circulation begins at the base of the aorta, where two main arteries arise—the left and right coronary arteries. These arteries encircle the heart in the coronary sulcus and supply the...