Related Experiment Video
Updated: Feb 10, 2026


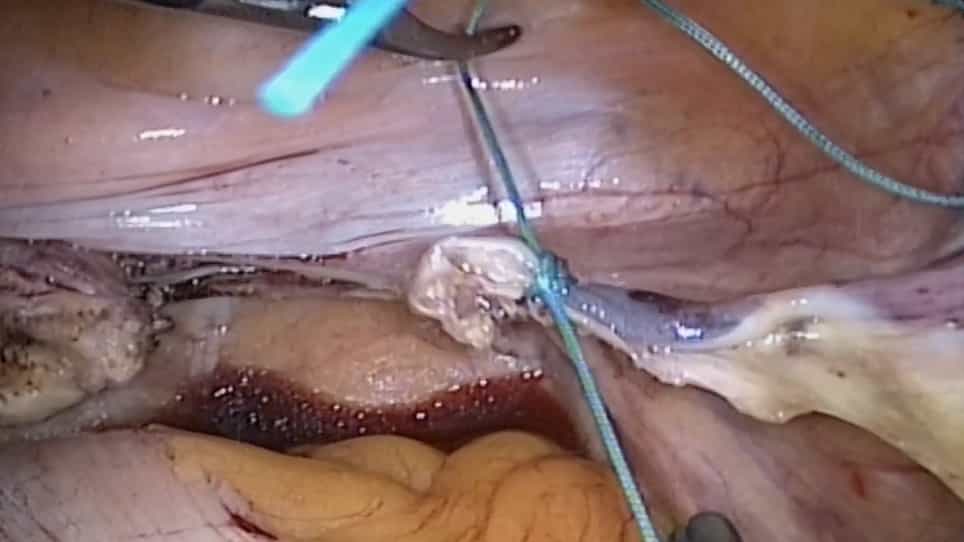
Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Laparoscopic Pelvic Exenteration for Locally Advanced Rectal Cancer, Technique and Short-Term Outcomes
Ashish Pokharkar1, Praveen Kammar1, Ashwin D'souza1
1Colorectal Services, Tata Memorial Hospital, Mumbai, India.

Abstract:
Since last two decades minimally invasive techniques have revolutionized surgical field. In 2003 Pomel first described laparoscopic pelvic exenteration, since then very few reports have described minimally invasive approaches for total pelvic exenteration. We report the 10 cases of locally advanced rectal adenocarcinoma which were operated between the periods from March 1, 2017 to November 11, 2017 at the Tata Memorial Hospital, Mumbai. All male patients had lower rectal cancer with prostate involvement on magnetic resonance imaging (MRI). One female patient had uterine and fornix involvement. All perioperative and intraoperative parameters were collected retrospectively from prospectively maintained electronic data. Nine male patients with diagnosis of nonmetastatic locally advanced lower rectal adenocarcinoma were selected. All patients were operated with minimally invasive approach. All patients underwent abdominoperineal resection with permanent sigmoid stoma. Ileal conduit was constructed with Bricker's procedure through small infraumbilical incision (4-5 cm). Lateral pelvic lymph node dissection was done only when postchemoradiotherapy MRI showed enlarged pelvic nodes. All 10 patients received neoadjuvant chemo radiotherapy, whereas 8 patients received additional neoadjuvant chemotherapy. Mean body mass index was 21.73 (range 19.5-26.3). Mean blood loss was 1000 mL (range 300-2000 mL). Mean duration of surgery was 9.13 hours (range 7-13 hours). One patient developed paralytic ileus, which was managed conservatively. One patient developed intestinal obstruction due to herniation of small intestine behind the left ureter and ileal conduit. The same patient developed acute pylonephritis, which was managed with antibiotics. Mean postoperative stay was 14.6 days (range 9-25 days). On postoperative histopathology, all margins were free of tumor in all cases. Minimally invasive approaches can be used safely for total pelvic exenteration in locally advanced lower rectal adenocarcinoma. All patients had fast recovery with less blood loss. In all patients R0 resection was achieved with adequate margins. Long-term oncological outcomes are still uncertain and will require further follow-up.

Related Concept Videos
 01:08
Sample Preparation for Analysis: Advanced Techniques
Acid digestion with strong acids is commonly used to dissolve inorganic materials that are insoluble (do not dissolve) in water. This method can be useful for...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:27
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 02:24
Predicting Reaction Outcomes
 01:26
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:13
Outcomes of Glycolysis
Cellular respiration can occur aerobically (with oxygen) or anaerobically (without oxygen). In the presence of oxygen, cellular respiration starts with glycolysis and continues with pyruvate...