Related Experiment Video
Updated: Feb 10, 2026

Studying Brain Function in Children Using Magnetoencephalography
Published on: April 8, 2019
Leveraging pediatric PROMIS item banks to assess physical functioning in children at risk for severe functional loss
Angie Mae Rodday1, Robert J Graham2, Ruth Ann Weidner3
11Institute for Clinical Research and Health Policy Studies, Tufts Medical Center, Department of Medicine, Tufts University School of Medicine, 800 Washington St, Box 345, Boston, MA 02111 USA.

Insights
Custom PROMIS short forms effectively measured low physical functioning in children with neuromuscular illnesses. These tools show promise for improving health-related quality of life assessments in this population.
Area of Science:
- Pediatric Health
- Rehabilitation Medicine
- Quality of Life Research
Background:
- Pediatric neuromuscular illnesses significantly impair health-related quality of life (HRQL), particularly physical functioning.
- Existing generic HRQL measures may not capture severe functional limitations in children.
- Custom parent-proxy short forms were developed using PROMIS item banks to address this measurement gap.
Purpose of the Study:
- To create and evaluate custom parent-proxy physical functioning short forms for children with neuromuscular illnesses.
- To assess the ability of these PROMIS-based measures to capture low levels of physical functioning.
- To explore the psychometric properties of the custom short forms.
Main Methods:
- Developed two custom 13-item parent-proxy short forms from PROMIS Upper Extremity and Mobility item banks.
- Administered forms to parents of children (5-22 years) with chronic respiratory insufficiency due to neuromuscular illnesses.
- Assessed psychometric properties, including known-groups comparisons with physician-rated clinical severity and CHRIs global health.
Main Results:
- Fifty-seven parents completed the custom PROMIS short forms.
- Mean Upper Extremity T-score was 21 (SD=13), and Mobility T-score was 22 (SD=11), indicating significantly low functioning.
- Known-groups comparisons confirmed better functioning in children with lower clinical severity and better self-reported health.
Conclusions:
- Custom PROMIS short form T-scores were substantially below the PROMIS pediatric mean, demonstrating sensitivity to low physical functioning.
- Preliminary psychometrics suggest potential for accurate measurement of severe functional loss in pediatric neuromuscular populations.
- Further refinement and larger-scale testing are needed to optimize these measures.
Background:
Pediatric neuromuscular illnesses often result in decreased health-related quality of life (HRQL), notably in physical functioning. Generic HRQL measures have been developed for use in general populations, but may not adequately assess patients with severe functional loss. To address this measurement gap, we created two custom parent-proxy physical functioning short forms for use among children at risk for low levels of functioning, using pediatric Patient Reported Outcomes Measurement Information System (PROMIS) item banks for Upper Extremity and Mobility.
Methods:
Two custom short forms from PROMIS Upper Extremity (13 items) and Mobility (13 items) parent-proxy item banks were created and administered to parents of children (ages 5 - 22 years) enrolled in an integrated care program for management of chronic respiratory insufficiency, largely due to neuromuscular illnesses. Standardized PROMIS T-scores have a mean of 50 (SD = 10); higher scores indicate better functioning. Physicians rated clinical severity. Single proxy-rated items on mental and physical health from the Child Health Rating Inventories (CHRIs) global health scale were completed by parents. Psychometric properties, including known groups comparisons, were explored.
Results:
Fifty-seven parents completed the parent-proxy custom PROMIS short forms. The mean Upper Extremity T-score was 21 (SD = 13); the mean Mobility T-score was 22 (SD = 11). Some participants scored at the measurement floor; two items on assistive devices did not perform well in this sample and were excluded from the Mobility T-score. Known groups comparisons showed that those with lower clinical severity had better median Upper Extremity (22 vs. 14, p < 0.001) and Mobility (28 vs. 16, p = 0.004) function than those with worse clinical severity. Both Upper Extremity and Mobility T-scores were higher in the subgroups defined by better physical and mental health, as measured by the CHRIs.
Conclusions:
Upper Extremity and Mobility T-scores were nearly three standard deviations below the PROMIS pediatric calibration population mean. Preliminary psychometrics demonstrated the potential to more accurately measure lower physical functioning using items from PROMIS item banks. However, some participants scored at the measurement floor despite targeting items at the lower end of the scale. Further short form refinement, enrichment of the item banks, and larger-scale field testing are needed.


Related Concept Videos
 01:12
Loss of Tumor Suppressor Gene Functions
When the tumor suppressor genes develop mutations or are lost, cells start growing out of control, leading to cancer. However, a single functional copy of the tumor suppressor gene is enough for the cells to maintain their normal functions and cell...
 02:45
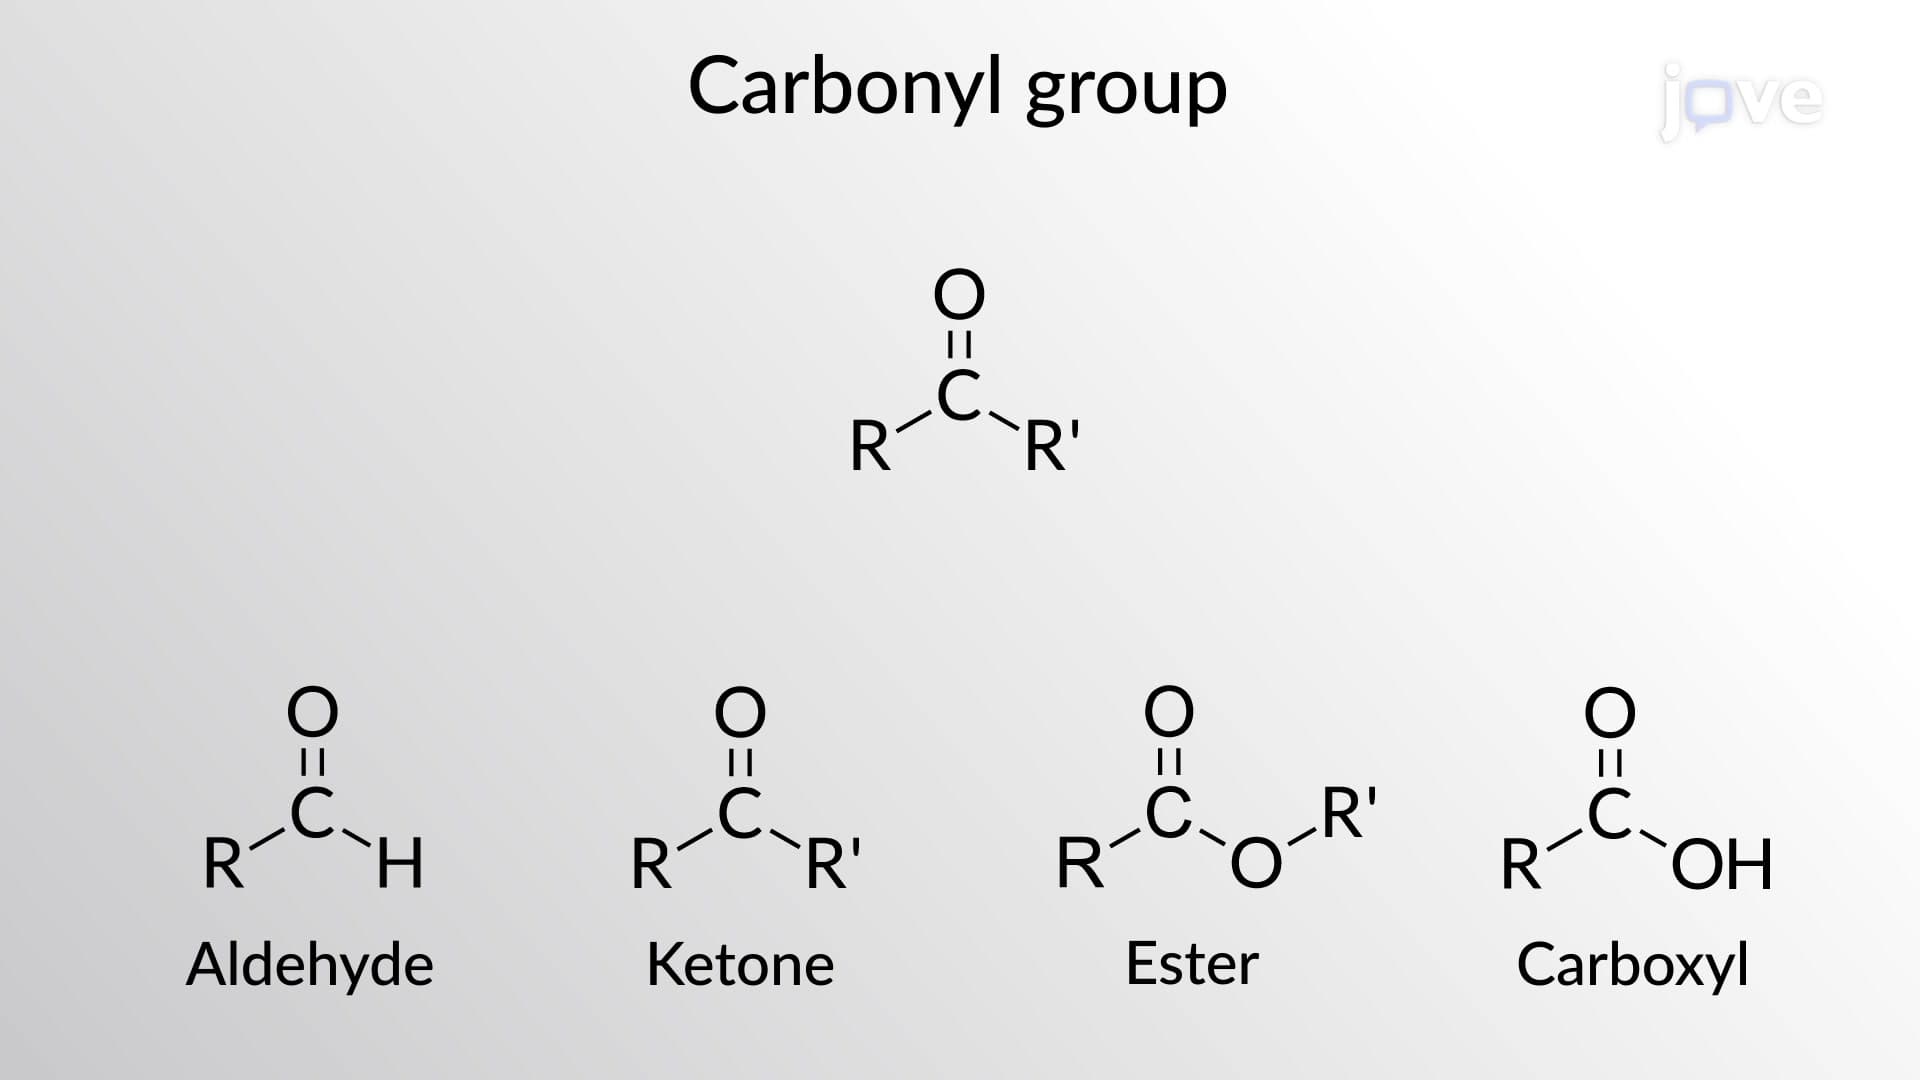
Functional Groups
02:45Functional Groups
 01:11
Functionalism
James envisioned psychology's...
 01:58
Mechanical Protein Functions
 01:56
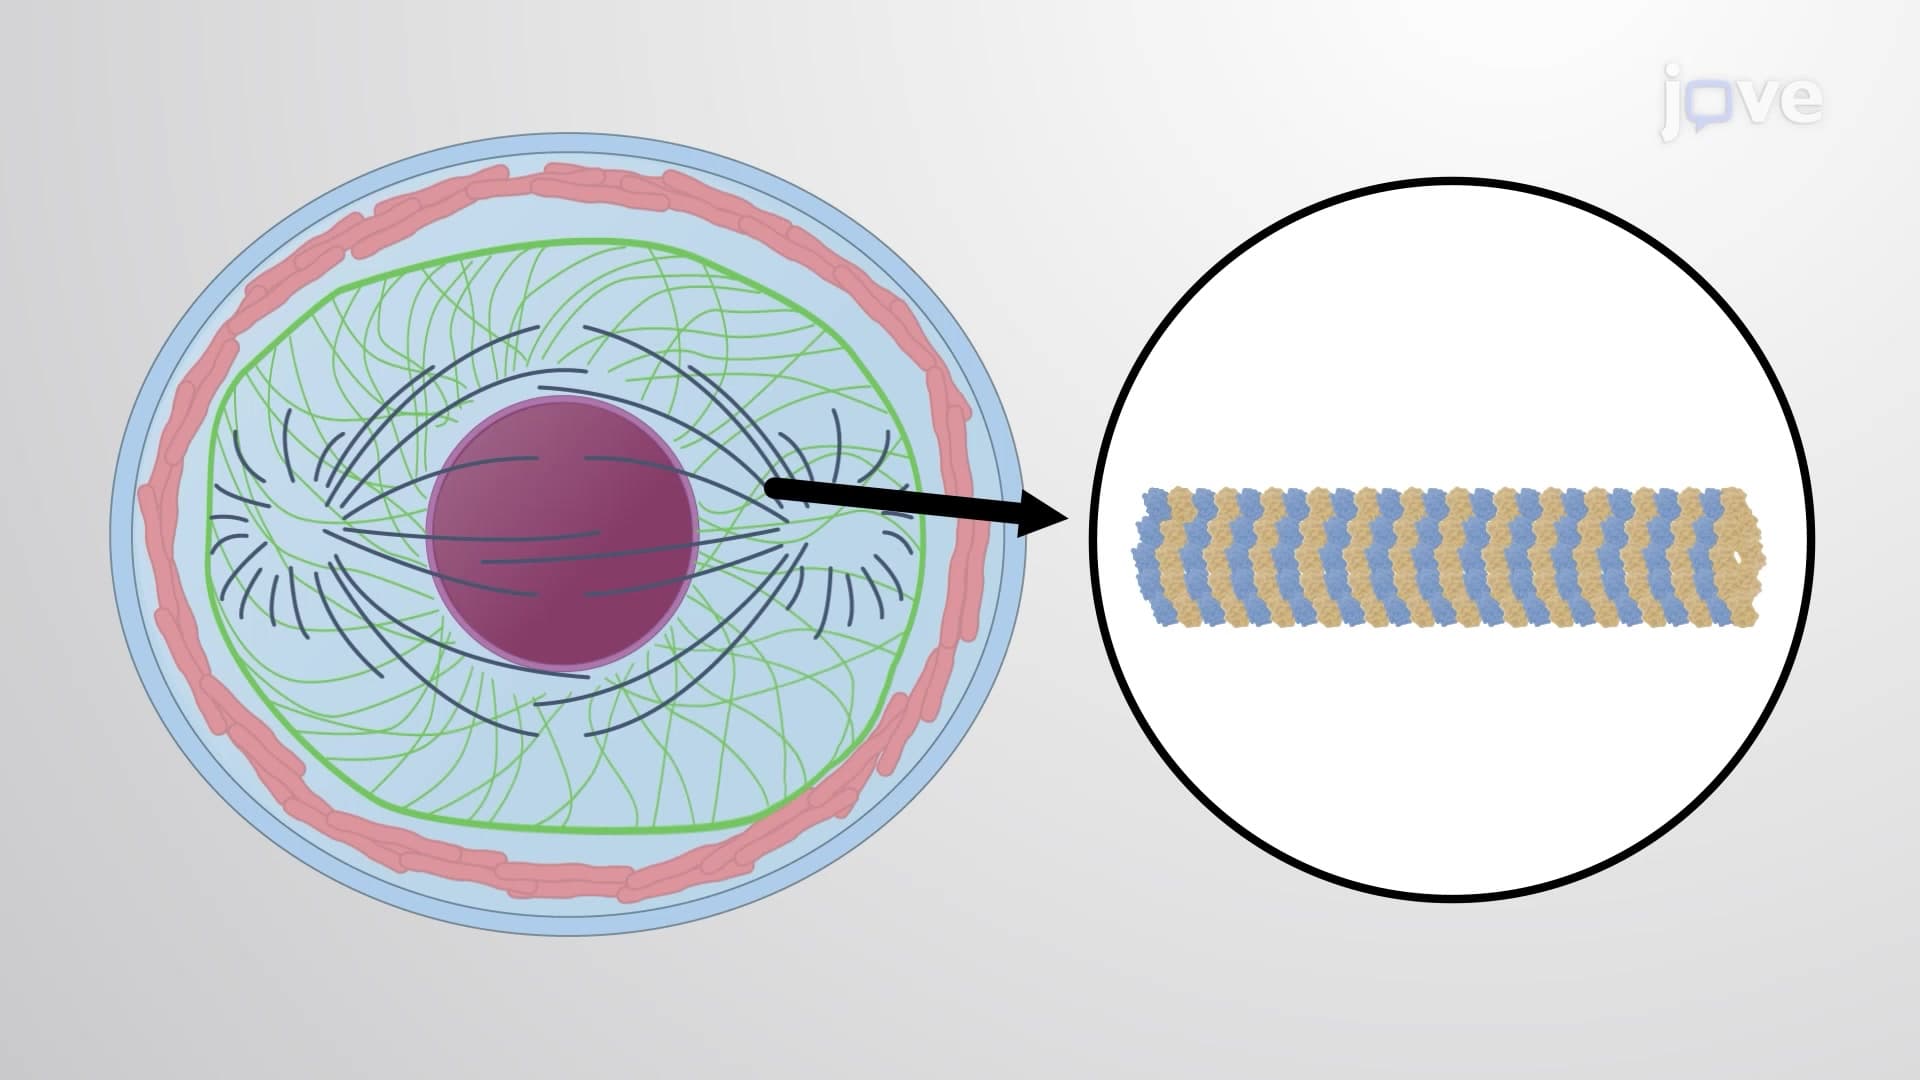
Structural Protein Function
Collagen, the most abundant protein in mammals, is found throughout the body. In connective tissue, such as skin, ligaments, and tendons, it provides tensile strength and elasticity. In bones and teeth, it mineralizes to...