Related Experiment Video
Updated: Feb 10, 2026

Advanced Cardiac Rhythm Management by Applying Optogenetic Multi-Site Photostimulation in Murine Hearts
Published on: August 26, 2021
Management of cardiac hemochromatosis
1Cardiology Division, Department of Medicine, Westchester Medical Center/New York Medical College, Valhalla, NY, USA.

Insights
Cardiac hemochromatosis, a cause of heart failure, involves iron overload in the heart. Early screening with serum ferritin and transferrin saturation, followed by MRI, guides treatment with phlebotomy or iron chelation therapy.
Area of Science:
- Cardiology
- Hematology
- Genetics
Background:
- Iron overload syndromes, hereditary or acquired, can lead to severe cardiac complications.
- Cardiac hemochromatosis presents as dilated cardiomyopathy, potentially causing rapid deterioration and heart failure.
- Iron deposition in the cardiac conduction system, particularly the atrioventricular node, can disrupt heart rhythm.
Purpose of the Study:
- To highlight the importance of considering cardiac hemochromatosis in unexplained heart failure.
- To outline diagnostic strategies for systemic iron overload and cardiac involvement.
- To detail therapeutic approaches for managing cardiac hemochromatosis.
Main Methods:
- Screening for systemic iron overload using serum ferritin and transferrin saturation.
- Utilizing cardiac magnetic resonance imaging (MRI) for quantitative assessment of myocardial iron load.
- Histologic confirmation of organ involvement in cases of suspected iron overload.
Main Results:
- Cardiac hemochromatosis is characterized by dilated cardiomyopathy with reduced ejection fraction and fractional shortening.
- Cardiac MRI is superior for quantifying myocardial iron load compared to other diagnostic tests.
- Therapeutic phlebotomy is effective for non-anemic patients with specific serum ferritin thresholds.
Conclusions:
- Cardiac hemochromatosis should be suspected in patients with unexplained heart failure.
- Early diagnosis through screening and advanced imaging like MRI is crucial.
- Phlebotomy is the primary treatment for non-anemic patients, while iron chelation is indicated for anemic or severely compromised patients.
Abstract:
Iron-overload syndromes may be hereditary or acquired. Patients may be asymptomatic early in the disease. Once heart failure develops, there is rapid deterioration. Cardiac hemochromatosis is characterized by a dilated cardiomyopathy with dilated ventricles, reduced ejection fraction, and reduced fractional shortening. Deposition of iron may occur in the entire cardiac conduction system, especially the atrioventricular node. Cardiac hemochromatosis should be considered in any patient with unexplained heart failure. Screening for systemic iron overload with serum ferritin and transferin saturation should be performed. If these tests are consistent with iron overload, further noninvasive and histologic confirmation is indicated to confirm organ involvement with iron overload. Cardiac magnetic resonance imaging is superior to other diagnostic tests since it can quantitatively assess myocardial iron load. Therapeutic phlebotomy is the therapy of choice in nonanemic patients with cardiac hemochromatosis. Therapeutic phlebotomy should be started in men with serum ferritin levels of 300 μg/l or more and in women with serum ferritin levels of 200 μg/l or more. Therapeutic phlebotomy consists of removing 1 unit of blood (450 to 500 ml) weekly until the serum ferritin level is 10 to 20 μg/l and maintenance of the serum ferritin level at 50 μg/l or lower thereafter by periodic removal of blood. Phlebotomy is not a treatment option in patients with anemia (secondary iron-overload disorders) nor in patients with severe congestive heart failure. In these patients, the treatment of choice is iron chelation therapy.
More Related Videos
 05:04
In vitro Assessment of Cardiac Reprogramming by Measuring Cardiac Specific Calcium Flux with a GCaMP3 Reporter
Published on: February 22, 2022
 06:29
Cardiac Magnetic Resonance for the Evaluation of Suspected Cardiac Thrombus: Conventional and Emerging Techniques
Published on: June 11, 2019
Related Concept Videos
 01:26
Cardiac Catheterization IV: Nursing Management
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:26
Tonsillitis II: Management
 01:29
Impression Management Techniques I: Managing Appearances
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
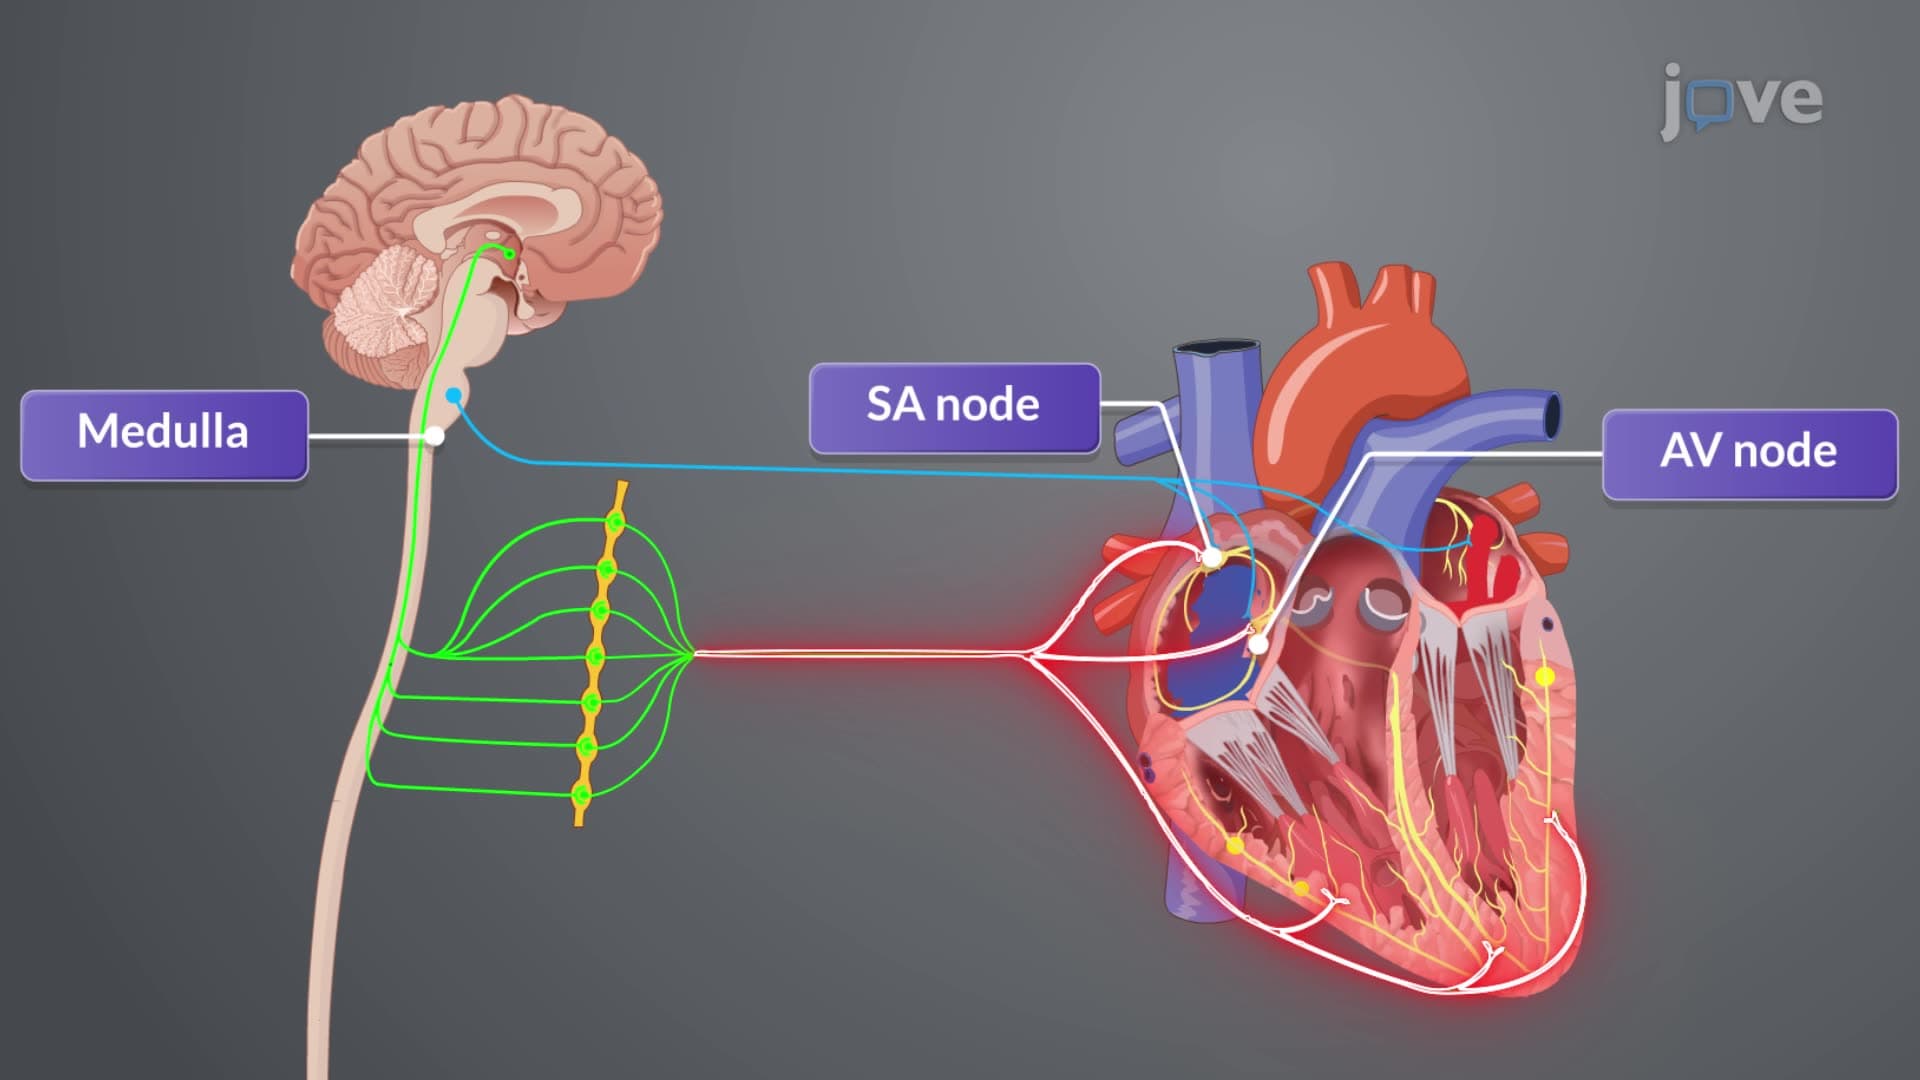
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:13
The Cardiac Cycle
The Process
Electrical signals—sent from the sinoatrial (SA) node in the right atrial wall to the atrioventricular (AV) node between the right atrium and right ventricle—cause both atria to simultaneously contract. When the signal reaches the AV node, it pauses for approximately a tenth of a second, allowing the atria to contract and...