Related Experiment Video
Updated: Feb 10, 2026


Development of Human Renal Tubular Epithelial Cell Primary Cultures in Monolayers and Three-Dimensional Conditions
Published on: June 13, 2025
Optimal dosage and early intervention of L-ascorbic acid inhibiting K2Cr2O7-induced renal tubular cell damage
Tzeng-Jih Lin1, Yeou-Lih Huang2, Jung-San Chang3
1Emergency Department, Kaohsiung Medical University Hospital, Kaohsiung Medical University, Kaohsiung, Taiwan; Family Medicine Department, Taoyuan Branch, Taipei Veterans General Hospital, Taipei, Taiwan.

Abstract:
Chromium poisoning can cause renal failure and death. Chromium intoxication may be managed using L-ascorbic acid (vitamin C) therapy. However, the evidence supporting the effectiveness of this treatment is insufficient, and the mechanism of action has not been clarified in renal cells. In this study, our results showed that the optimal regimen of L-ascorbic acid therapy in human epithelial renal proximal tubule cells, HK-2 cells, was 30 μg/mL. Supplementation of L-ascorbic acid with 30 μg/mL and within 8 h of chromium intoxication (K2Cr2O7, Cr6+) was effective to inhibit renal tubular cell damage by blocking generation of free radicals, cell apoptosis, and autophagy. Intracellular chromium concentrations were estimated using electrothermal atomic absorption spectrometry. Treatment of L-ascorbic acid within 8 h of chromium intoxication significantly decreased the entry of chromium into the cells. Moreover, concomitant administration of L-ascorbic acid with repeatedly dosing at 8-hourly intervals had a better protective effect at lower concentration of L-ascorbic acid when compared to single dosing of L-ascorbic acid at an early time point of chromium intoxication. These findings might help physicians develop effective therapy strategies in renal failure.


Related Concept Videos
 01:25
Renal Drug Excretion: Tubular Reabsorption
 01:28
Renal Drug Excretion: Tubular Secretion
 01:15
Drug Elimination by Renal Route: Tubular Secretion
 01:22
Drug Elimination by Renal Route: Tubular Reabsorption
 03:38
Polyprotic Acids
 01:29
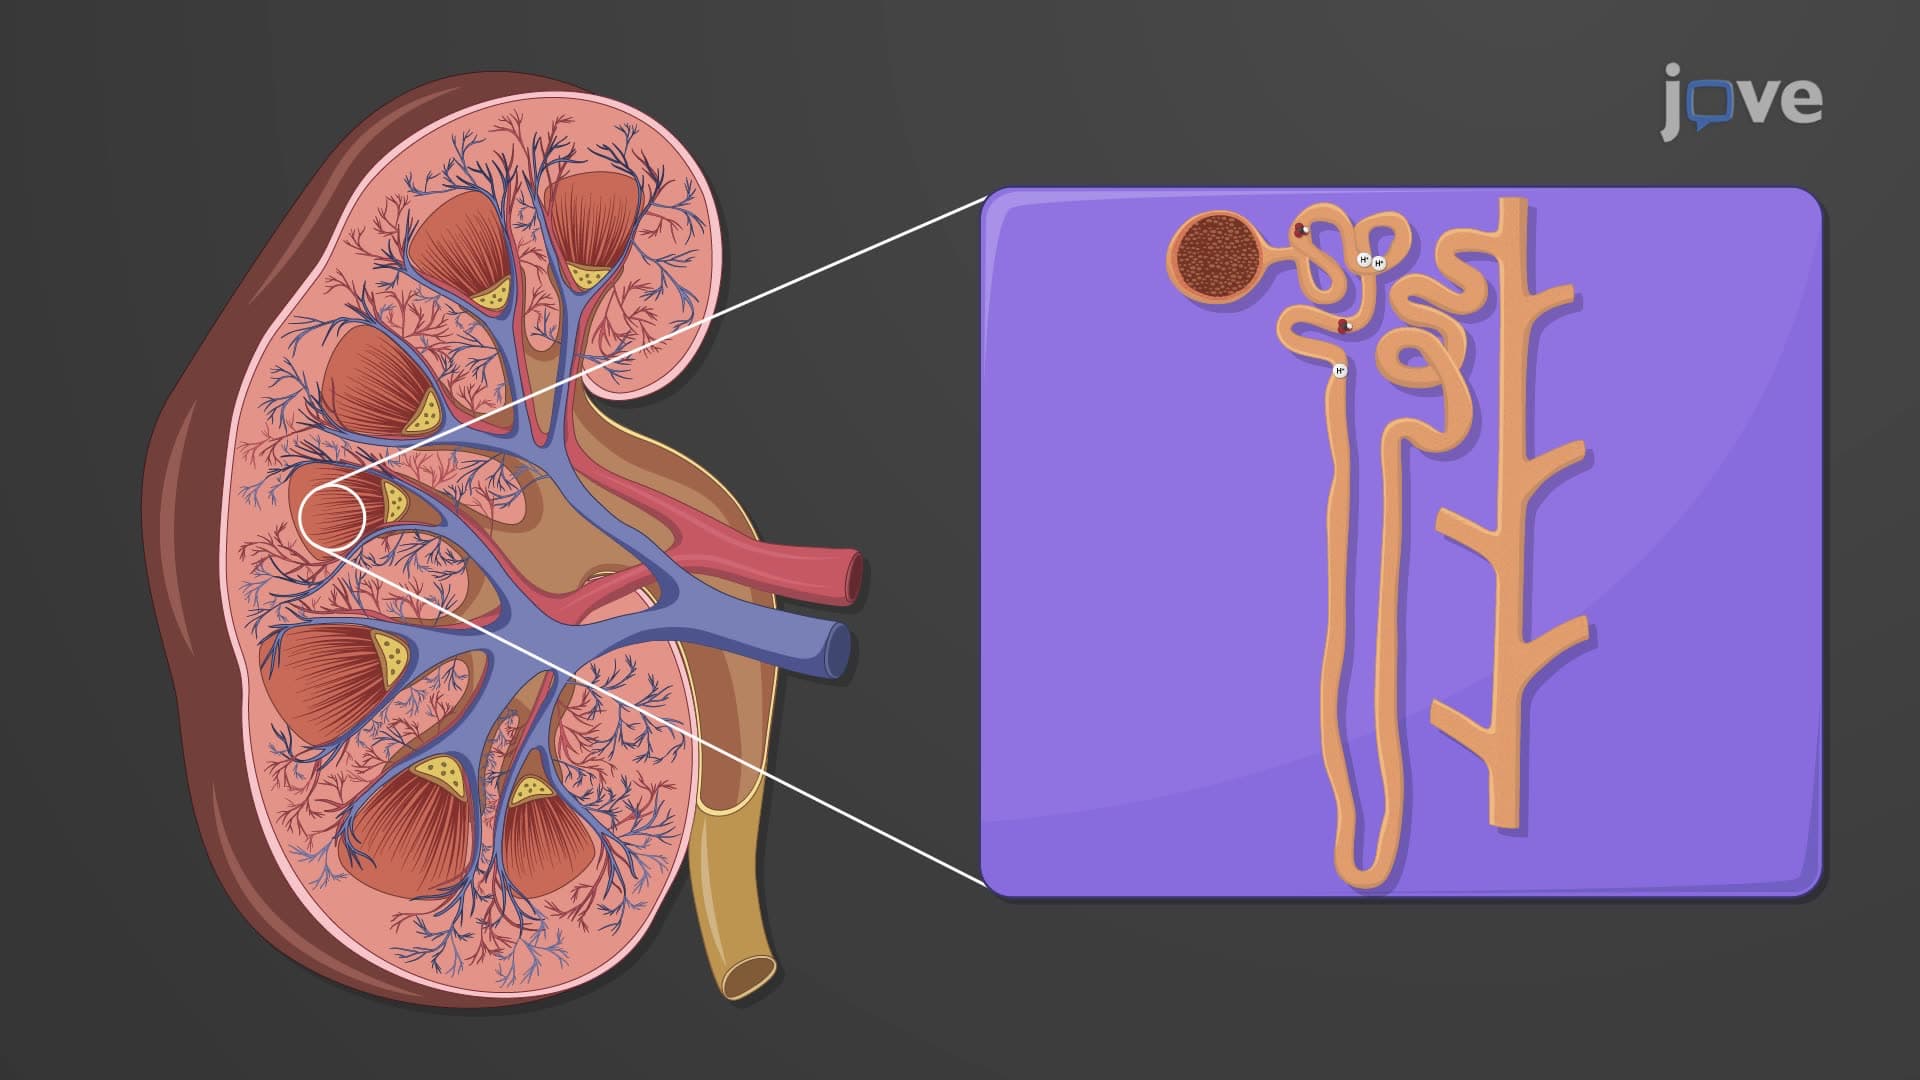
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...