Related Experiment Video
Updated: Feb 10, 2026

Author Spotlight: Utilizing Venoplasty Balloon Model in Rodents to Simulate Surgical Interventions for Deep Veins
Published on: May 24, 2024
Does Respiratory Variation in Inferior Vena Cava Diameter Predict Fluid Responsiveness in Mechanically Ventilated
Xiang Si1, Hailin Xu1, Zimeng Liu1
1From the Department of Surgical Intensive Care Unit, The First Affiliated Hospital.

Background:
We performed a systematic review and meta-analysis of studies investigating the diagnostic accuracy of respiratory variation in inferior vena cava diameter (ΔIVC) for predicting fluid responsiveness in patients receiving mechanical ventilation.
Methods:
MEDLINE, EMBASE, the Cochrane Library, and Web of Science were screened from inception to February 2017. The meta-analysis assessed the pooled sensitivity, specificity, diagnostic odds ratio, and area under the receiver operating characteristic curve. In addition, heterogeneity and subgroup analyses were performed.
Results:
A total of 12 studies involving 753 patients were included. Significant heterogeneity existed among the studies, and meta-regression indicated that ventilator settings were the main sources of heterogeneity. Subgroup analysis indicated that ΔIVC exhibited better diagnostic performance in the group of patients ventilated with tidal volume (TV) ≥8 mL/kg and positive end-expiratory pressure (PEEP) ≤5 cm H2O than in the group ventilated with TV <8 mL/kg or PEEP >5 cm H2O, as demonstrated by higher sensitivity (0.80 vs 0.66; P = .02), specificity (0.94 vs 0.68; P < .001), diagnostic odds ratio (68 vs 4; P < .001), and area under the receiver operating characteristic curve (0.88 vs 0.70; P < .001). The best ΔIVC threshold for predicting fluid responsiveness was 16% ± 2% in the group of TV ≥8 mL/kg and PEEP ≤5 cm H2O, whereas in the group of TV <8 mL/kg or PEEP >5 cm H2O, this threshold was 14% ± 5%.
Conclusions:
ΔIVC shows limited ability for predicting fluid responsiveness in distinct ventilator settings. In patients with TV ≥8 mL/kg and PEEP ≤5 cm H2O, ΔIVC was an accurate predictor of fluid responsiveness, while in patients with TV <8 mL/kg or PEEP >5 cm H2O, ΔIVC was a poor predictor. Thus, intensivists must be cautious when using ΔIVC.
Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:11
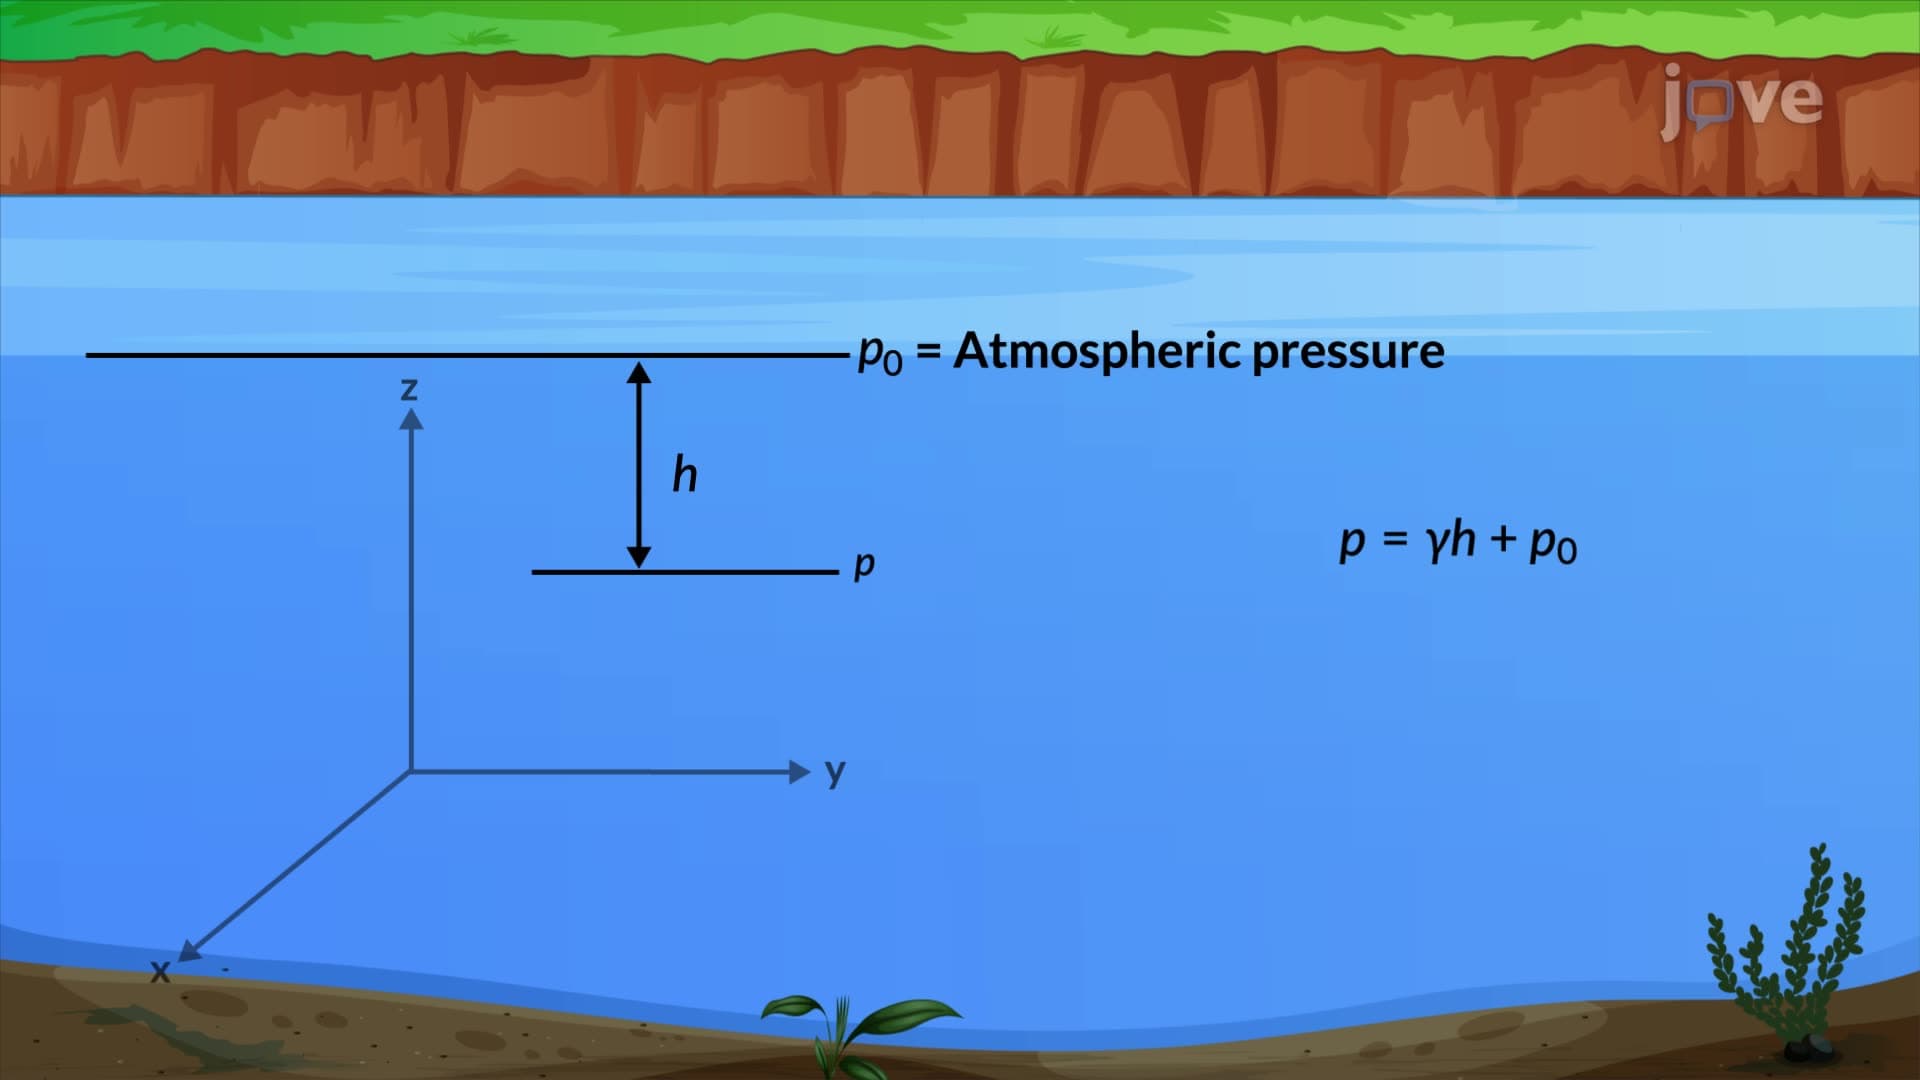
Pressure Variation in a Fluid at Rest
When measuring pressure at two different levels within the fluid, the difference in...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:29
Mechanical Ventilation I: Indication and Settings