Ranking hospitals: do we gain reliability by using composite rather than individual indicators?
Related Experiment Video
Updated: Feb 10, 2026
A Reliable Porcine Fascio-Cutaneous Flap Model for Vascularized Composite Allografts Bioengineering Studies
Published on: March 31, 2022
Stefanie N Hofstede1, Iris E Ceyisakar2, Hester F Lingsma2
1Department of Biomedical Data Sciences, Medical Decision Making, Leiden University Medical Centre, Leiden, The Netherlands.

Background:
Despite widespread use of quality indicators, it remains unclear to what extent they can reliably distinguish hospitals on true differences in performance. Rankability measures what part of variation in performance reflects 'true' hospital differences in outcomes versus random noise.
Objective:
This study sought to assess whether combining data into composites or including data from multiple years improves the reliability of ranking quality indicators for hospital care.
Methods:
Using the Dutch National Medical Registration (2007-2012) for stroke, colorectal carcinoma, heart failure, acute myocardial infarction and total hiparthroplasty (THA)/ total knee arthroplasty (TKA) in osteoarthritis (OA), we calculated the rankability for in-hospital mortality, 30-day acute readmission and prolonged length of stay (LOS) for single years and 3-year periods and for a dichotomous and ordinal composite measure in which mortality, readmission and prolonged LOS were combined. Rankability, defined as (between-hospital variation/between-hospital+within hospital variation)×100% is classified as low (<50%), moderate (50%-75%) and high (>75%).
Results:
Admissions from 555 053 patients treated in 95 hospitals were included. The rankability for mortality was generally low or moderate, varying from less than 1% for patients with OA undergoing THA/TKA in 2011 to 71% for stroke in 2010. Rankability for acute readmission was low, except for acute myocardial infarction in 2009 (51%) and 2012 (62%). Rankability for prolonged LOS was at least moderate. Combining multiple years improved rankability but still remained low in eight cases for both mortality and acute readmission. Combining the individual indicators into the dichotomous composite, all diagnoses had at least moderate rankability (range: 51%-96%). For the ordinal composite, only heart failure had low rankability (46% in 2008) (range: 46%-95%).
Conclusion:
Combining multiple years or into multiple indicators results in more reliable ranking of hospitals, particularly compared with mortality and acute readmission in single years, thereby improving the ability to detect true hospital differences. The composite measures provide more information and more reliable rankings than combining multiple years of individual indicators.

Related Concept Videos
 00:59
Hospitals-II
Nurses that work in...
 02:39
Indicators
 01:28
Hospitals-I
 01:02
Ranks
 01:29
Reliability and Validity
 01:15
Gain
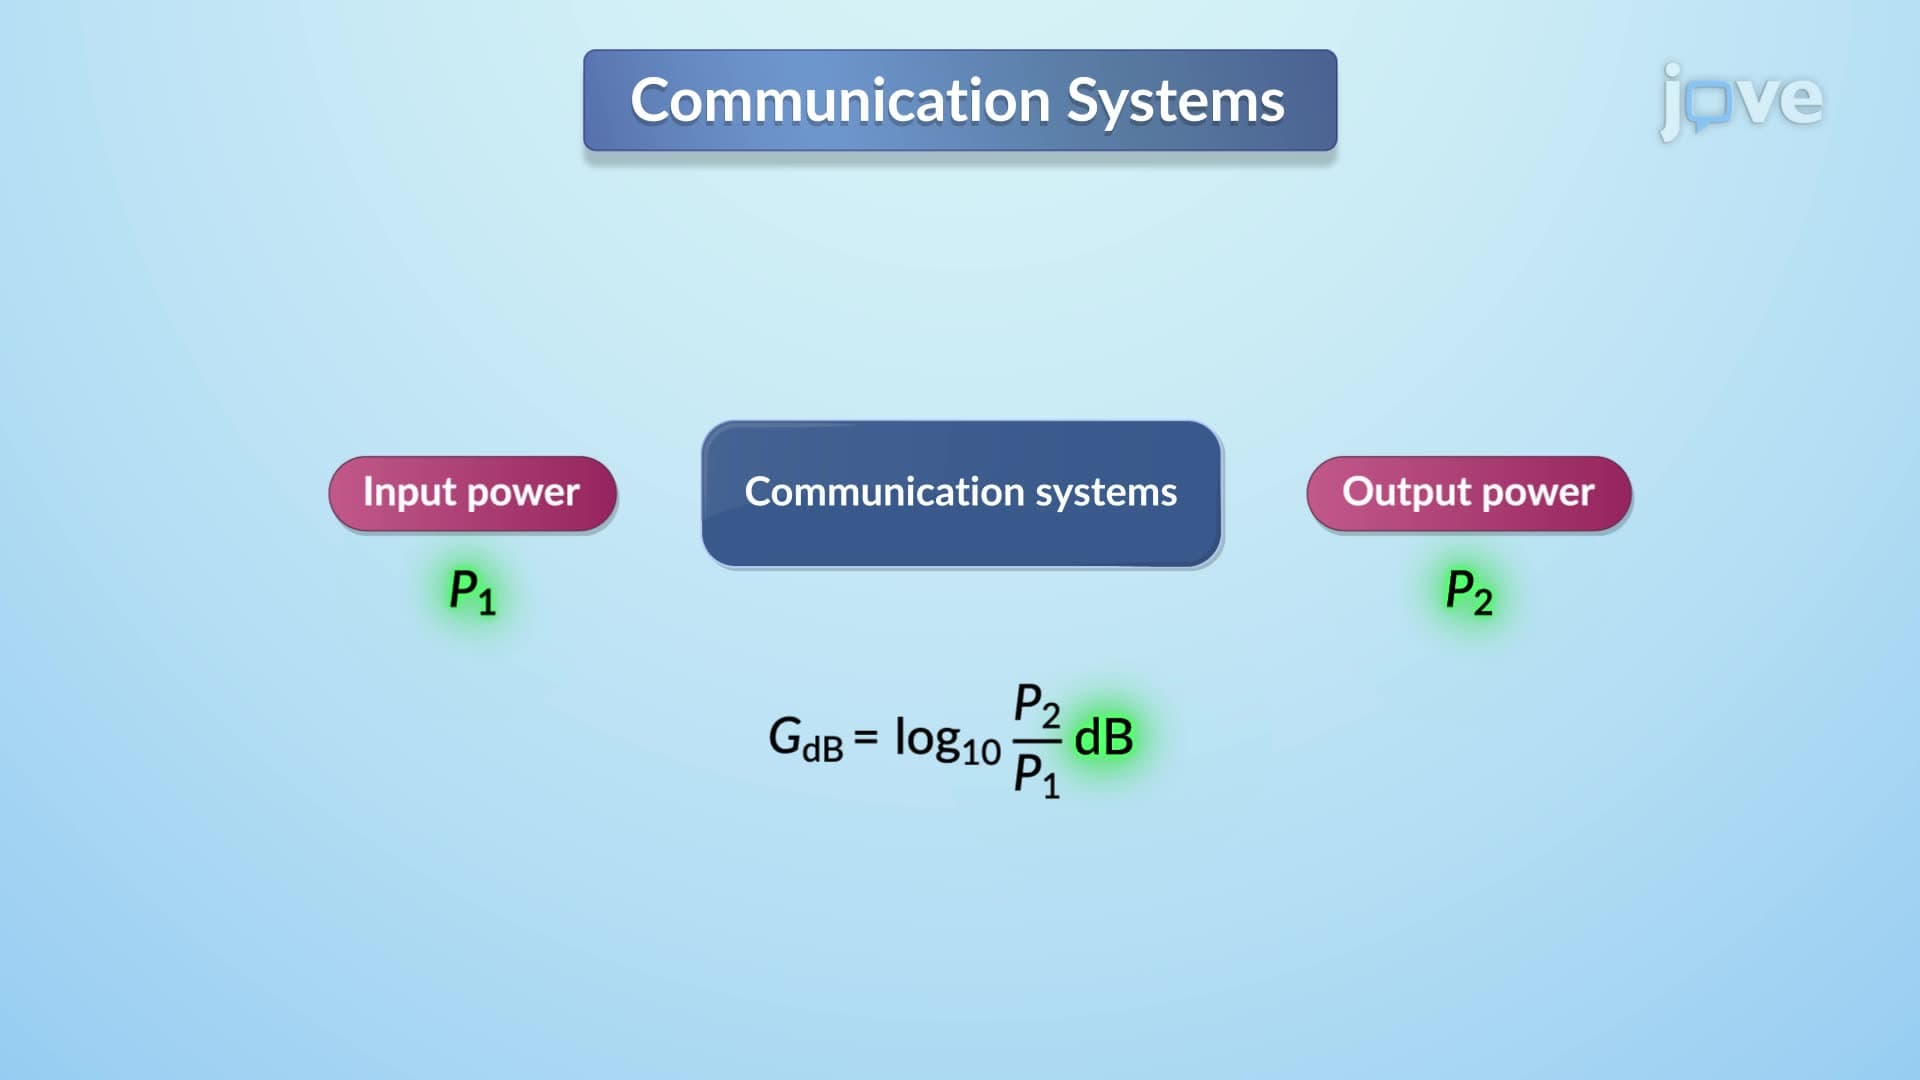
Gain:
Suppose Vin is the input and Vout is the output signal to a circuit.