Related Experiment Video
Updated: Feb 10, 2026
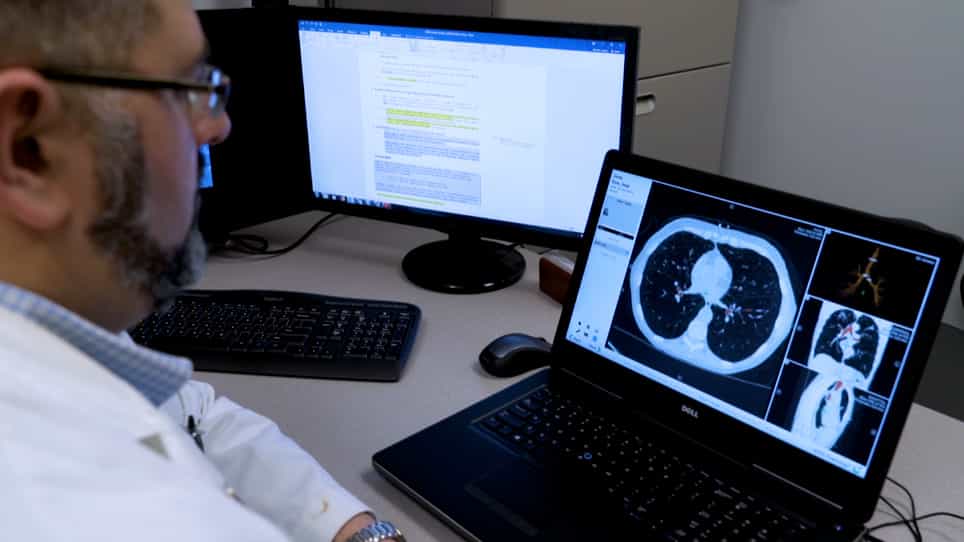

Electromagnetic Navigation Transthoracic Nodule Localization for Minimally Invasive Thoracic Surgery
Published on: May 4, 2022
Minimally Invasive Lung Cancer Surgery Performed by Thoracic Surgeons as Effective as Thoracotomy
Daniel J Boffa1, Andrzej S Kosinski1, Anthony P Furnary1
1Daniel J. Boffa and Jessica R. Hoag, Yale School of Medicine, New Haven, CT; Andrzej S. Kosinski, Sunghee Kim, and Patricia A. Cowper, Duke Clinical Research Institute; Betty C. Tong, Duke University School of Medicine, Durham, NC; Anthony P. Furnary, Starr-Wood Cardiac Group, Portland, OR; Mark W. Onaitis, University of California, San Diego School of Medicine, San Diego, CA; Jeffrey P. Jacobs, Johns Hopkins All Children's Heart Institute; Saint Petersburg; Joe B. Putnam Jr, Baptist MD Anderson Cancer Center, Jacksonville, FL; Cameron D. Wright, Massachusetts General Hospital, Boston, MA; and Felix G. Fernandez, Emory University, Atlanta, GA.

Purpose The prevalence of minimally invasive lung cancer surgery using video-assisted thoracic surgery (VATS) has increased dramatically over the past decade, yet recent studies have suggested that the lymph node evaluation during VATS lobectomy is inadequate. We hypothesized that the minimally invasive approach to lobectomy for stage I lung cancer resulted in a longitudinal outcome that was not inferior to thoracotomy. Patients and Methods Patients > 65 years of age who had undergone lobectomy for stage I lung cancer between 2002 and 2013 were analyzed within the Society of Thoracic Surgeons General Thoracic Surgery Database, which had been linked to Medicare data, as part of a retrospective-cohort, noninferiority study. Results A total of 10,597 patients with clinical stage I lung cancer who underwent lobectomy were evaluated (4,448 patients underwent thoracotomy, and 6,149 underwent VATS). VATS patients had a more favorable distribution of all health-related variables, including pulmonary function (59% of VATS patients had intact spirometry v 51% of thoracotomy patients; P < .001). Cox proportional hazards models were performed over two eras to account for an evolving practice standard. The mortality risk associated with the VATS approach was not greater than thoracotomy in either the earlier era (2002 to 2008; hazard ratio, 0.97; 95% CI, 0.87 to 1.09; P = .62) or the more recent era (2009 to 2013; hazard ratio, 0.84; 95% CI, 0.75 to 0.93; P < .001). Kaplan-Meier survival estimates of 2,901 propensity-matched VATS-thoracotomy pairs demonstrated that the 4-year survival associated with VATS (68.6%) was modestly superior to thoracotomy (64.8%; P = .003). The analyses detailed above were replicated in a separate cohort of pathologic stage I patients with similar findings. Conclusion The long-term efficacy of lobectomy for stage I lung cancer performed using the VATS approach by board-certified thoracic surgeons does not seem to be inferior to that of thoracotomy.
Purpose The prevalence of minimally invasive lung cancer surgery using video-assisted thoracic surgery (VATS) has increased dramatically over the past decade, yet recent studies have suggested that the lymph node evaluation during VATS lobectomy is inadequate. We hypothesized that the minimally invasive approach to lobectomy for stage I lung cancer resulted in a longitudinal outcome that was not inferior to thoracotomy. Patients and Methods Patients > 65 years of age who had undergone lobectomy for stage I lung cancer between 2002 and 2013 were analyzed within the Society of Thoracic Surgeons General Thoracic Surgery Database, which had been linked to Medicare data, as part of a retrospective-cohort, noninferiority study. Results A total of 10,597 patients with clinical stage I lung cancer who underwent lobectomy were evaluated (4,448 patients underwent thoracotomy, and 6,149 underwent VATS). VATS patients had a more favorable distribution of all health-related variables, including pulmonary function (59% of VATS patients had intact spirometry v 51% of thoracotomy patients; P < .001). Cox proportional hazards models were performed over two eras to account for an evolving practice standard. The mortality risk associated with the VATS approach was not greater than thoracotomy in either the earlier era (2002 to 2008; hazard ratio, 0.97; 95% CI, 0.87 to 1.09; P = .62) or the more recent era (2009 to 2013; hazard ratio, 0.84; 95% CI, 0.75 to 0.93; P < .001). Kaplan-Meier survival estimates of 2,901 propensity-matched VATS-thoracotomy pairs demonstrated that the 4-year survival associated with VATS (68.6%) was modestly superior to thoracotomy (64.8%; P = .003). The analyses detailed above were replicated in a separate cohort of pathologic stage I patients with similar findings. Conclusion The long-term efficacy of lobectomy for stage I lung cancer performed using the VATS approach by board-certified thoracic surgeons does not seem to be inferior to that of thoracotomy.


Related Concept Videos
 01:15
Thoracic Aorta
 01:17
The Thoracic Cage: Sternum
The sternum is the elongated bony structure on the anterior side of the thoracic cage. It consists of three parts: the manubrium, the body, and the xiphoid...
 01:20
The Thoracic Cage: Ribs
Parts of a Typical Rib
A typical rib has a head, neck, and body. The posterior end of the rib is called the head, followed by a narrow neck. The head articulates primarily with the costal...
 01:47
Lung Capacity
 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...
 02:19
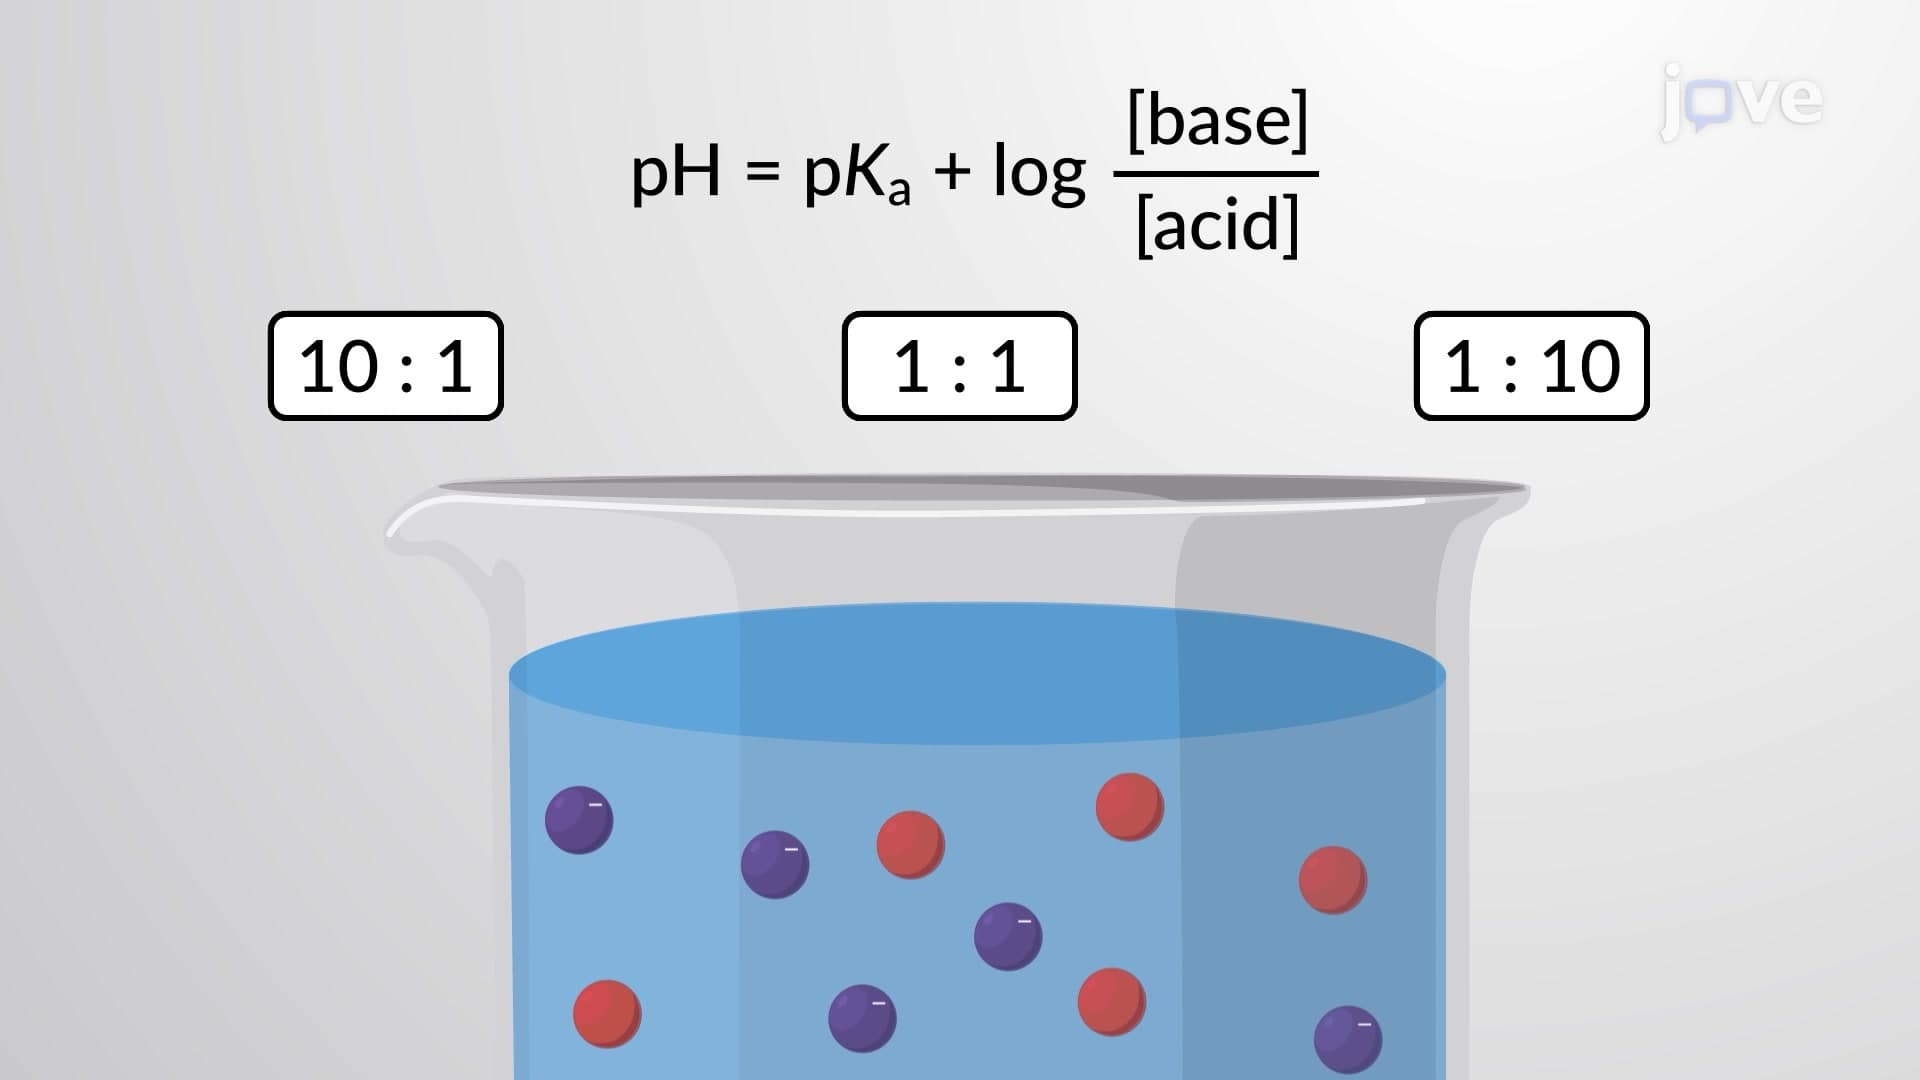
Buffer Effectiveness
The buffer capacity is the amount of acid or base that can be added to a given volume...