Related Experiment Video
Updated: Feb 10, 2026

Author Spotlight: Evaluating the Adjuvant Efficacy and Safety of Angong Niuhuang Pill in Viral Encephalitis Treatment
Published on: April 19, 2024
Effect of postoperative goal-directed therapy in cancer patients undergoing high-risk surgery: a randomized clinical
Aline Rejane Muller Gerent1, Juliano Pinheiro Almeida1, Evgeny Fominskiy2
1Intensive Care Unit and Department of Anesthesiology, Instituto do Cancer, Hospital das Clinicas da Faculdade de Medicina da Universidade de Sao Paulo, Sao Paulo, Brazil.

Insights
Goal-directed hemodynamic therapy (GDHT) did not reduce mortality or complications in high-risk cancer surgery patients. This postoperative intervention showed no significant benefit compared to usual care in reducing 30-day mortality or severe complications.
Area of Science:
- Critical Care Medicine
- Surgical Oncology
- Hemodynamics
Background:
- Perioperative goal-directed hemodynamic therapy (GDHT) is recommended for high-risk surgical patients to minimize complications.
- The study investigated the efficacy of cardiac index (CI)-guided GDHT postoperatively in cancer patients undergoing high-risk surgery.
Purpose of the Study:
- To determine if postoperative CI-guided GDHT reduces 30-day mortality and severe complications in high-risk cancer surgery patients.
- To evaluate the impact of GDHT on postoperative outcomes compared to usual care.
Main Methods:
- A randomized, parallel-group superiority trial involving adult patients undergoing high-risk cancer surgery.
- Patients were allocated to either CI-guided GDHT (target CI ≥ 2.5 L/min/m² for 8 hours postoperatively) or usual care.
- A meta-analysis of existing randomized trials on postoperative GDHT was also performed.
Main Results:
- The primary outcome (30-day mortality or severe complications) did not differ significantly between the GDHT group (53.1%) and the usual care group (43.8%).
- The meta-analysis of nine trials showed no significant difference in postoperative mortality or overall complication rates.
- However, the meta-analysis indicated a reduced hospital length of stay in the GDHT group.
Conclusions:
- Postoperative CI-guided hemodynamic therapy does not decrease 30-day mortality or severe complications in cancer patients undergoing high-risk surgery.
- While GDHT did not improve mortality or complication rates, it may be associated with shorter hospital stays.
Background:
Perioperative goal-directed hemodynamic therapy (GDHT) has been advocated in high-risk patients undergoing noncardiac surgery to reduce postoperative morbidity and mortality. We hypothesized that using cardiac index (CI)-guided GDHT in the postoperative period for patients undergoing high-risk surgery for cancer treatment would reduce 30-day mortality and postoperative complications.
Methods:
A randomized, parallel-group, superiority trial was performed in a tertiary oncology hospital. All adult patients undergoing high-risk cancer surgery who required intensive care unit admission were randomly allocated to a CI-guided GDHT group or to a usual care group. In the GDHT group, postoperative therapy aimed at CI ≥ 2.5 L/min/m2 using fluids, inotropes and red blood cells during the first 8 postoperative hours. The primary outcome was a composite endpoint of 30-day all-cause mortality and severe postoperative complications during the hospital stay. A meta-analysis was also conducted including all randomized trials of postoperative GDHT published from 1966 to May 2017.
Results:
A total of 128 patients (64 in each group) were randomized. The primary outcome occurred in 34 patients of the GDHT group and in 28 patients of the usual care group (53.1% vs 43.8%, absolute difference 9.4 (95% CI, - 7.8 to 25.8); p = 0.3). During the 8-h intervention period more patients in the GDHT group received dobutamine when compared to the usual care group (55% vs 16%, p < 0.001). A meta-analysis of nine randomized trials showed no differences in postoperative mortality (risk ratio 0.85, 95% CI 0.59-1.23; p = 0.4; p for heterogeneity = 0.7; I2 = 0%) and in the overall complications rate (risk ratio 0.88, 95% CI 0.71-1.08; p = 0.2; p for heterogeneity = 0.07; I2 = 48%), but a reduced hospital length of stay in the GDHT group (mean difference (MD) - 1.6; 95% CI - 2.75 to - 0.46; p = 0.006; p for heterogeneity = 0.002; I2 = 74%).
Conclusions:
CI-guided hemodynamic therapy in the first 8 postoperative hours does not reduce 30-day mortality and severe complications during hospital stay when compared to usual care in cancer patients undergoing high-risk surgery.
Trial Registration:
www.clinicaltrials.gov , NCT01946269 . Registered on 16 September 2013.
More Related Videos
 03:07
Single-Port Robotic-assisted Transaxillary Breast-conserving Surgery: A Prospective, Single-arm, Non-randomized Phase IIa Clinical Trial
Published on: August 19, 2025
 07:14
A Quantitative Sensory Testing Paradigm to Obtain Measures of Pain Processing in Patients Undergoing Breast Cancer Surgery
Published on: January 18, 2018
Related Concept Videos
 01:09
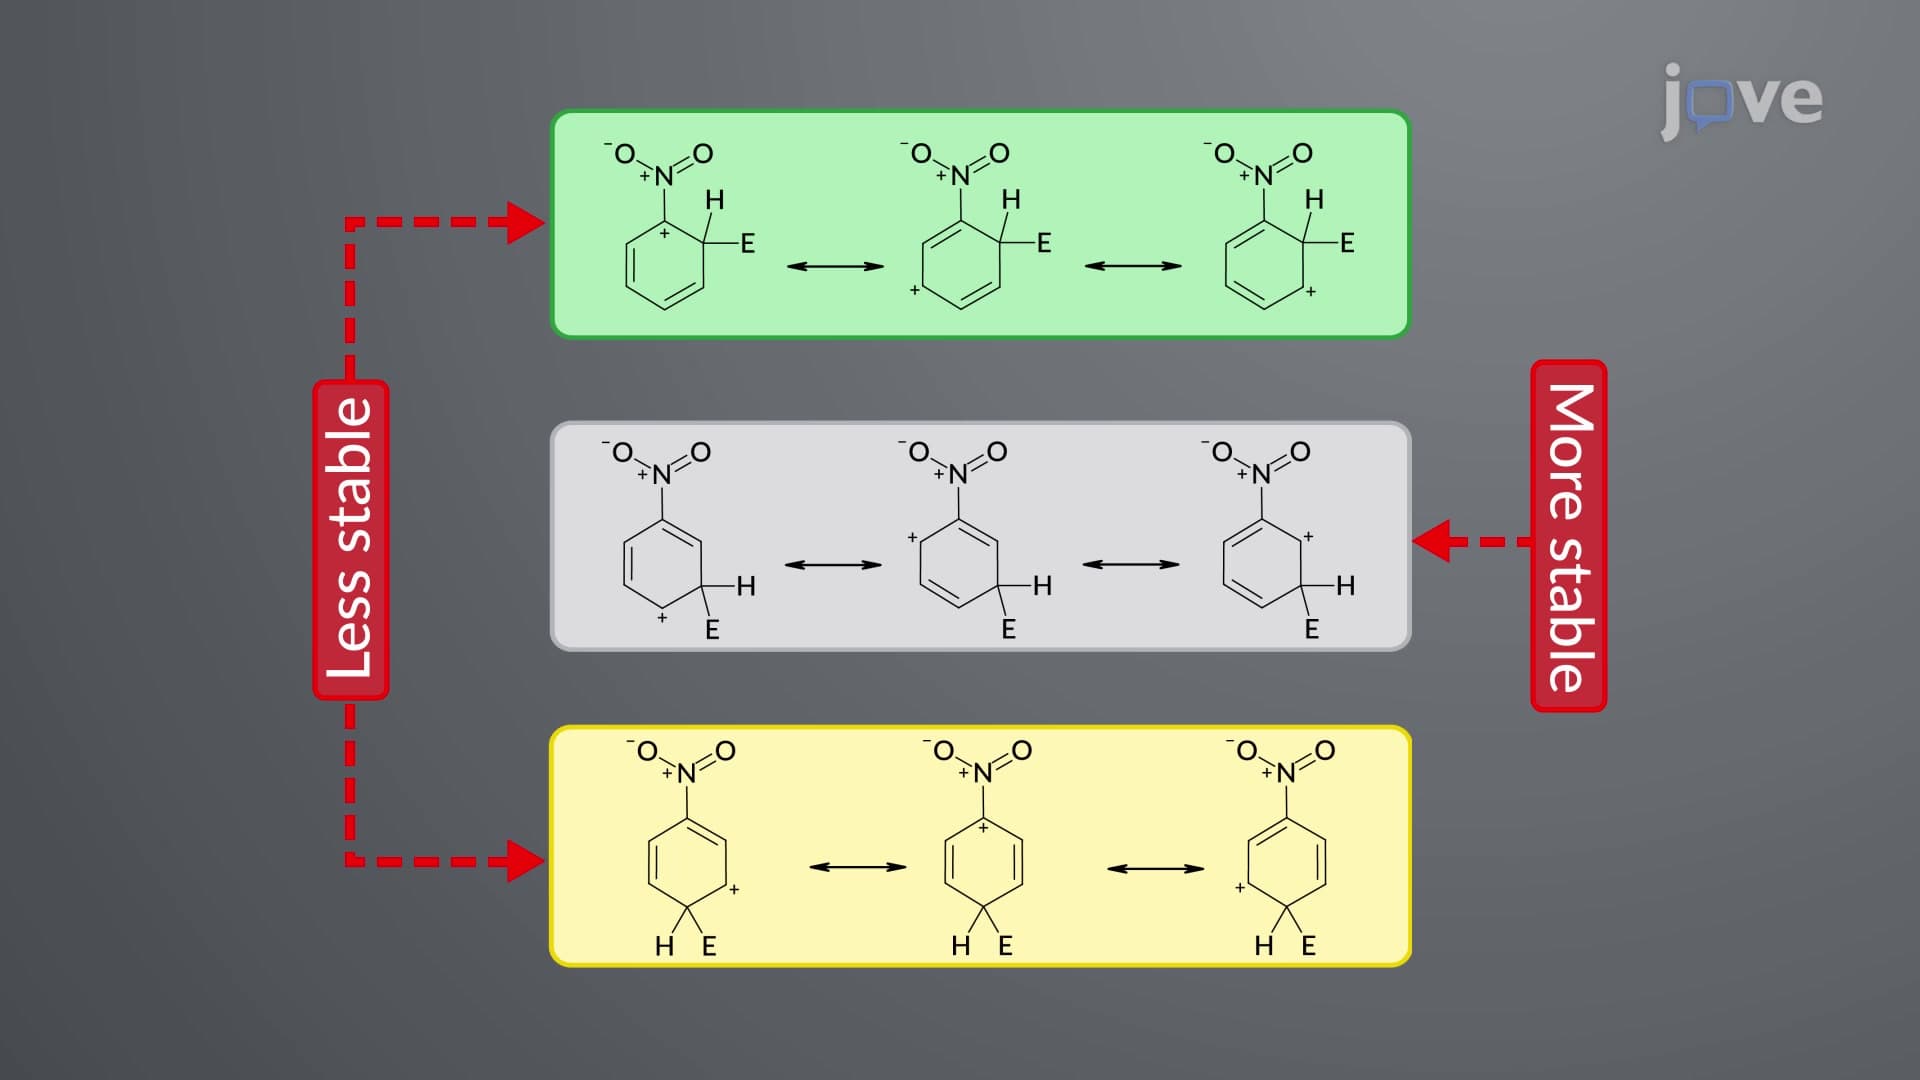
Directing Effect of Substituents: meta-Directing Groups
 01:16
Clinical Trials
There are four phases in a clinical trial. A phase one...
 01:11
Clinical Trials: Overview
 01:12
Statistical Software for Data Analysis and Clinical Trials
 02:49
Cancer Therapies
However, cancer treatments can pose several challenges, as therapies used to kill cancer cells are generally also toxic to normal cells. Moreover, cancer cells mutate rapidly and can develop resistance to chemical agents or radiation therapy. Besides, all types of cancer cells may not respond to the same therapy. Some cancer cells respond to one...
 01:13
meta-Directing Deactivators: –NO2, –CN, –CHO, –CO2R, –COR, –CO2H