Related Experiment Video
Updated: Sep 4, 2026
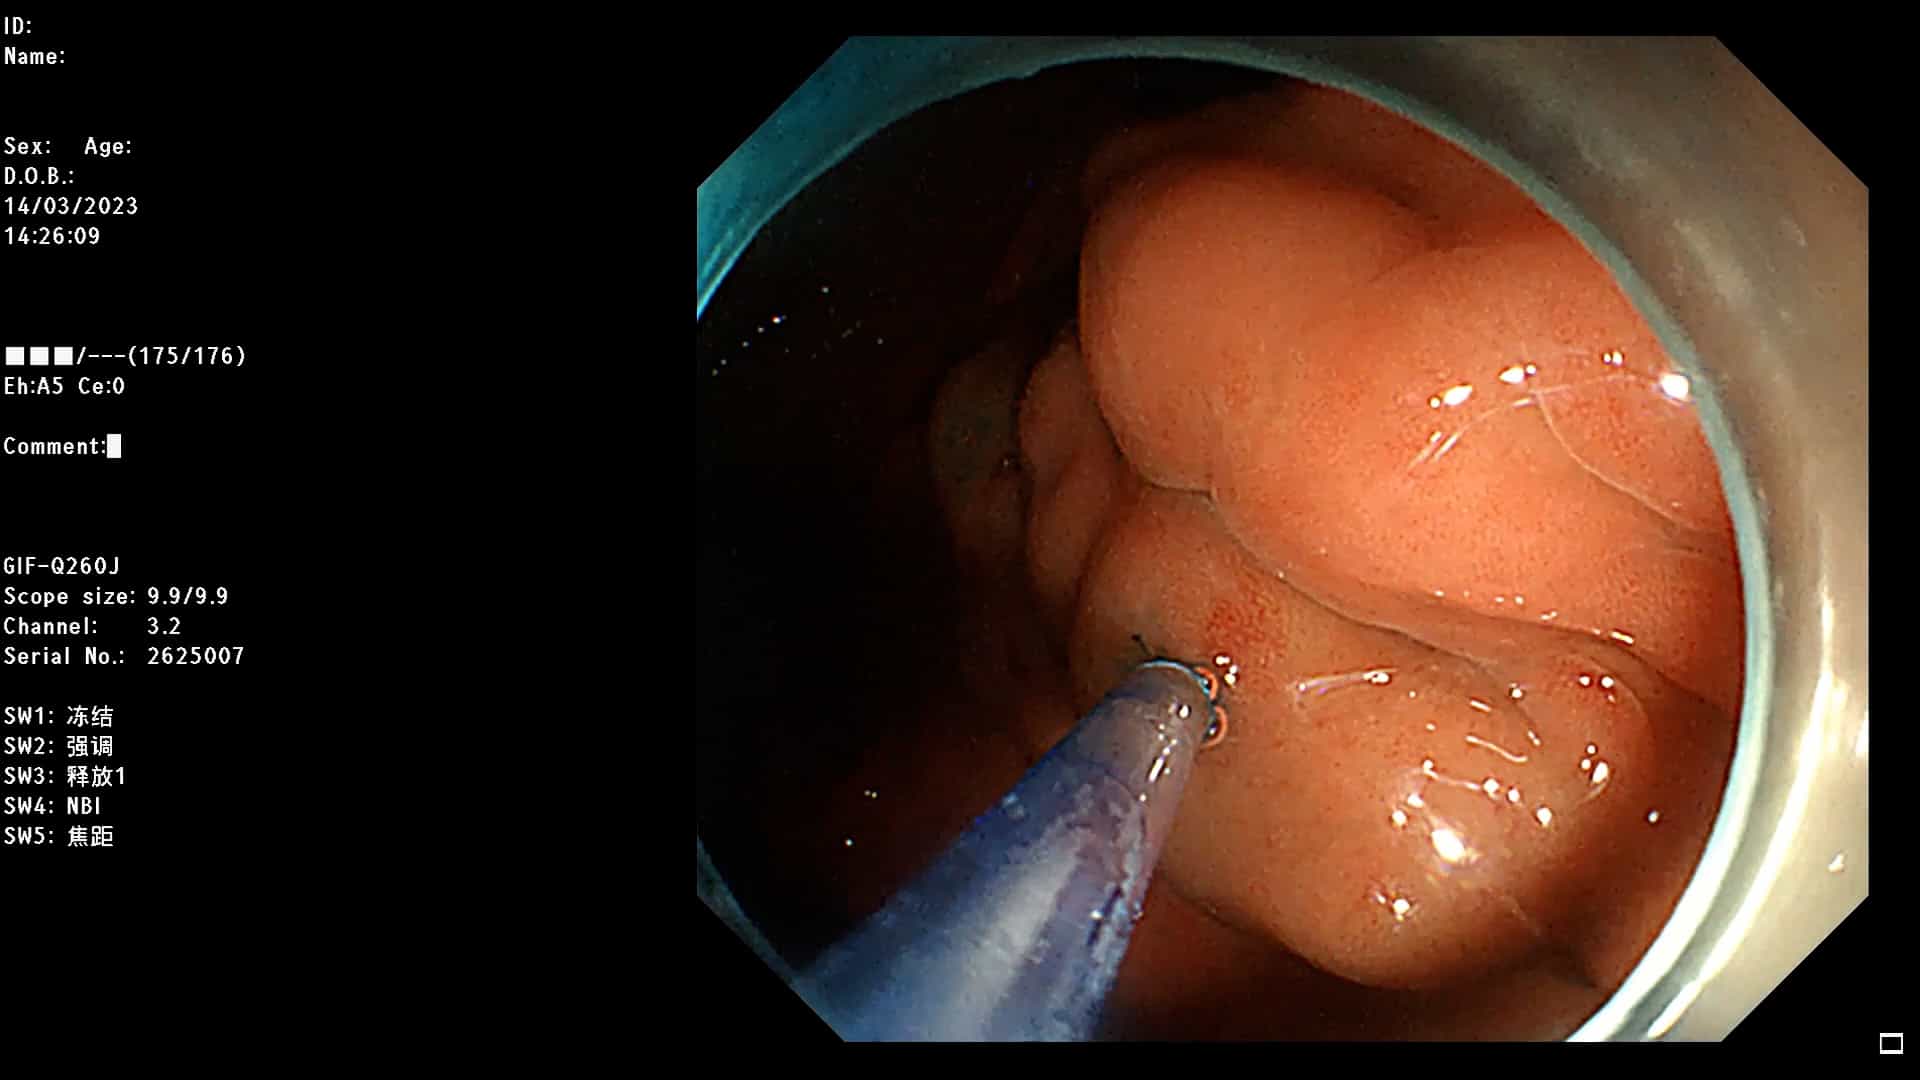
Endoscopic Injection Sclerotherapy Assisted by Cyanoacrylate and Clips for Gastroesophageal Varices
Published on: June 13, 2025
Treatment of endoscopy-negative NSAID-induced upper gastrointestinal symptoms with cimetidine: an international
1Department of Rheumatology, University Hospital Utrecht, The Netherlands.

Abstract:
In this double-blind multicentre trial, 127 patients on non-steroidal anti-inflammatory drugs (NSAIDs) who experienced gastrointestinal symptoms significant enough to warrant endoscopic evaluation, but without endoscopic evidence of mucosal damage, were randomized to receive cimetidine 400 mg b.d. or placebo for 4 weeks. Non-steroidal anti-inflammatory drug therapy was maintained at pre-trial doses for the duration of the study. After 4 weeks, 72% of cimetidine-treated patients experienced complete symptom resolution, as defined by a global symptom score of zero, compared with 49% on placebo. Complete disappearance of upper abdominal pain was achieved in 72% of the cimetidine-treated patients as opposed to 47% on placebo. Relief of heartburn was experienced by 87% of patients on cimetidine compared with 60% on placebo. Throughout treatment, the proportion of cimetidine-treated patients with nausea was consistently lower than in patients on placebo, while the two groups were similar with respect to disappearance of vomiting. At the completion of acute treatment, 27% of placebo-treated patients but only 12% of those on cimetidine were ineligible to continue maintenance due to persisting gastrointestinal symptoms. Patients who were symptom-free and required continuation of NSAID therapy were followed for 6 months during which they were re-randomized to receive cimetidine 400 mg nocte or placebo. Of the 105 patients included in this maintenance treatment phase of the study, 11% of the cimetidine-treated patients and 10% of those on placebo experienced relapse of symptoms. However, the mean time to relapse was 120 days with cimetidine compared with 35 days with placebo.(ABSTRACT TRUNCATED AT 250 WORDS)

Related Concept Videos
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...
 01:16
Treating Helicobacter pylori in Peptic Ulcers: Antimicrobial Therapy
 01:21
Drugs for Treatment of Constipation-Predominant IBS
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...