Related Experiment Video
Updated: Feb 10, 2026

A Procedure for Implanting a Spinal Chamber for Longitudinal In Vivo Imaging of the Mouse Spinal Cord
Published on: December 3, 2014
Reducing risk of spinal haematoma from spinal and epidural pain procedures
Harald Breivik1,2,3, Hilde Norum2,3, Christian Fenger-Eriksen4
1Oslo University Hospital, Division of Emergencies and Critical Care, Department of Pain Management and Research, PB 4956 Nydalen, 0424 Oslo, Norway, Phone: +47 23073691, Fax: +47 23073690.

Background And Aims:
Central neuraxial blocks (CNB: epidural, spinal and their combinations) and other spinal pain procedures can cause serious harm to the spinal cord in patients on antihaemostatic drugs or who have other risk-factors for bleeding in the spinal canal. The purpose of this narrative review is to provide a practise advisory on how to reduce risk of spinal cord injury from spinal haematoma (SH) during CNBs and other spinal pain procedures. Scandinavian guidelines from 2010 are part of the background for this practise advisory.
Methods:
We searched recent guidelines, PubMed (MEDLINE), SCOPUS and EMBASE for new and relevant randomised controlled trials (RCT), case-reports and original articles concerning benefits of neuraxial blocks, risks of SH due to anti-haemostatic drugs, patient-related risk factors, especially renal impairment with delayed excretion of antihaemostatic drugs, and specific risk factors related to the neuraxial pain procedures.
Results And Recommendations:
Epidural and spinal analgesic techniques, as well as their combination provide superior analgesia and reduce the risk of postoperative and obstetric morbidity and mortality. Spinal pain procedure can be highly effective for cancer patients, less so for chronic non-cancer patients. We did not identify any RCT with SH as outcome. We evaluated risks and recommend precautions for SH when patients are treated with antiplatelet, anticoagulant, or fibrinolytic drugs, when patients' comorbidities may increase risks, and when procedure-specific risk factors are present. Inserting and withdrawing epidural catheters appear to have similar risks for initiating a SH. Invasive neuraxial pain procedures, e.g. spinal cord stimulation, have higher risks of bleeding than traditional neuraxial blocks. We recommend robust monitoring routines and treatment protocol to ensure early diagnosis and effective treatment of SH should this rare but potentially serious complication occur.
Conclusions:
When neuraxial analgesia is considered for a patient on anti-haemostatic medication, with patient-related, or procedure-related risk factors, the balance of benefits against risks of bleeding is decisive; when CNB are offered exclusively to patients who will have a reduction of postoperative morbidity and mortality, then a higher risk of bleeding may be accepted. Robust routines should ensure appropriate discontinuation of anti-haemostatic drugs and early detection and treatment of SH.
Implications:
There is an on-going development of drugs for prevention of thromboembolic events following surgery and childbirth. The present practise advisory provides up-to-date knowledge and experts' experiences so that patients who will greatly benefit from neuraxial pain procedures and have increased risk of bleeding can safely benefit from these procedures. There are always individual factors for the clinician to evaluate and consider. Increasingly it is necessary for the anaesthesia and analgesia provider to collaborate with specialists in haemostasis. Surgeons and obstetricians must be equally well prepared to collaborate for the best outcome for their patients suffering from acute or chronic pain. Optimal pain management is a prerequisite for enhanced recovery after surgery, but there is a multitude of additional concerns, such as early mobilisation, early oral feeding and ileus prevention that surgeons and anaesthesia providers need to optimise for the best outcome and least risk of complications.


Related Concept Videos
 01:26
Spinal Cord
 01:54
The Spinal Cord
 01:10
Spinal Cord: Information Processing
Sensory Information Processing
Sensory information processing begins at the sensory receptors located in the skin and other tissues, which detect somatic sensory stimuli such as touch, temperature, or pain. These receptors function as catalysts, initiating...
 01:21
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
 01:19
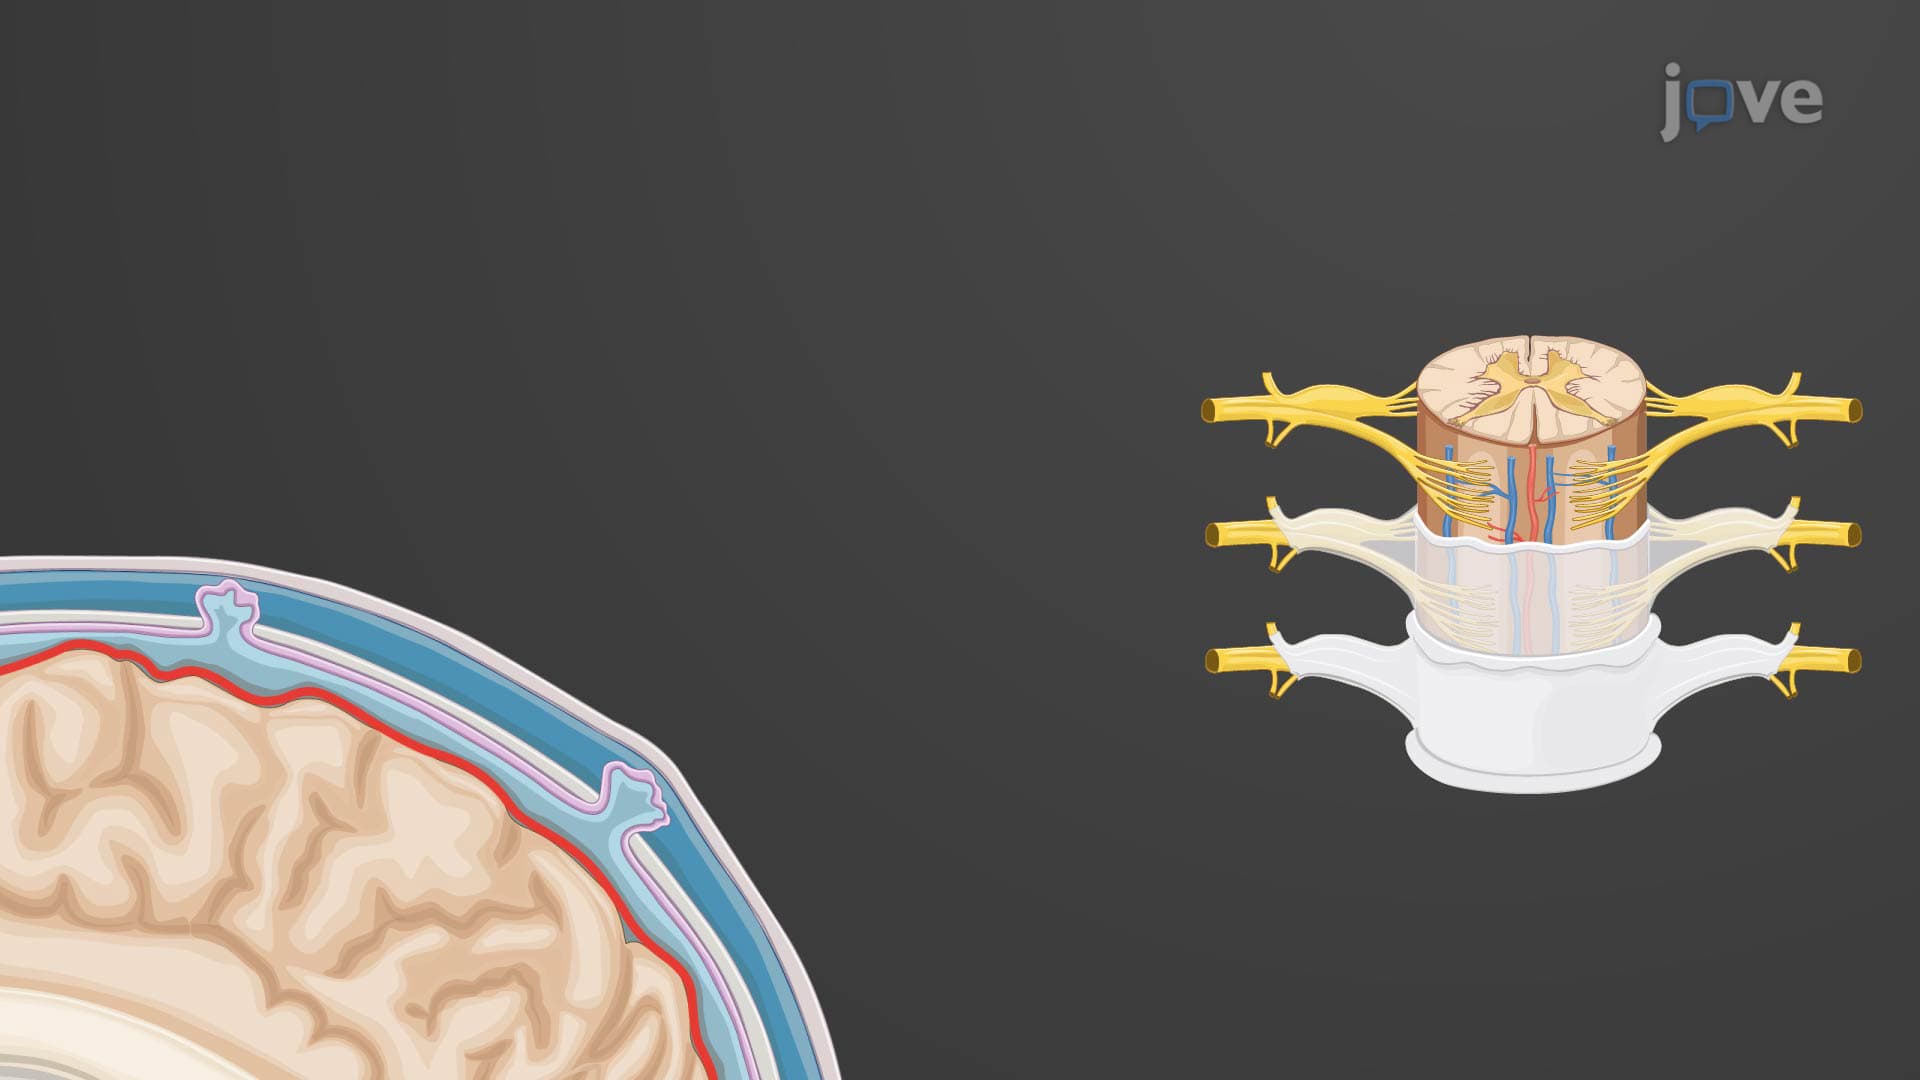
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:23
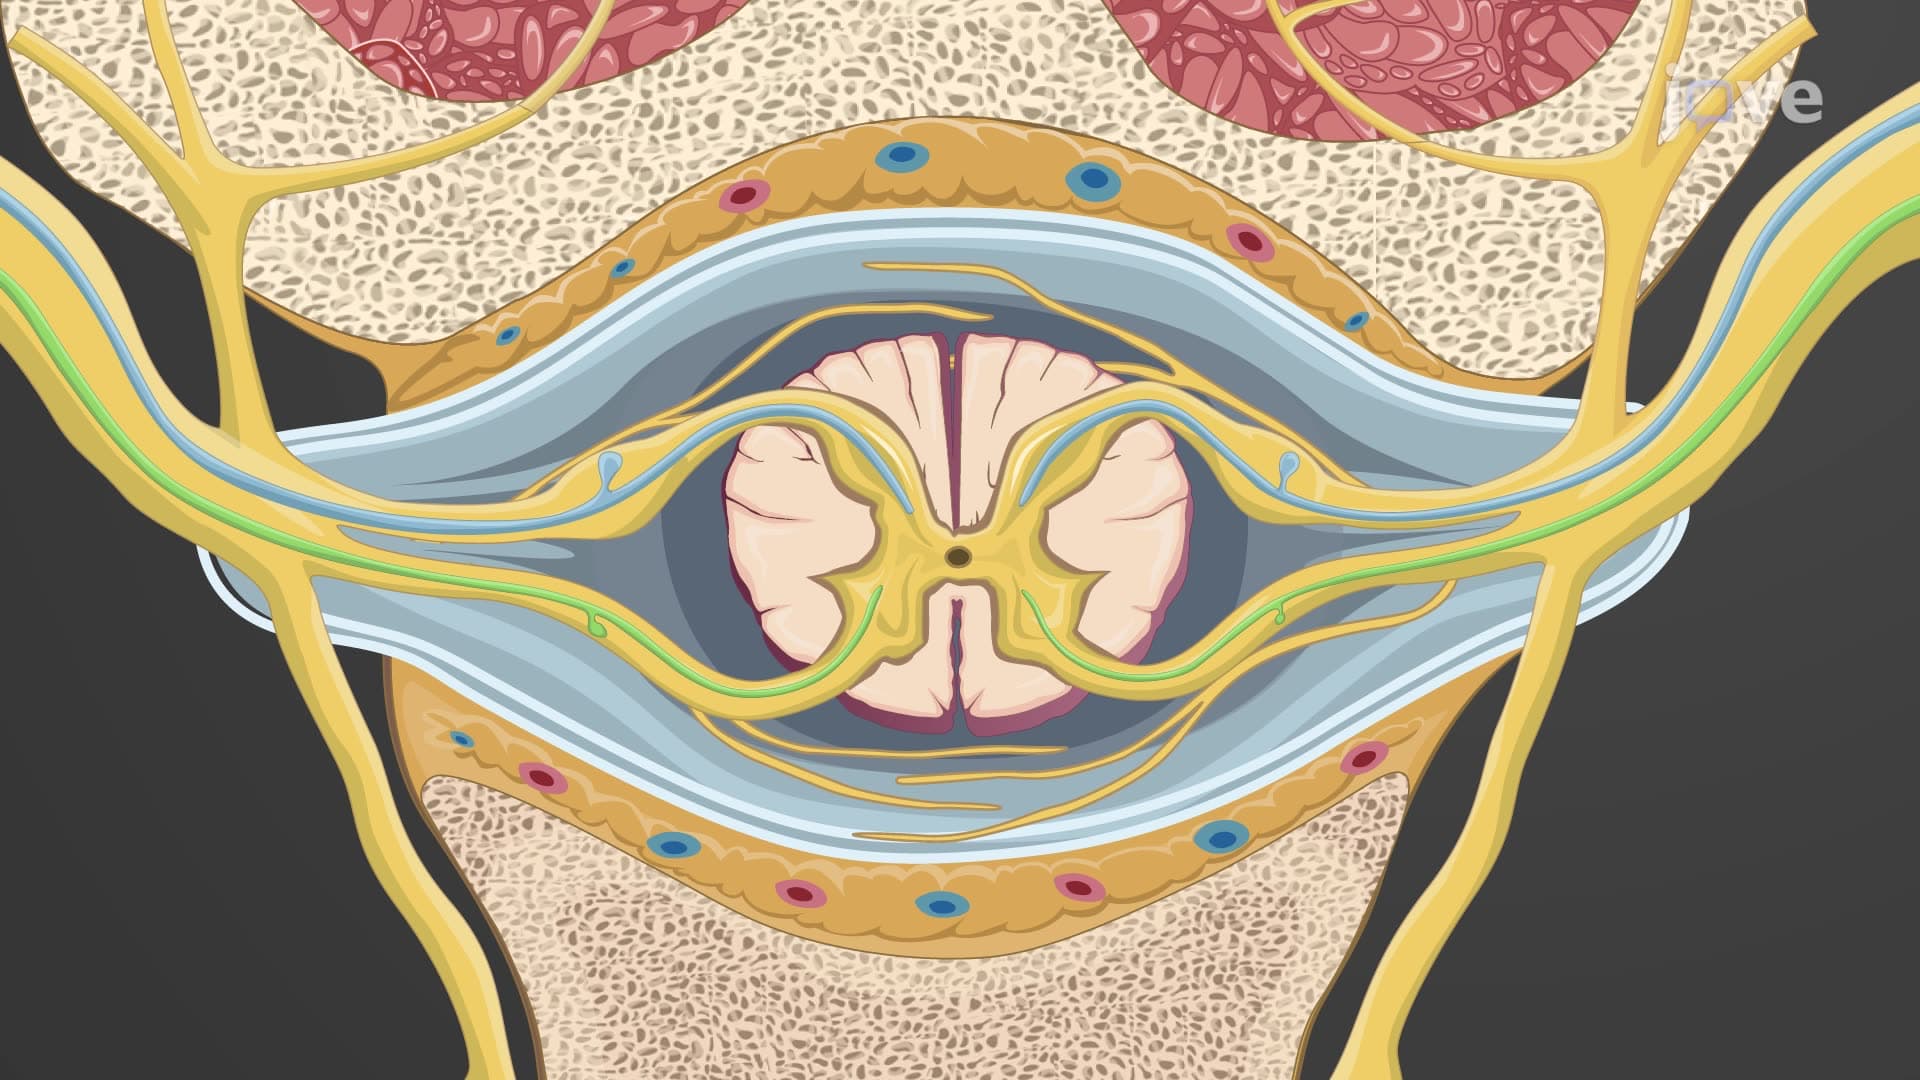
Spinal Nerves: Anatomy
There are 31 bilateral pairs of spinal nerves, each emerging from the spinal cord through the intervertebral foramina—openings between adjacent vertebrae. These nerves are...