Related Experiment Video
Updated: Feb 10, 2026

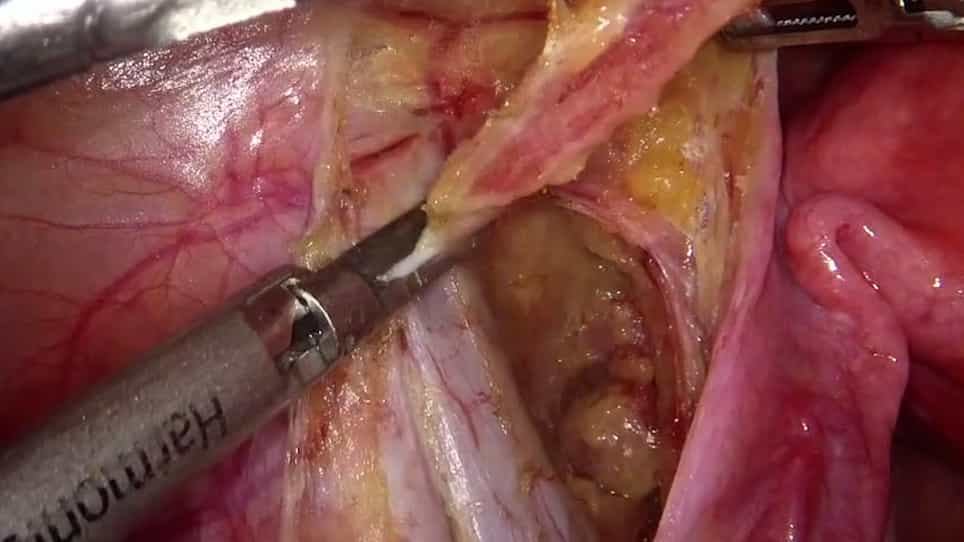
Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Laparoscopic treatment of rectal cancer and lateral pelvic lymph node dissection: are they obsolete?
Shigeo Toda1, Hiroya Kuroyanagi2, Shuichiro Matoba2
1Department of Gastroenterological Surgery, Toranomon Hospital, Tokyo, Japan - shigeo-toda@toranomon.gr.jp.

Abstract:
Laparoscopic surgery for rectal cancer offers favorable short-term results without compromising long term oncological outcomes so far, according to the data from major trials. For this reason, it is currently considered as a standard option for rectal cancer surgery. The learning curve of laparoscopic rectal cancer surgery is generally longer compared to colon cancer. Appropriate standardization and training of laparoscopic rectal cancer surgery is required. Several RCTs suggested the potential negative effect on quality of resected specimen, which can increase local recurrence. The long-term outcomes - especially local recurrence rate - of these RCTs are awaited. Lateral pelvic lymph node dissection (LPLND) has a certain effect of reducing local recurrence of rectal cancer even after neoadjuvant radiotherapy. Since LPLND is associated with postoperative morbidity, we should carefully select the candidate to maximize the effect of LPLND and minimize the morbidity caused by LPLND. Recent advancements in imaging study such as CT and MRI enable us to find the suitable candidates for LPLND. The morbidity caused by LPLND could be reduced by minimally invasive surgeries such as laparoscopic surgery and robotic surgery. We have to improve oncological outcomes and reduce morbidity by the multidisciplinary strategy for rectal cancer including total mesorectal excision, neoadjuvant chemoradiotherapy and LPLND together with laparoscopic surgery.
Related Concept Videos
 01:23
Detailed Structure and Function of Lymph Nodes
From a histological perspective, lymph nodes can be split into two main areas: the superficial cortex and the deep medulla. The outer cortex is populated by dendritic cells, macrophages, and B lymphocytes, which are densely packed into follicles. When these B-lymphocytes are presented...
 02:56
Treatment Resistant Cancers
 01:27
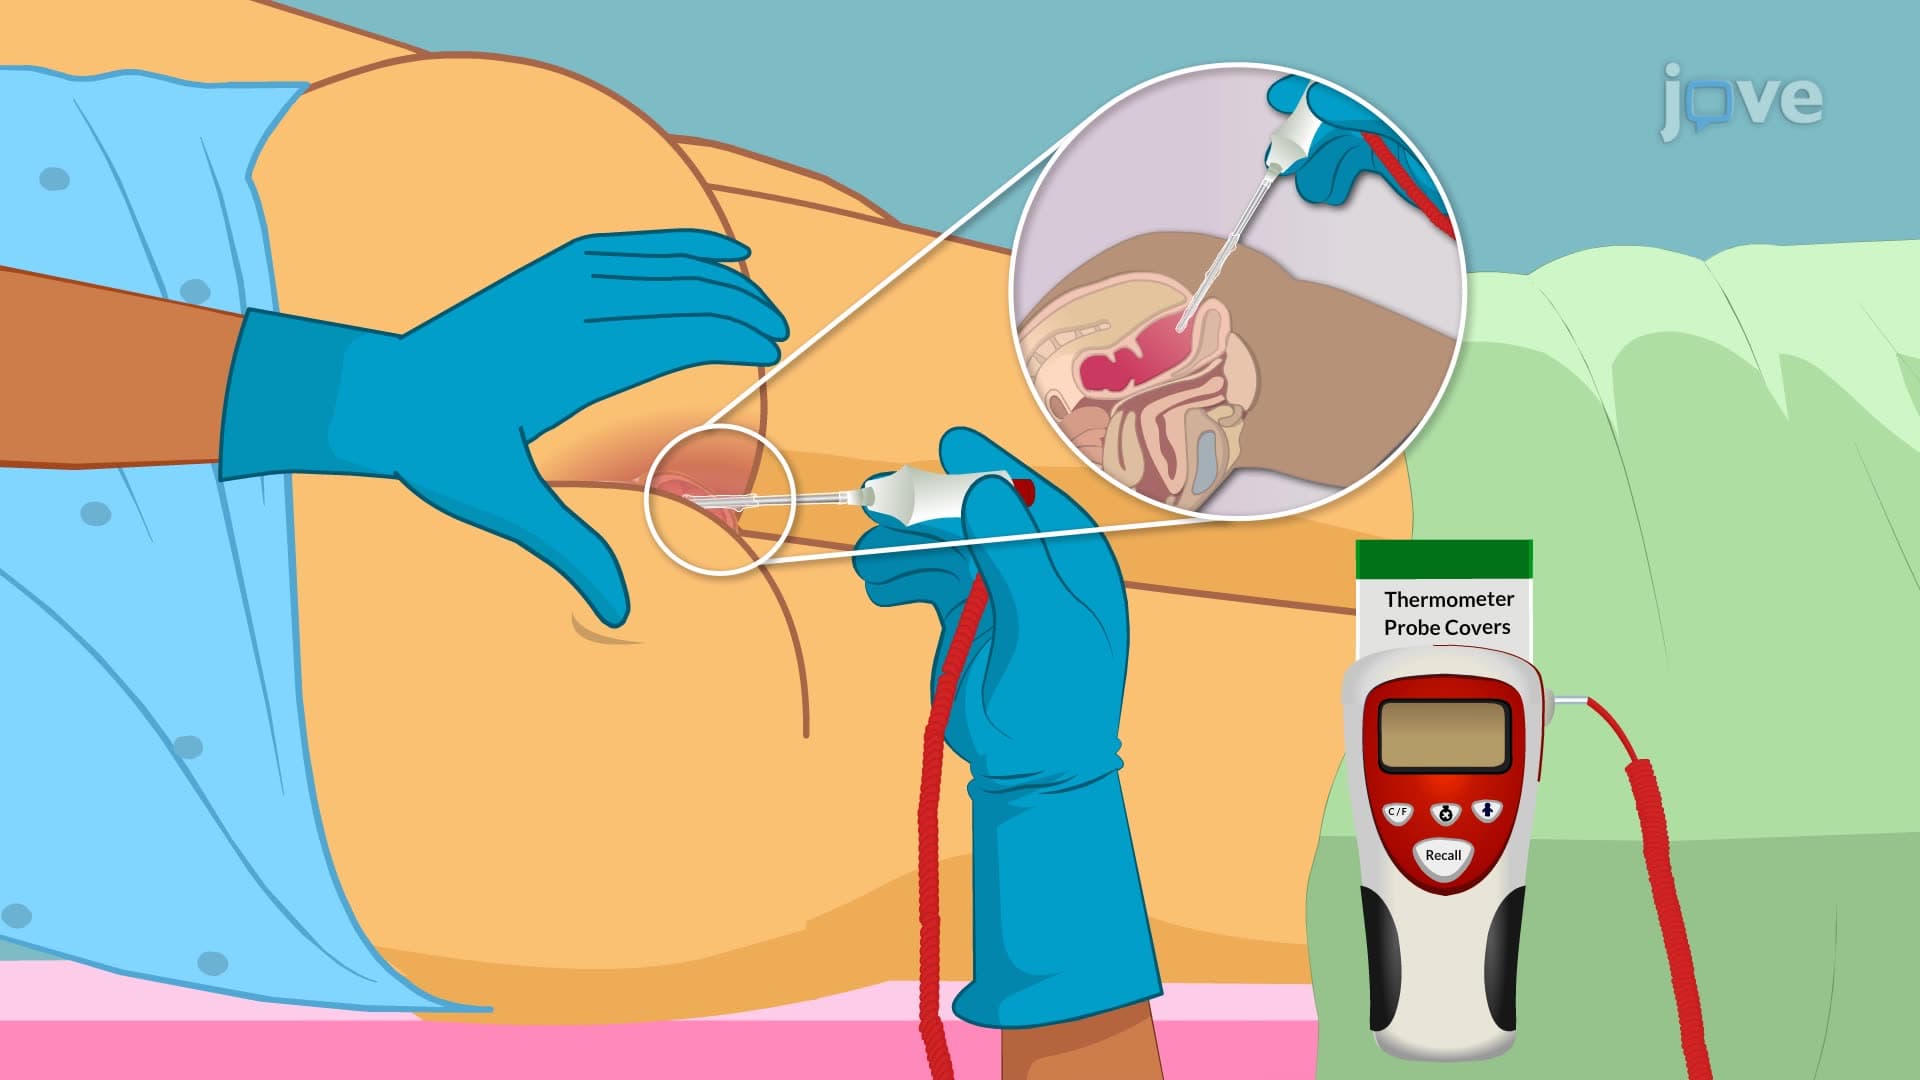
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 01:26
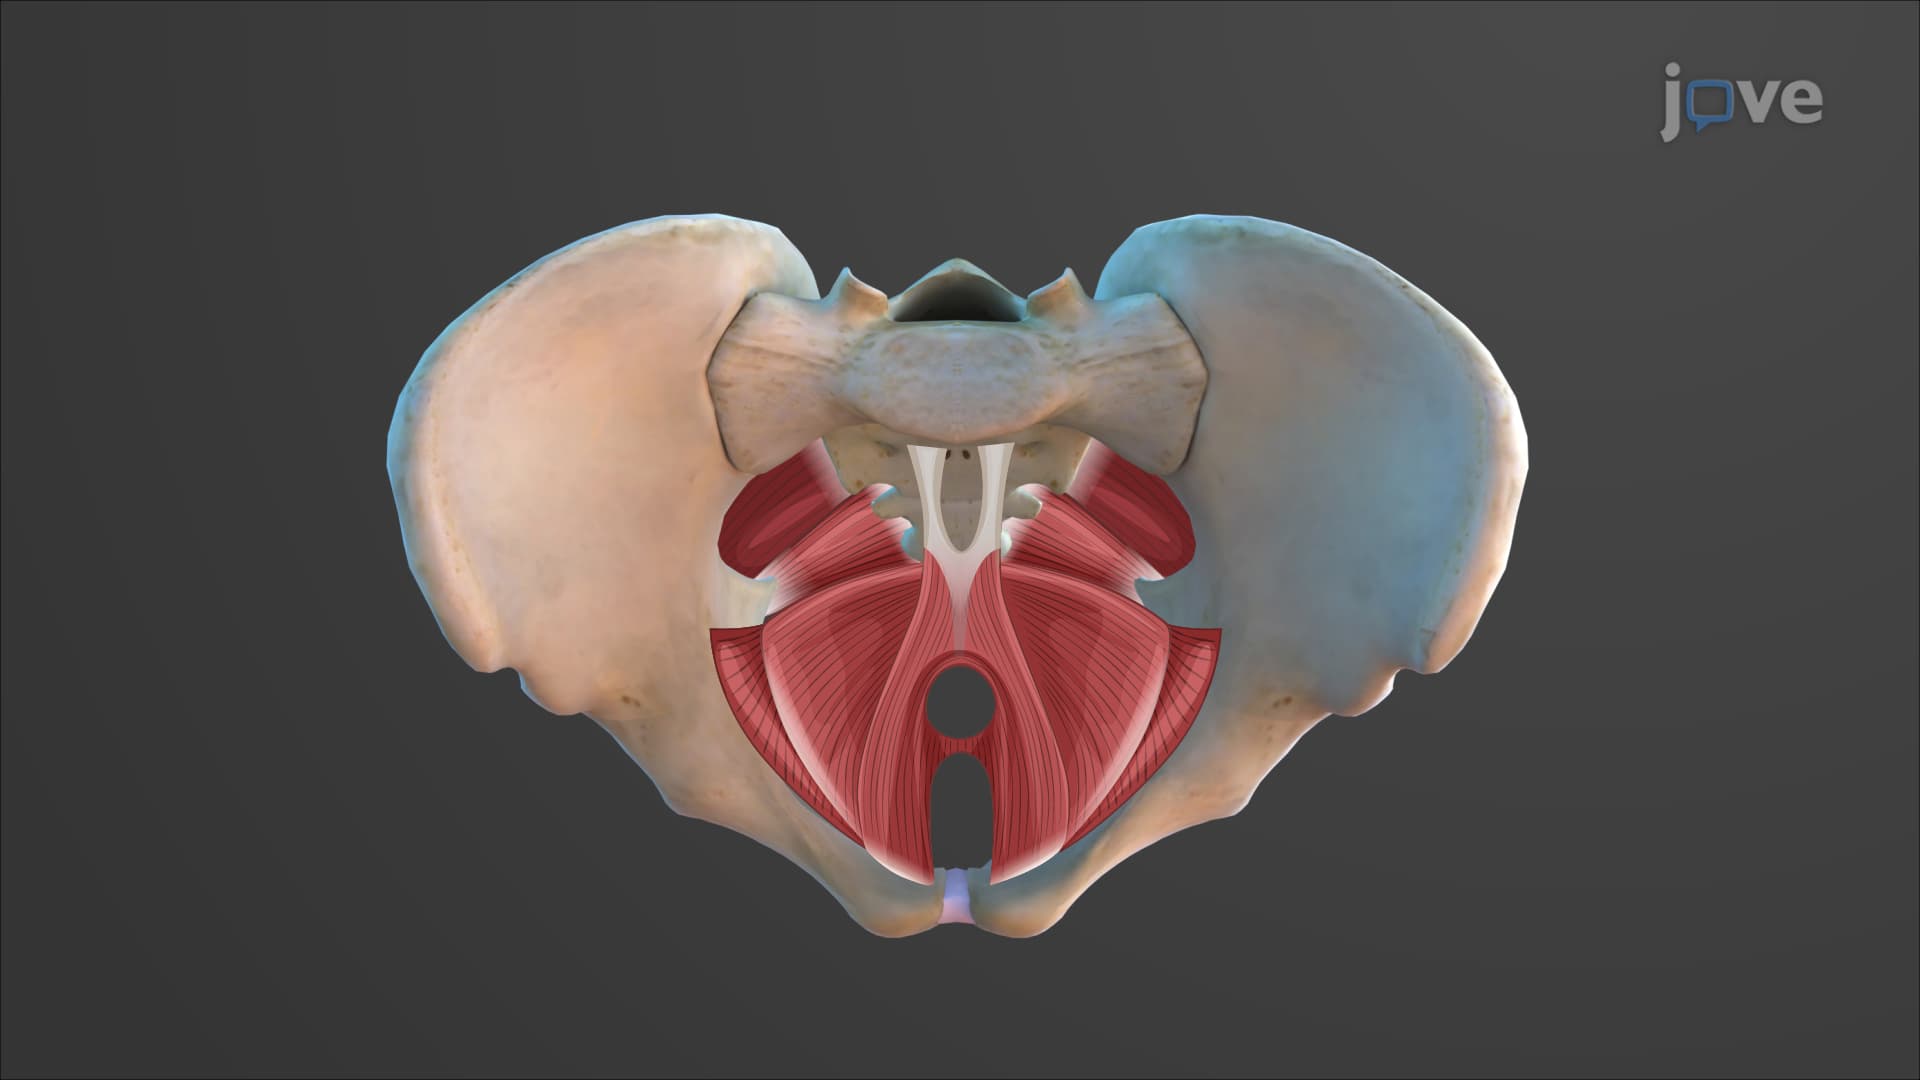
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:28
Lateralization
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...