Related Experiment Video
Updated: Feb 10, 2026


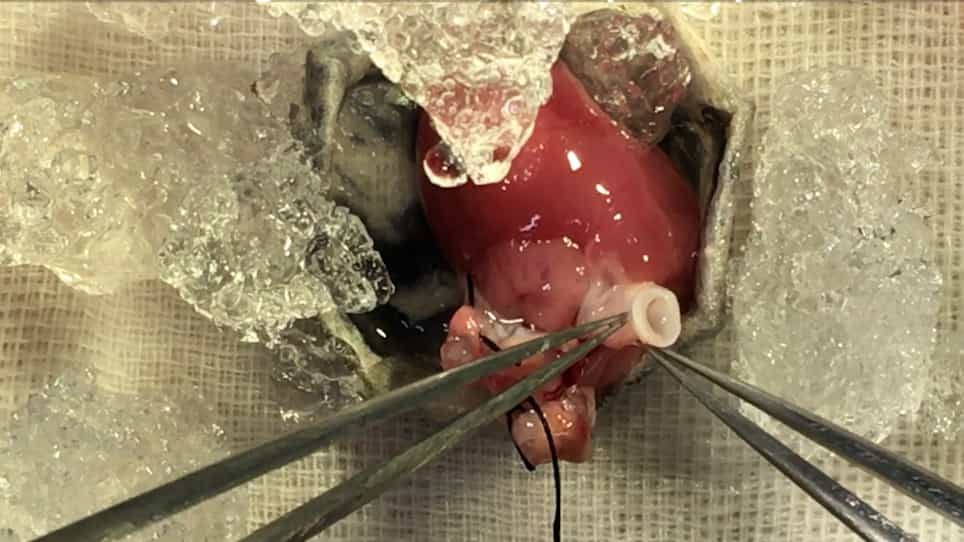
Murine Corneal Transplantation: A Model to Study the Most Common Form of Solid Organ Transplantation
Published on: November 17, 2014
Impact of High-Dose Acyclovir Cytomegalovirus Prophylaxis Failure in Abdominal Solid Organ Transplant Recipients
Magdalena Siodlak1, Margaret R Jorgenson1, Jillian L Descourouez1
1Department of Pharmacy, University of Wisconsin Hospital and Clinics, Madison, Wisconsin.

Study Objective:
To evaluate the clinical course and long-term impact of high-dose acyclovir (HD-A, 800 mg 4 times/day) cytomegalovirus (CMV) prophylaxis failure in a CMV-seropositive abdominal solid organ transplant population.
Design:
Retrospective cohort study.
Setting:
Tertiary academic medical center.
Patients:
A total of 691 adults who received solid organ transplants between January 1, 2008, and June 30, 2013, without lymphocyte-depleting induction and were prescribed 3 months of HD-A prophylaxis at the time of hospital discharge. Of those patients, 54 experienced prophylaxis failure, defined as CMV detected via molecular diagnostics or on biopsy while receiving HD-A (prophylaxis failure group), and 637 did not (comparator group).
Measurements And Main Results:
Mean ± SD time to failure was 64 ± 23 days; 98% (53/54 patients) was attributable to viremia diagnosed via positive polymerase chain reaction (PCR). Of these 53 patients, 34% (18 patients) were below the quantifiable range when detected. Median initial and peak CMV PCR for quantifiable readings were 1531 IU/ml (interquartile range [IQR] less than 250-2947) and 4442 IU/ml (IQR less than 250-32,500); 19 (36%) had a single detectable CMV PCR. Treatment was required in 56% (30/54 patients), with a median duration of 63 days; 40% (12 patients) were treated with valganciclovir alone, and the remainder received intravenous ganciclovir. CMV disease resulted in hospitalization in 28% (15 patients). Immunosuppression was modified in 52% (28 patients). The rate of CMV recurrence after 100 days was significantly higher in the prophylaxis failure group (59% vs 13%, p<0.0001). Higher rates of rejection; higher rates of 1-, 3-, and 5-year graft failure; and higher rates of 1-, 3-, and 5-year mortality were noted in the prophylaxis failure group on univariate analysis (43% vs 30%, p=0.045; 8%, 17%, and 34% vs 4%, 12%, and 17%, p=0.006; and 6%, 17%, and 26% vs 1%, 6%, and 10%, p=0.003, respectively). Multivariate analysis demonstrated an increased risk of graft failure in the prophylaxis failure group (hazard ratio [HR] 1.76, 95% confidence interval [CI] 1-3.1, p=0.0499) and a trend to increased mortality (HR 1.6, 95% CI 0.83-3.1, p=0.16).
Conclusion:
Prophylaxis failure with HD-A was mostly limited to mild viremia; however, it was associated with significantly reduced long-term graft survival, likely reflecting the negative impact of CMV viremia.

Related Concept Videos
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 02:37
Metallic Solids
All metallic solids exhibit high thermal and electrical conductivity, metallic luster, and malleability....
 02:22
Structures of Solids
 02:18
Network Covalent Solids
To break or to melt a covalent network solid, covalent bonds must be broken. Because covalent bonds are relatively strong, covalent network solids are typically...
 02:54
Molecular and Ionic Solids
Molecular Solids
Molecular crystalline solids, such as ice, sucrose (table sugar), and iodine, are solids that are composed of neutral molecules as their constituent units. These molecules are held together by weak intermolecular forces such as London dispersion forces, dipole-dipole interactions, or hydrogen bonds, which...
 01:19
Impact of Groups on Groups