Related Experiment Video
Updated: Feb 10, 2026


A Multicenter MRI Protocol for the Evaluation and Quantification of Deep Vein Thrombosis
Published on: June 2, 2015
Evaluation of coronary features of HIV patients presenting with ACS: The CUORE, a multicenter study
Mattia Peyracchia1, Giulia De Lio1, Chiara Montrucchio1
1Division of Cardiology, Città Della Salute e Della Scienza "Molinette" Hospital, University of Turin, Turin, Italy.

Insights
HIV patients with acute coronary syndrome (ACS) show distinct coronary plaque features on intravascular ultrasound (IVUS). Advanced HIV infection is linked to higher risks of non-calcific plaques and adverse cardiovascular events.
Area of Science:
- Cardiology
- Infectious Diseases
- Vascular Biology
Background:
- Human immunodeficiency virus (HIV) infection is associated with an increased risk of cardiovascular disease.
- Coronary plaque characteristics in HIV patients with acute coronary syndrome (ACS) are not well understood compared to non-HIV patients.
Purpose of the Study:
- To investigate differences in coronary plaque morphology and clinical outcomes between HIV-positive and HIV-negative patients presenting with ACS.
- To assess the impact of advanced HIV infection (CD4 count <200/mm³).
Main Methods:
- Multicenter case-control study comparing HIV and non-HIV patients with ACS undergoing intravascular ultrasound (IVUS).
- Propensity score matching was used to adjust for baseline differences.
- Primary endpoint: multivessel disease. Secondary endpoints: IVUS plaque features, major adverse cardiovascular events (MACE), myocardial infarction (MI) recurrence, and stent thrombosis (ST).
Main Results:
- HIV patients exhibited lower plaque burden and a higher prevalence of hyperechoic non-calcified plaques.
- Patients with advanced HIV infection (CD4 <200/mm³) showed a higher prevalence of hypoechoic plaques.
- Advanced HIV infection was associated with increased MACE, MI recurrence, and stent thrombosis.
Conclusions:
- HIV patients present with unique coronary plaque morphologies on IVUS, even after clinical variable adjustment.
- Advanced HIV infection is a significant risk factor for non-calcific plaques and poorer cardiovascular outcomes, including ACS recurrence.
Background And Aims:
The risk of recurrence of myocardial infarction (MI) in HIV patients presenting with acute coronary syndrome (ACS) is well known, but there is limited evidence about potential differences in coronary plaques compared to non-HIV patients.
Methods:
In this multicenter case-control study, HIV patients presenting with ACS, with intravascular-ultrasound (IVUS) data, enrolled between February 2015 and June 2017, and undergoing highly active antiretroviral therapy (HAART), were retrospectively compared to non-HIV patients presenting with ACS, before and after propensity score with matching, randomly selected from included centers. Primary end-point was the prevalence of multivessel disease. Secondary end-points were the prevalence of abnormal features at IVUS, the incidence of major-acute-cardiovascular-events (MACE), a composite end point of cardiovascular death, MI, target lesion revascularization (TLR), stent thrombosis (ST), non-cardiac death and target vessel revascularization (TVR). For each end-point, a subgroup analysis was conducted in HIV patients with CD4 cell count <200/mm3.
Results:
Before propensity score, 66 HIV patients and 120 non-HIV patients were selected, resulting in 20 and 40 after propensity score. Patients with multivessel disease were 11 and 17, respectively (p = 0.56). IVUS showed a lower plaque burden (71% vs. 75%, p < 0.001) and a higher prevalence of hyperechoic non-calcified plaques (100% vs. 35%, p < 0.05) in HIV patients; a higher prevalence of hypoechoic plaques (7% vs. 0%, p < 0.05), a higher incidence of MACE (17.4% vs. 9.1% vs. l'8.0%, p < 0.05), MI recurrence (17.2% vs. 0.0% vs. 2.3%, p < 0.05), and ST (6.7% vs. 0.3% vs. 03%, p < 0.05) in HIV patients with CD4 < 200/mm3.
Conclusions:
Our study may provide a part of the pathophysiological basis of the differences in coronary arteries between HIV-positive and HIV-negative patients, suggesting that the former present with peculiar morphological features at IVUS, even after adjustment for clinical variables. Furthermore, we confirmed that an advanced HIV infection is associated with a high risk of non-calcific plaques and with a worse prognosis, including cardiovascular events and ACS recurrence.
More Related Videos
 13:50
Sequencing of Bacterial Microflora in Peripheral Blood: our Experience with HIV-infected Patients
Published on: June 11, 2011
 13:58
Amplifying and Quantifying HIV-1 RNA in HIV Infected Individuals with Viral Loads Below the Limit of Detection by Standard Clinical Assays
Published on: September 26, 2011
Related Concept Videos
 01:20
AC Sources
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are:
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:31
Resistor in an AC Circuit
One-way current through the meter is measured using diodes. A diode is a device with better conductivity in one direction compared to the other; in its ideal state, it has zero resistance in one direction and allows...
 01:26
Power in an AC Circuit
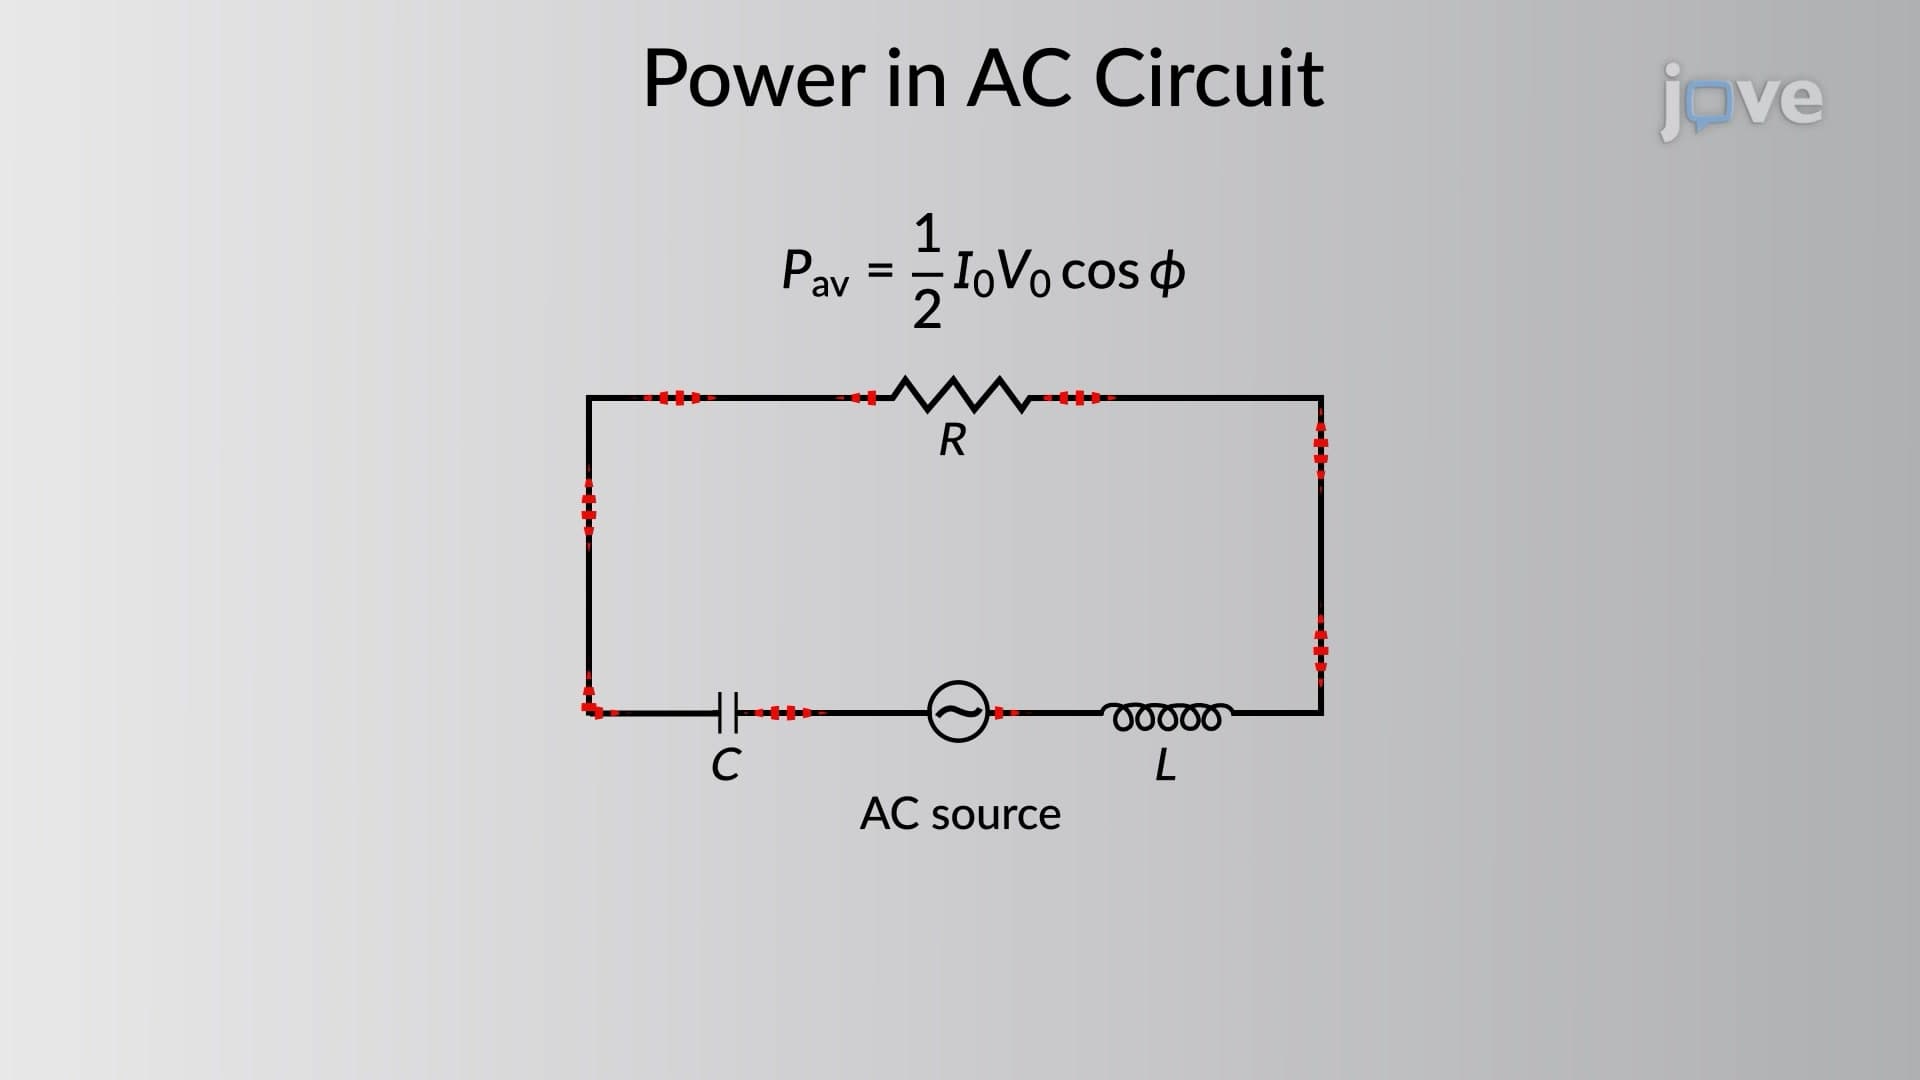
In a DC circuit, there is no sinusoidal waveform associated with the supply; the voltages and currents are...
 01:21
Coronary Circulation
Coronary circulation begins at the base of the aorta, where two main arteries arise—the left and right coronary arteries. These arteries encircle the heart in the coronary sulcus and supply the...