
Comparing the Effect of Throughput and Output Factors on Emergency Department Crowding: A Retrospective Observational
Malcolm B Doupe1, Dan Chateau2, Alecs Chochinov3
1Manitoba Centre for Health Policy, Max Rady College of Medicine, University of Manitoba, Winnipeg, Manitoba, Canada; Department of Emergency Medicine, Max Rady College of Medicine, University of Manitoba, Winnipeg, Manitoba, Canada; Department of Community Health Sciences, Max Rady College of Medicine, University of Manitoba, Winnipeg, Manitoba, Canada.

Study Objective:
This study compares how throughput and output factors affect emergency department (ED) median waiting room time.
Methods:
Administrative health care use records were used to identify all daytime (8 am to 8 pm) visits made to adult EDs in Winnipeg, Canada, between April 1, 2012, and March 31, 2013. First, we measured the waiting room time (from patient registration until transfer into the ED) of each index visit (incoming patient). We then linked each index visit to a group of existing patients surrounding it and counted the number of existing patients engaged in throughput processes (radiographs, computed tomography [CT] scans, advanced diagnostic tests) and one output process (waiting to be hospitalized). Regression analysis was used to measure how strongly each factor uniquely affected incoming patient median waiting room time, stratified by the acuity level.
Results:
Analyses were performed on 143,172 index visits. On average, 153.4 radiographs and 48.5 CT scans were conducted daily, whereas 45.3 patients were admitted daily to hospital. Median waiting room time was shortest (8.0 minutes) for the highest-acuity index visits and was not influenced by these throughput or output factors. For all other index visits, median waiting room time was associated strongly with the number of existing patients receiving radiographs, and, to a lesser extent, with the number of existing patients receiving CT scans and waiting for hospital admission.
Conclusion:
Both throughput and output factors affect how long newly arriving ED patients remain in the waiting room. This suggests that a range of strategies may help to reduce ED wait time, each requiring stronger ED and hospital partnerships.
More Related Videos
 04:05
Author Spotlight: Unveiling Prognostic Indicators in Heart Failure - The Role of Phase Angle and Bioelectrical Impedance Analysis
Published on: June 30, 2023
 07:52
Expired CO2 Measurement in Intubated or Spontaneously Breathing Patients from the Emergency Department
Published on: January 29, 2011
Related Concept Videos
 01:11
Observational Studies
There are three types of observational studies – Prospective, retrospective, and cross-sectional.
Prospective Study
Prospective studies, also known as longitudinal or cohort studies, are carried out by collecting future data from groups sharing similar characteristics. One...
 01:27
Emerging Adulthood
 02:30
Naturalistic Observations
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
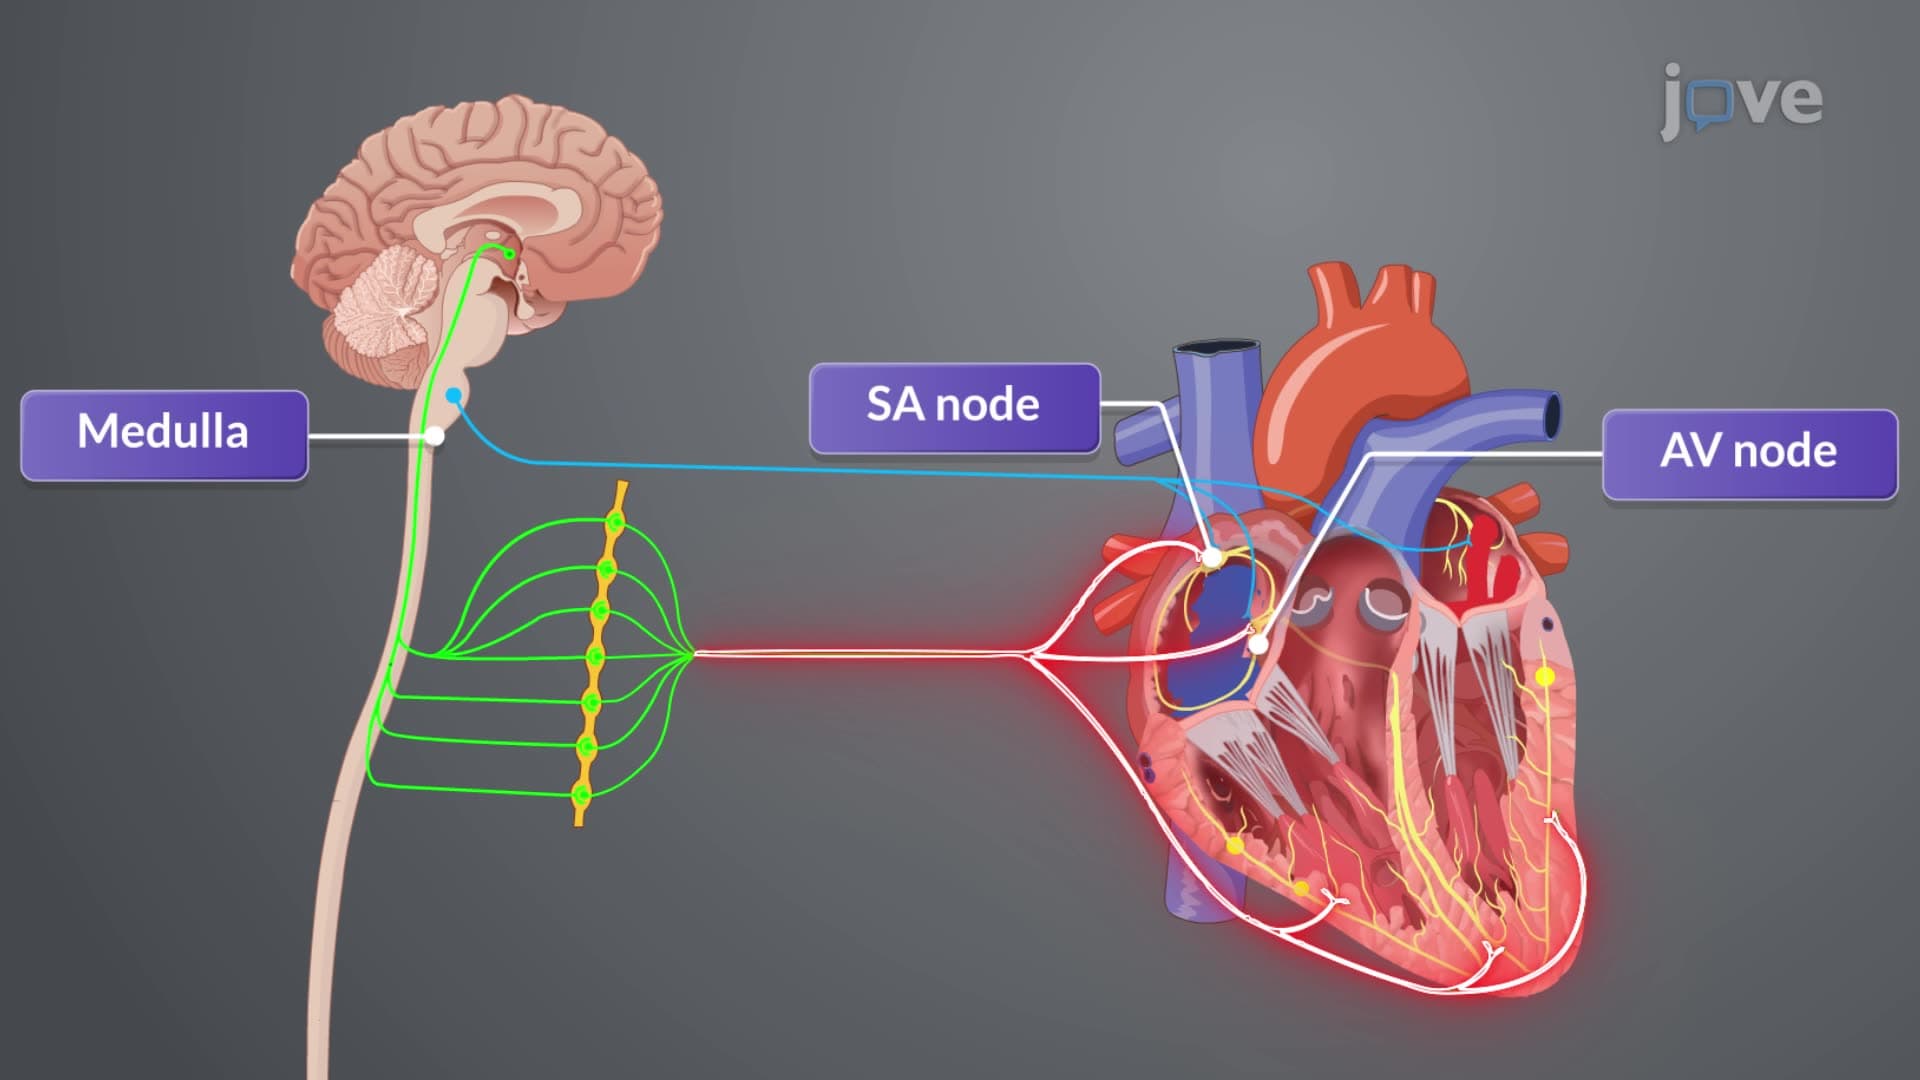
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...