Related Experiment Video
Updated: Feb 10, 2026
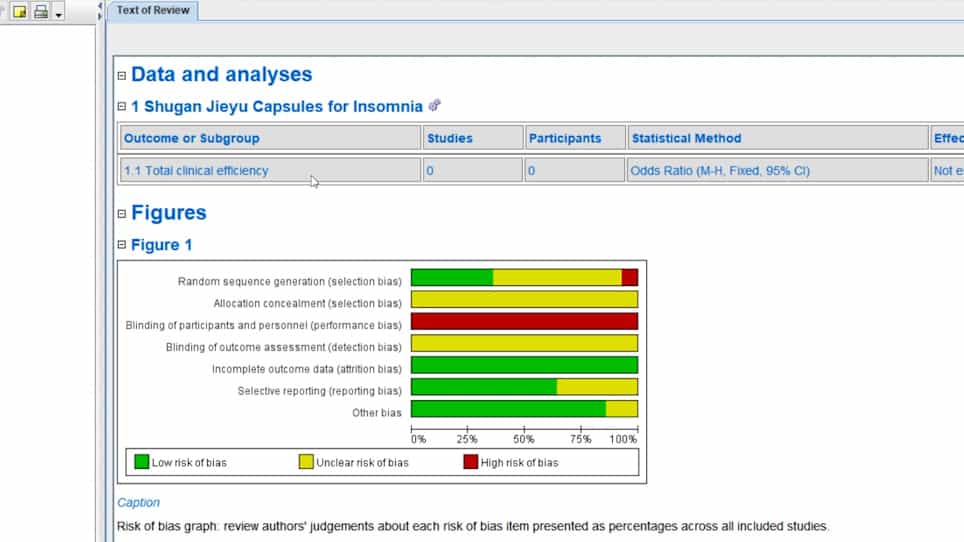
Meta-Analysis of the Effectiveness and Safety of Shugan Jieyu Capsules for the Treatment of Insomnia
Published on: February 17, 2023
A systematic review and meta-analysis of revascularization outcomes of infrainguinal chronic limb-threatening
Jehad Almasri1, Jayanth Adusumalli2, Noor Asi1
1Evidence-Based Practice Research Program, Mayo Clinic, Rochester, Minn; Robert D. and Patricia E. Kern Center for the Science of Health Care Delivery, Mayo Clinic, Rochester, Minn.

Insights
Optimal infrainguinal revascularization for chronic limb-threatening ischemia (CLTI) is unclear. Saphenous vein grafts offer the best patency, while prosthetic grafts show inferior outcomes, and endovascular treatments are comparable for focal disease.
Area of Science:
- Vascular Surgery
- Interventional Cardiology
- Regenerative Medicine
Background:
- The optimal revascularization strategy for infrainguinal chronic limb-threatening ischemia (CLTI) is debated due to limited comparative trials and reliance on low-quality evidence.
- Clinical decisions are often based on anecdotal evidence, highlighting the need for high-quality comparative studies.
Purpose of the Study:
- To systematically evaluate patient-relevant outcomes of different infrainguinal revascularization procedures for CLTI.
- To compare the effectiveness of various revascularization techniques, including bypass grafts and endovascular interventions.
Main Methods:
- A systematic literature search was conducted across multiple databases up to May 7, 2017.
- Prospective studies with at least 1-year follow-up evaluating infrainguinal revascularization in CLTI patients were included.
- Random-effects meta-analysis was employed to synthesize outcomes from 44 included studies enrolling 8602 patients.
Main Results:
- Periprocedural outcomes (mortality, amputation, MACE) were similar across modalities.
- Great saphenous vein grafts demonstrated superior patency rates (1-year: 87%, 2-year: 78%) compared to other interventions.
- Prosthetic bypasses showed inferior amputation and patency outcomes, especially for below-knee targets. Drug-eluting stents improved infrapopliteal artery patency over bare-metal stents.
- Survival and amputation-free survival at 2 years were similar between endovascular interventions and vein bypass, but prosthetic bypass had higher limb loss rates.
Conclusions:
- Current evidence for CLTI treatment decisions, especially for complex endovascular cases, has significant limitations.
- Saphenous vein bypass offers the highest patency, while prosthetic grafts are inferior for below-knee targets. Endovascular options like angioplasty and DES are comparable for focal infrapopliteal disease.
- Future research should integrate limb severity and anatomic staging to guide CLTI treatment decisions effectively.
Background:
The optimal strategy for revascularization in infrainguinal chronic limb-threatening ischemia (CLTI) remains debatable. Comparative trials are scarce, and daily decisions are often made using anecdotal or low-quality evidence.
Methods:
We searched multiple databases through May 7, 2017, for prospective studies with at least 1-year follow-up that evaluated patient-relevant outcomes of infrainguinal revascularization procedures in adults with CLTI. Independent pairs of reviewers selected articles and extracted data. Random-effects meta-analysis was used to pool outcomes across studies.
Results:
We included 44 studies that enrolled 8602 patients. Periprocedural outcomes (mortality, amputation, major adverse cardiac events) were similar across treatment modalities. Overall, patients with infrapopliteal disease had higher patency rates of great saphenous vein graft at 1 and 2 years (primary: 87%, 78%; secondary: 94%, 87%, respectively) compared with all other interventions. Prosthetic bypass outcomes were notably inferior to vein bypass in terms of amputation and patency outcomes, especially for below knee targets at 2 years and beyond. Drug-eluting stents demonstrated improved patency over bare-metal stents in infrapopliteal arteries (primary patency: 73% vs 50% at 1 year), and was at least comparable to balloon angioplasty (66% primary patency). Survival, major amputation, and amputation-free survival at 2 years were broadly similar between endovascular interventions and vein bypass, with prosthetic bypass having higher rates of limb loss. Overall, the included studies were at moderate to high risk of bias and the quality of evidence was low.
Conclusions:
There are major limitations in the current state of evidence guiding treatment decisions in CLTI, particularly for severe anatomic patterns of disease treated via endovascular means. Periprocedural (30-day) mortality, amputation, and major adverse cardiac events are broadly similar across modalities. Patency rates are highest for saphenous vein bypass, whereas both patency and limb salvage are markedly inferior for prosthetic grafting to below the knee targets. Among endovascular interventions, percutaneous transluminal angioplasty and drug-eluting stents appear comparable for focal infrapopliteal disease, although no studies included long segment tibial lesions. Heterogeneity in patient risk, severity of limb threat, and anatomy treated renders direct comparison of outcomes from the current literature challenging. Future studies should incorporate both limb severity and anatomic staging to best guide clinical decision making in CLTI.
Related Concept Videos
 01:10
Review and Preview
Percentiles are a type of fractile that partition data into...
 01:13
Review and Preview
 02:24
Predicting Reaction Outcomes
 01:20
Random and Systematic Errors
 01:09
Directing Effect of Substituents: meta-Directing Groups
 01:17
Systematic Sampling Method
Systematic sampling is one of the simplest methods...