Related Experiment Video
Updated: Feb 9, 2026
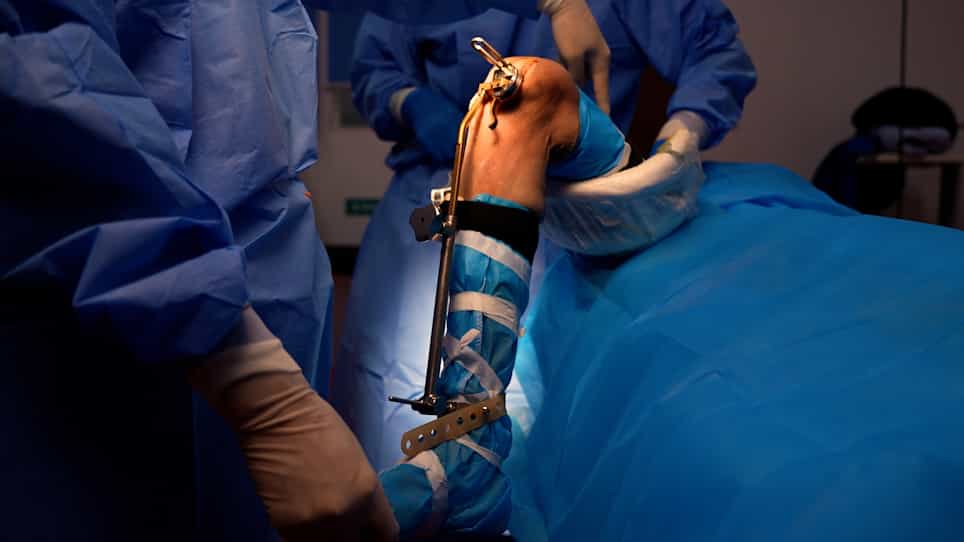

In Vitro Application of a Wireless Sensor in Flexion-Extension Gap Balance of Unicompartmental Knee Arthroplasty
Published on: May 5, 2023
Increased valgus laxity in flexion with greater tibial resection depth following total knee arthroplasty
E Sappey-Marinier1, N White1, R Gaillard2
1Centre Albert Trillat, Orthopaedic Surgery, Croix-Rousse Hospital, Lyon, France.

Purpose:
Soft tissue balancing is of central importance to outcome following total knee arthroplasty (TKA). However, there are lack of data analysing the effect of tibial bone cut thickness on valgus laxity. A cadaveric study was undertaken to assess the biomechanical consequences of tibial resection depth on through range knee joint valgus stability. We aimed to establish a maximum tibial resection depth, beyond which medial collateral ligament balancing becomes challenging, and a constrained implant should be considered.
Methods:
Eleven cadaveric specimens were included for analysis. The biomechanical effects of increasing tibial resection were studied, with bone cuts made at 6, 10, 14, 18 and 24 mm from the lateral tibial articular surface. A computer navigation system was used to perform the tibial resection and to measure the valgus laxity resulting from a torque of 10 Nm. Measurements were taken in four knee positions: 0° or extension, 30°, 60° and 90° of flexion. Intra-observer reliability was assessed. A minimum sample size of eight cadavers was necessary. Statistical analysis was performed using a nonparametric Spearman's ranking correlation matrix at the different stages: in extension, at 30°, 60° and 90° of knee flexion. Significance was set at p < 0.05.
Results:
There was no macroscopic injury to the dMCL or sMCL in any of the specimens during tibial resection. There was no significant correlation found between the degree of valgus laxity and the thickness of the tibial cut with the knee in extension. There was a statistically significant correlation between valgus laxity and the thickness of the tibial cut in all other knee flexion positions: 30° (p < 0.0001), 60° (p < 0.001) and 90° (p < 0.0001). We identified greater than 5° of valgus laxity, at 90° of knee flexion, after a tibial resection of 14 mm.
Conclusion:
Increased tibial resection depth is associated with significantly greater valgus laxity when tested in positions from 30° to 90° of flexion, despite stability in extension. Greater than 5° of laxity was identified with a tibial resection of 14 mm. When a tibial bone cut of 14 mm or greater is necessary, as may occur with severe preoperative coronal plane deformity, it is recommended to consider the use of a constrained knee prosthesis.
Related Concept Videos
 01:23
Knee Joint
A total of seven ligaments support the knee joint. The patellar ligament, which is also attached to the quadriceps femoris...
 01:18
Increasing Function
 01:27
Uniform Depth Channel Flow
 01:15
Depth Perception and Spatial Vision
 01:25
Increased Body Temperature
 01:17
Increased pulse rate
Many factors can elevate the risk of developing tachycardia. These include advanced age, a family history of arrhythmias, and an...