Clinical and economic impact of compression in the acute phase of deep vein thrombosis
Related Experiment Video
Updated: Feb 9, 2026
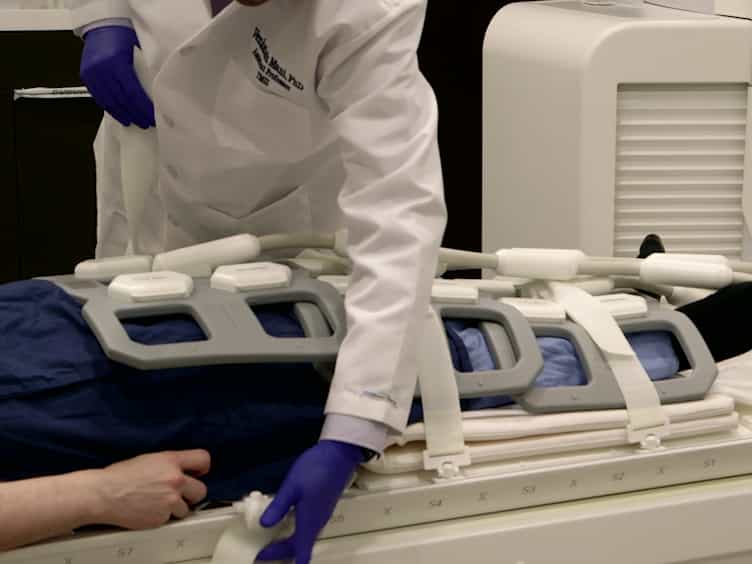
A Multicenter MRI Protocol for the Evaluation and Quantification of Deep Vein Thrombosis
Published on: June 2, 2015
E E Amin1,2,3, M A Joore2, H Ten Cate1,3
1Department of Biochemistry, Cardiovascular Research Institute Maastricht, Maastricht University, Maastricht, the Netherlands.

Essentials The value of compression therapy in acute phase of deep vein thrombosis is still unclear. Patients with deep vein thrombosis received acute compression hosiery, bandaging, or none. Acute compression reduces irreversible skin signs related to post thrombotic syndrome. Compression hosiery may be the preferred choice for the acute phase SUMMARY: Background The effectiveness of compression therapy in the acute phase of deep vein thrombosis (DVT) is not yet determined. Objectives To investigate the impact of compression therapy in the acute phase of DVT on determinants of the Villalta score, health-related quality of life (HRQOL), and costs. Patients/Methods Eight hundred and sixty-five patients with proximal DVT (substudy of the IDEAL DVT study) received, immediately after DVT diagnosis, either no compression, multilayer bandaging, or hosiery. In the acute phase and 3 months after diagnosis, HRQOL was determined by use of the EQ-5D, SF6D, and VEINES-QoL intrinsic method (VEINES-QoLint ). At 3 months, signs and symptoms were assessed for the total and separate items of the Villalta score, and healthcare costs were calculated. Results The compression groups had lower overall objective Villalta scores than the no-compression group (1.47 [standard deviation (SD) 1.570] and 1.59 [SD 1.64] versus 2.21 [SD 2.15]). The differences were mainly attributable to irreversible skin signs (induration, hyperpigmentation, and venectasia) and pain on calf compression. Subjective and total Villalta scores were similar across groups. Differences in HRQOL were only observed at 1 month; HRQOL was better for hosiery (EQ-5D 0.86 [SD 0.18]; VEINES-QoLint 0.66 [SD 0.18]) than for multilayer compression bandaging (EQ-5D 0.81 [SD 0.23; VEINES-QoLint 0.62 [SD 0.19]). Mean healthcare costs per patient were €417.08 (€354.10 to €489.30) for bandaging, €114.25 (€92.50 to €198.43) for hosiery, and €105.86 (€34.63 to €199.30) for no compression. Conclusions Initial compression reduces irreversible skin signs, edema, and pain on calf compression. Multilayer bandaging is slightly more effective than hosiery, but has substantially higher costs, without a gain in HRQOL. From a patient and economic perspective, compression hosiery would be preferred when initial compression is applied.
Essentials The value of compression therapy in acute phase of deep vein thrombosis is still unclear. Patients with deep vein thrombosis received acute compression hosiery, bandaging, or none. Acute compression reduces irreversible skin signs related to post thrombotic syndrome. Compression hosiery may be the preferred choice for the acute phase SUMMARY: Background The effectiveness of compression therapy in the acute phase of deep vein thrombosis (DVT) is not yet determined. Objectives To investigate the impact of compression therapy in the acute phase of DVT on determinants of the Villalta score, health-related quality of life (HRQOL), and costs. Patients/Methods Eight hundred and sixty-five patients with proximal DVT (substudy of the IDEAL DVT study) received, immediately after DVT diagnosis, either no compression, multilayer bandaging, or hosiery. In the acute phase and 3 months after diagnosis, HRQOL was determined by use of the EQ-5D, SF6D, and VEINES-QoL intrinsic method (VEINES-QoLint ). At 3 months, signs and symptoms were assessed for the total and separate items of the Villalta score, and healthcare costs were calculated. Results The compression groups had lower overall objective Villalta scores than the no-compression group (1.47 [standard deviation (SD) 1.570] and 1.59 [SD 1.64] versus 2.21 [SD 2.15]). The differences were mainly attributable to irreversible skin signs (induration, hyperpigmentation, and venectasia) and pain on calf compression. Subjective and total Villalta scores were similar across groups. Differences in HRQOL were only observed at 1 month; HRQOL was better for hosiery (EQ-5D 0.86 [SD 0.18]; VEINES-QoLint 0.66 [SD 0.18]) than for multilayer compression bandaging (EQ-5D 0.81 [SD 0.23; VEINES-QoLint 0.62 [SD 0.19]). Mean healthcare costs per patient were €417.08 (€354.10 to €489.30) for bandaging, €114.25 (€92.50 to €198.43) for hosiery, and €105.86 (€34.63 to €199.30) for no compression. Conclusions Initial compression reduces irreversible skin signs, edema, and pain on calf compression. Multilayer bandaging is slightly more effective than hosiery, but has substantially higher costs, without a gain in HRQOL. From a patient and economic perspective, compression hosiery would be preferred when initial compression is applied.
Trial Registration:
IDEAL DVT study ClinicalTrials.gov number, NCT01429714.

Related Concept Videos
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:30
Venous Thrombosis I: Introduction
 01:19
Impact of Groups on Groups