Related Experiment Video
Updated: Feb 9, 2026
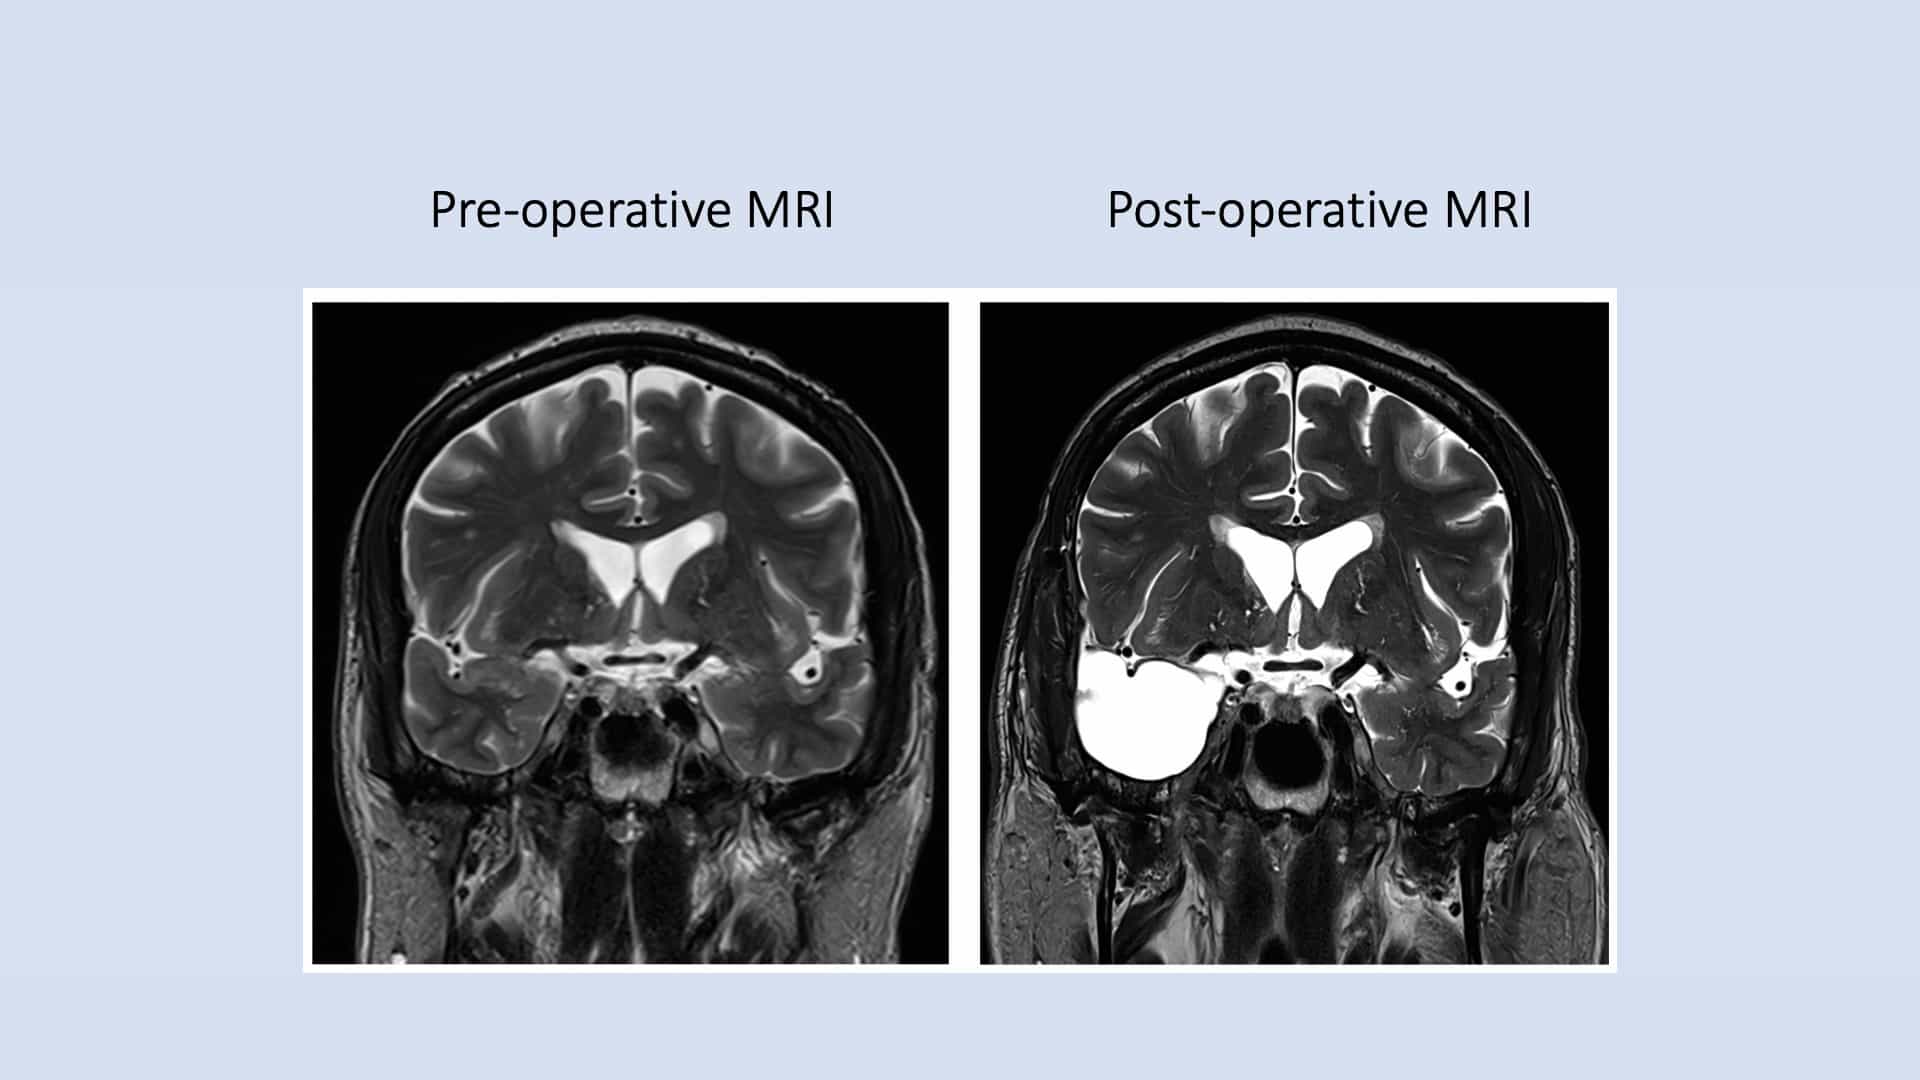

Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Readmission Following Surgical Resection for Intractable Epilepsy: Nationwide Rates, Causes, Predictors, and Outcomes
Kavelin Rumalla1, Kyle A Smith2, Paul M Arnold2
1School of Medicine, University of Missouri-Kansas City, Kansas City, Missouri.

Background:
Hospital readmissions can be detrimental to patients and may interfere with the potential benefits of the therapeutic procedure. Government agencies have begun to focus on reducing readmissions; however, the etiology of readmissions is lacking.
Objective:
To report the national rates, risk factors, and outcomes associated with 30- and 90-d readmissions following surgery for intractable epilepsy.
Methods:
We queried the Nationwide Readmissions Database from January to September 2013 using International Classification of Diseases, Ninth Edition, Clinical Modification codes to identify all patients with intractable epilepsy, who underwent hemispherectomy (01.52), brain lobectomy (01.53), amydalohippocampectomy, or partial lobectomy (01.59). Predictor variables included epilepsy type, presurgical diagnostic testing, surgery type, medical complications, surgical complications, and discharge disposition.
Results:
In 1587 patients, the 30- and 90-d readmission rates were 11.5% and 16.8%, respectively. The most common reasons for readmission were persistent epilepsy, video electroencephalography monitoring, postoperative infection, and postoperative central nervous system complication. In multivariable analysis, risk factors associated with both 30- and 90-d readmission were Medicare payer status, lowest quartile of median income, depression, hemispherectomy, and postoperative complications (P < .05). The only unique predictor of 30-d readmission was small bedsize hospital (P = .001). Readmissions within 30 d were associated with longer length of stay (6.8 vs 5.8 d), greater costs ($18 660 vs $15 515), and increased adverse discharges (26.4% vs 21.8%).
Conclusion:
Following epilepsy surgery, most readmissions that occurred within 30 d can be attributed to management of persistent epilepsy and predicted by Medicare payer status, depression, and complications. These data can assist the clinician in preventing readmissions and assist policy makers determine which admissions are potentially avoidable.
More Related Videos
Related Concept Videos
 02:24
Predicting Reaction Outcomes
 01:13
Outcomes of Glycolysis
Cellular respiration can occur aerobically (with oxygen) or anaerobically (without oxygen). In the presence of oxygen, cellular respiration starts with glycolysis and continues with pyruvate...
 02:53
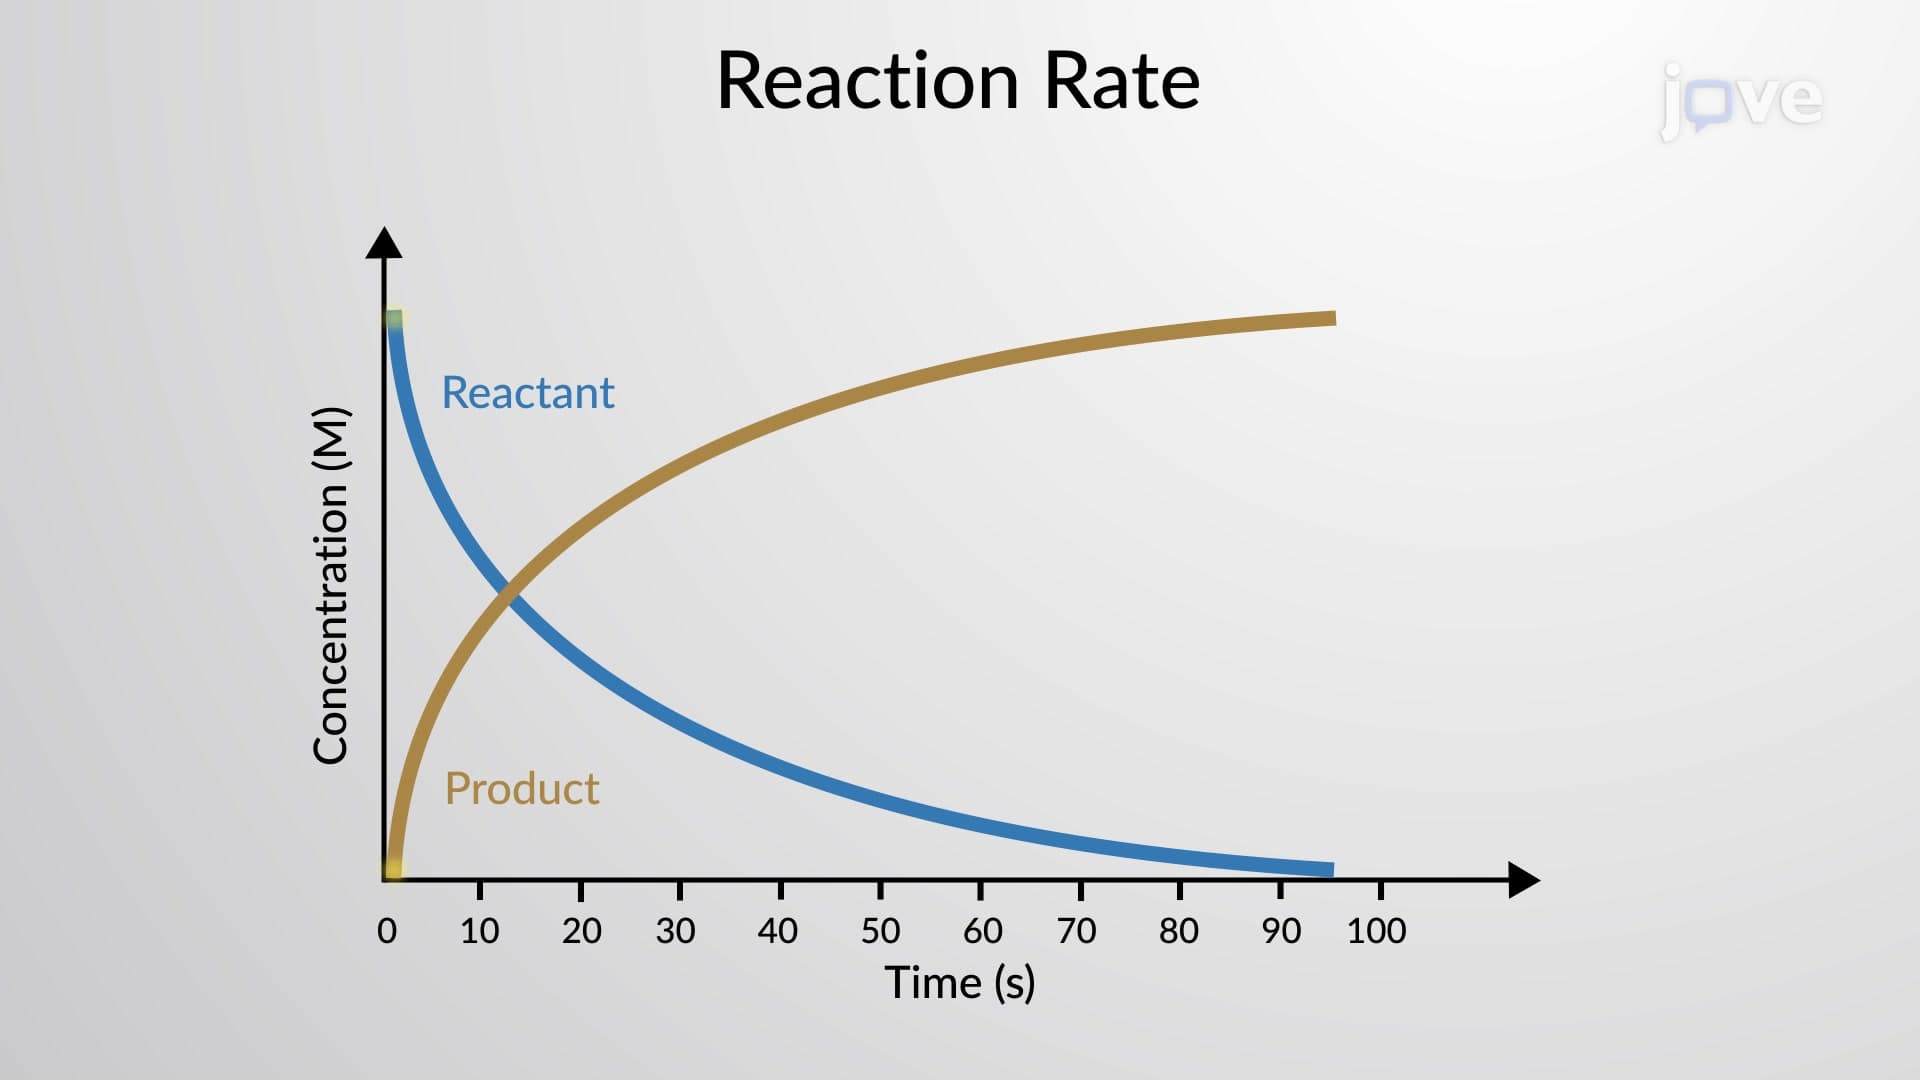
Reaction Rate
The mathematical representation of the change in the concentration of reactants and products, over time, is the rate...
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:11
Guidelines for Writing Outcome
Patient outcomes reflect the patient's response to the goal rather than what the nurse aims to achieve. Terminology should be observable and measurable to avoid the reader's interpretation. The desired outcome should be realistic and achievable in the designated care timeframe. Expected outcomes should align with adjunctive therapies. The outcome should enhance care...
 01:18
Related Rates