Related Experiment Video
Updated: Feb 9, 2026
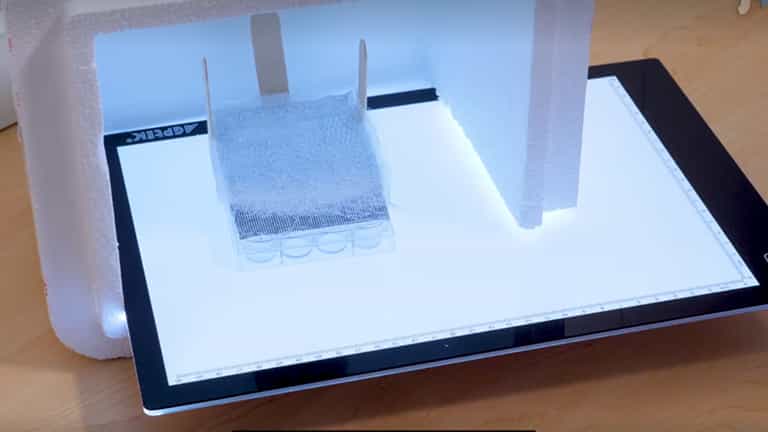

High-Throughput Method for Measuring Alcohol Sedation Time of Individual Drosophila melanogaster
Published on: April 20, 2020
Sedation strategies for defibrillation threshold testing: safety outcomes with anaesthesiologist compared to
Roopinder K Sandhu1, Kenneth K Quadros1, Yan Yun Liu2
1Mazankowski Alberta Heart Institute, University of Alberta, 8440-112 Street, 2C2 WMC Edmonton, AB, Canada.

Aims:
No standard practice exists with respect to anaesthesiologist-directed sedation (ADS) vs. sedation by proceduralist (PDS) for defibrillation threshold (DT) testing. We aimed to evaluate adverse events and safety outcomes with ADS vs. PDS for DT testing.
Methods And Results:
A post hoc analysis of the Shockless Implant Evaluation (SIMPLE) study was performed among the 1242 patients who had DT testing (624 ADS and 618 PDS). We evaluated both intraoperative and in-hospital adverse composite events and two safety composite outcomes at 30-days of the main trial. Propensity score adjusted models were used to compute odds ratio (OR) and 95% confidence interval (CI) to evaluate the association between adverse and safety outcomes with method of sedation and independent predictors for use of ADS. Compared to PDS, patients who received ADS were younger (62 ± 12 years vs. 64 ± 12 years, P = 0.01), had lower ejection fraction (left ventricular ejection fraction 0.31 ± 13 vs. 0.33 ± 13, P = 0.03), were more likely to receive inhalational anaesthesia, propofol, or narcotics (P < 0.001, respectively) and receive an arterial line (43% vs. 8%, P = <0.0001). Independent predictors for ADS sedation were presence of coronary artery disease (OR 1.69, 95% CI 1.0-2.72; P = 0.03) and hypertrophic cardiomyopathy (OR 2.64, 95% CI 1.19-5.85; P = 0.02). Anaesthesiologist directed sedation had higher intraoperative adverse events (2.2% vs. 0.5%; OR 4.47, 95% CI 1.25-16.0; P = 0.02) and higher primary safety outcomes at 30 days (8.2% vs. 4.9%; OR 1.72 95% CI 1.06-2.80; P = 0.03) and no difference in other outcomes compared to PDS.
Conclusion:
Proceduralist-directed sedation is safe, however, this could be result of selection bias. Further research is needed.

Related Concept Videos
 01:23
Sedatives and Hypnotics: Overview
Sedative-hypnotics are categorized into barbiturates, benzodiazepines (BZDs), and non-benzodiazepines or Z-drugs. These drugs work by suppressing central nervous system activity, and this suppression is dose-dependent. Older sedative medications, like barbiturates, follow a linear curve in...
 01:20
Sedatives and Hypnotics Drugs: Barbiturates
 01:19
Sedatives and Hypnotics Drugs: Benzodiazepines
Benzodiazepines work by enhancing the effects of the inhibitory neurotransmitter GABA. They bind to the GABAA receptor, increasing its affinity for GABA, which opens chloride...
 01:17
Sedatives and Hypnotics Drugs: Miscellaneous Agents
Melatonin congeners like ramelteon (Rozerem) and tasimelteon (Hetlioz) selectively bind to melatonin receptors (MT1 and MT2) and thus mimic the actions of melatonin, a hormone that regulates sleep-wake cycles. Tasimelteon is primarily used for non-24-hour sleep-wake disorder, common in blind patients. They are also used to treat conditions like insomnia...
 01:20
Comparing the Survival Analysis of Two or More Groups
 01:28
Survey Safety