Related Experiment Video
Updated: Feb 9, 2026

Author Spotlight: Scope of LE-ULBD as a Safe, Effective, and Minimally Invasive Approach to Treat Lumbar Spinal Stenosis
Published on: February 9, 2024
Influence of Skeletal Muscle Mass and Spinal Alignment on Surgical Outcomes for Lumbar Spinal Stenosis
Yawara Eguchi1, Munetaka Suzuki1, Hajime Yamanaka1
1Department of Orthopaedic Surgery, Shimoshizu National Hospital, Yotsukaido, Japan.

Study Design:
Retrospective observational study.
Purpose:
We considered the relationship between spinal alignment and skeletal muscle mass on clinical outcomes following a surgery for lumbar spinal stenosis (LSS).
Overview Of Literature:
There are no reports of preoperative factors predicting residual low back pain following surgery for LSS.
Methods:
Our target population included 34 women (mean age, 74.4 years) who underwent surgery for LSS. Prior to and 6 months after the surgery, systemic bone mineral density and lean soft tissue mass were measured using dual-energy X-ray absorptiometry. Skeletal muscle mass index (SMI) was calculated as the sum of the arm and leg lean mass in kilograms divided by height in meters squared. The spinal alignment was also measured. Clinical outcomes were evaluated using the Japanese Orthopedic Association scoring system, leg and low back pain Visual Analog Scale, and Roland-Morris Disability Questionnaire (RDQ). Additionally, we examined the bone mineral density, skeletal muscle mass, and spinal alignment before and after the surgery. We used the Spearman correlation coefficient to examine the associations among clinical outcomes, preoperative muscle mass, and spinal alignment.
Results:
Sarcopenia (SMI <5.46) was observed in nine subjects (26.5%). Compared with normal subjects (SMI >6.12), RDQ was significantly higher in subjects with sarcopenia (p =0.04). RDQ was significantly negatively correlated with SMI (r =-0.42, p <0.05). There was a significant positive correlation between postoperative RDQ and pelvic tilt (PT; r =0.41, p <0.05). SMI and PT were significantly negatively correlated (r =-0.39, r <0.05).
Conclusions:
Good postoperative outcomes were negatively correlated with low preoperative appendicular muscle mass, suggesting that postoperative outcomes were inferior in cases of decreased appendicular muscle mass (sarcopenia). Posterior PT due to decreased limb muscle mass may contribute to postoperative back pain, showing that preoperatively reduced limb muscle mass and posterior PT are predictive factors in the persistence of postoperative low back pain.

Related Concept Videos
 01:48
Classification of Skeletal Muscle Fibers
Slow-Twitch Muscle Fibers
Slow oxidative, muscle fibers appear red due to large numbers of capillaries and high levels of...
 01:26
Spinal Cord
 01:54
The Spinal Cord
 01:10
Spinal Cord: Information Processing
Sensory Information Processing
Sensory information processing begins at the sensory receptors located in the skin and other tissues, which detect somatic sensory stimuli such as touch, temperature, or pain. These receptors function as catalysts, initiating...
 01:21
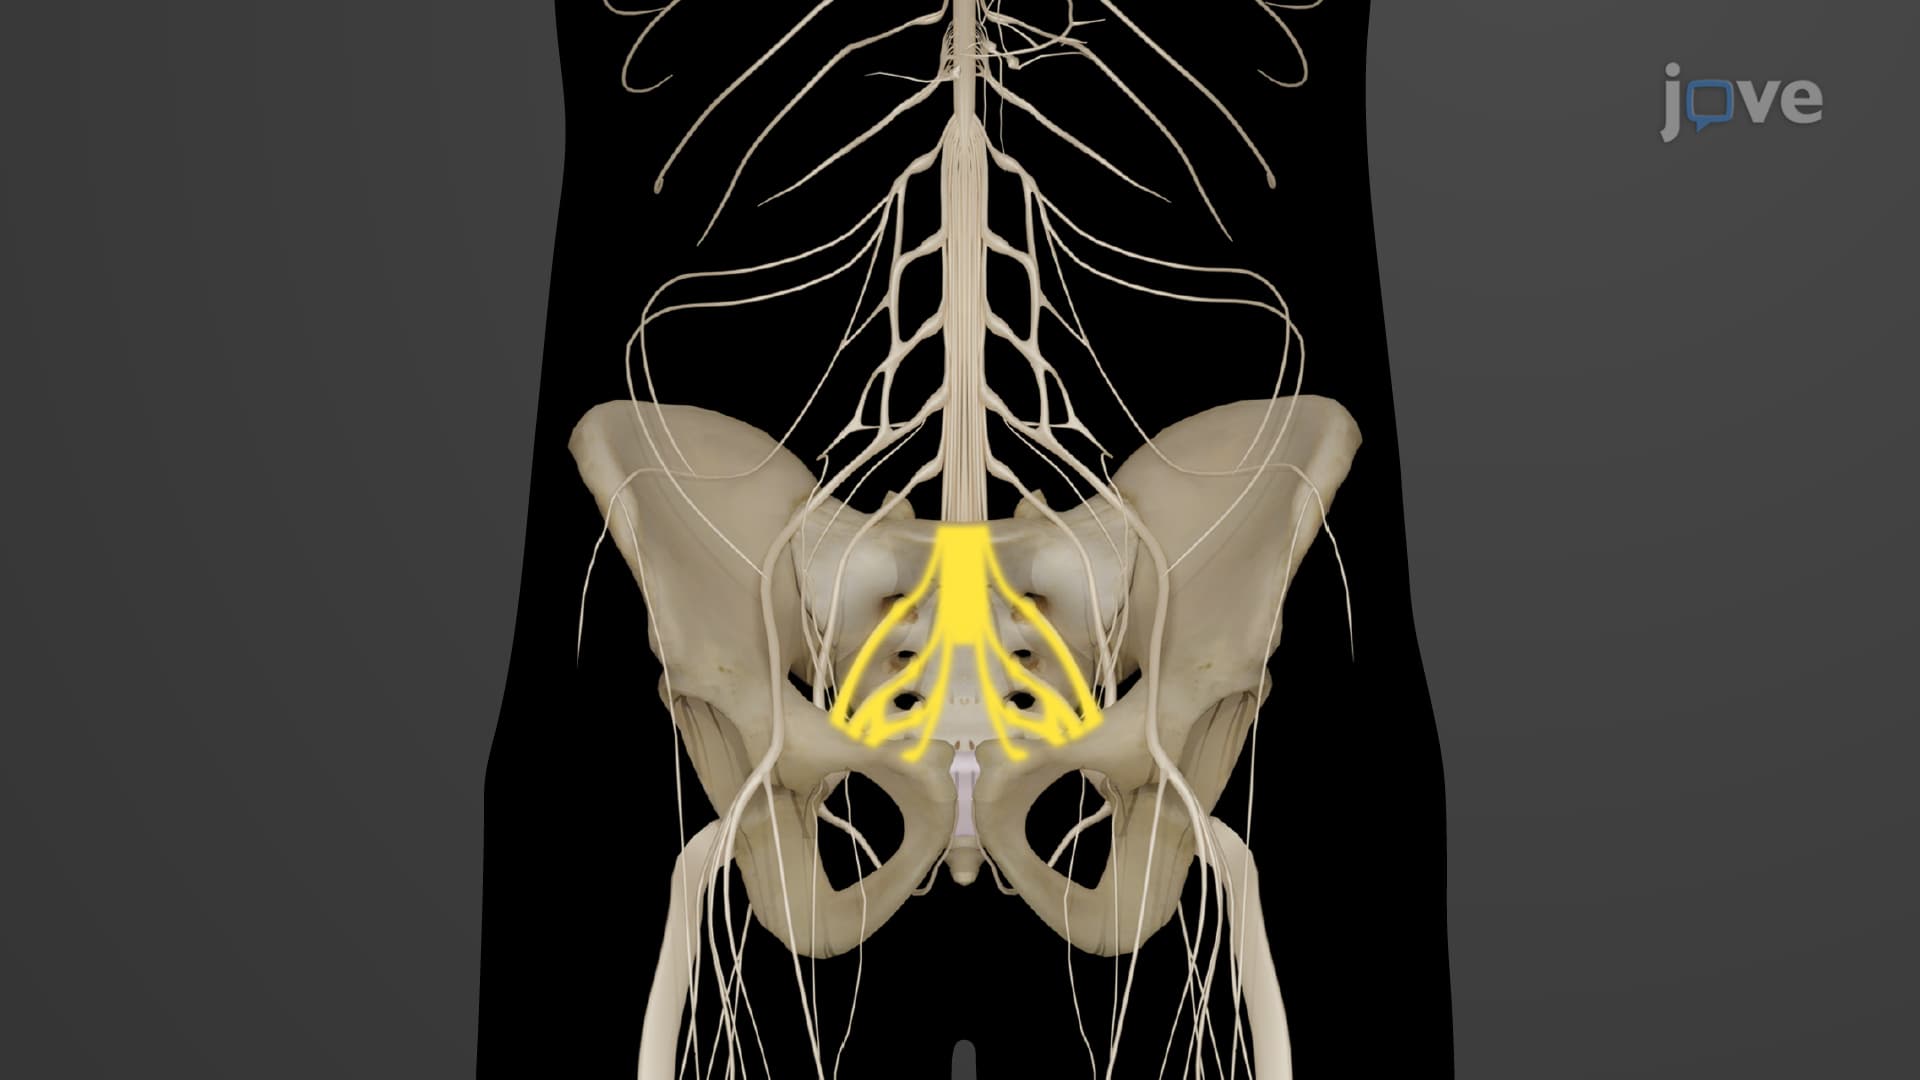
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
 01:19
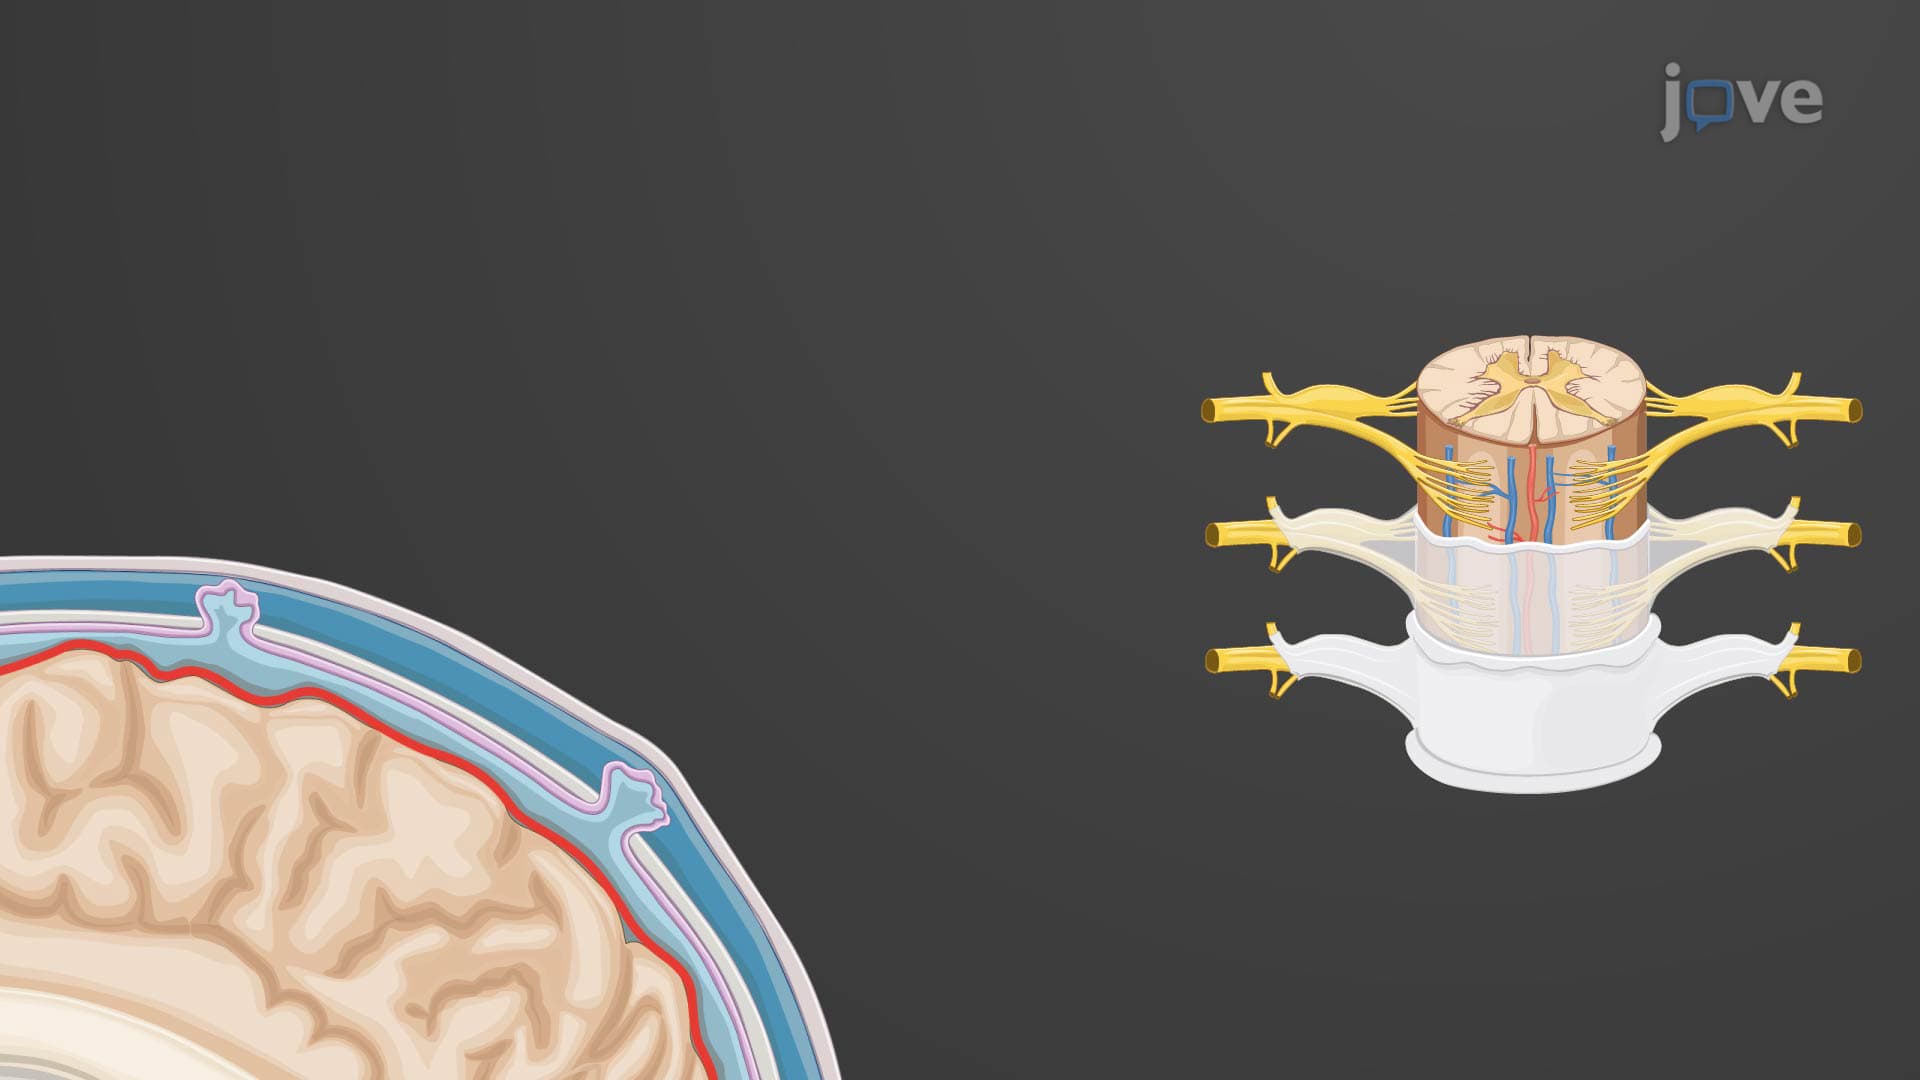
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...