Related Experiment Video
Updated: Feb 9, 2026
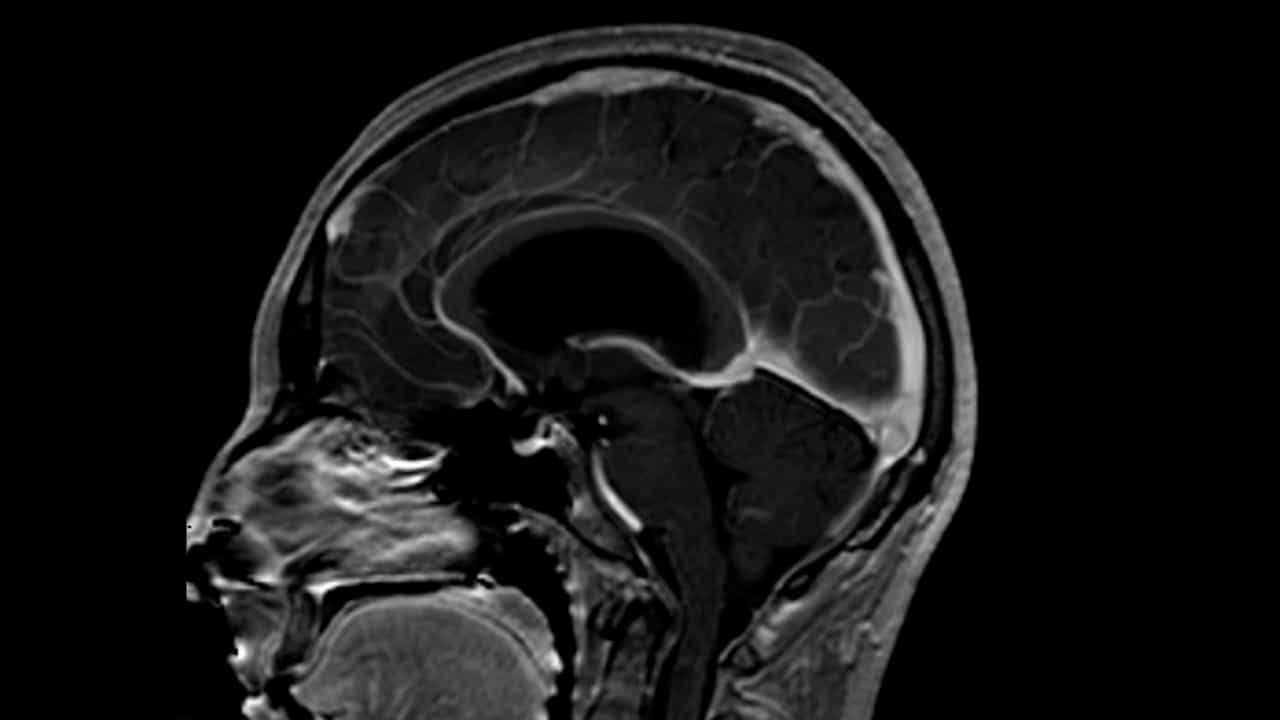

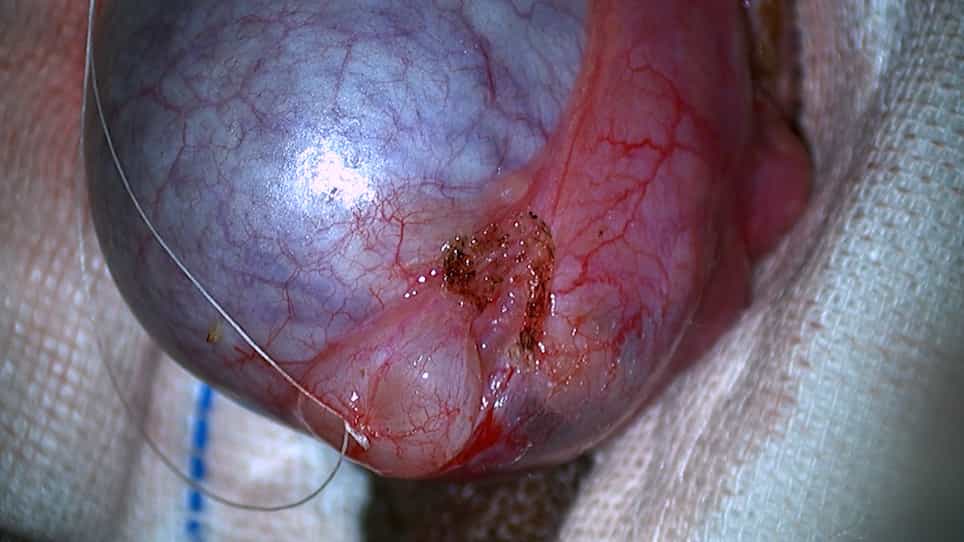
Endoscopic Approach for Colloid Cyst Resection
Published on: May 23, 2025
Endoscopic endonasal resection of epidermoid cysts involving the ventral cranial base
Jonathan A Forbes1, Matei Banu2, Kurt Lehner3
11Department of Neurological Surgery, Weill Cornell Medical College, NewYork-Presbyterian Hospital, New York, New York.

Objective:
Epidermoid cysts (ECs) commonly extend to involve the ventral cisterns of the cranial base. When present, symptoms arise due to progressive mass effect on the brainstem and adjacent cranial nerves. Historically, a variety of open microsurgical approaches have been used for resection of ECs in this intricate region. In recent years, the endoscopic endonasal approach (EEA) has been proposed as an alternative corridor that avoids crossing the plane of the cranial nerves. To date, there is a paucity of data in the literature regarding the safety and efficacy of the EEA in the treatment of ECs of the ventral cranial base.
Methods:
The authors reviewed a prospectively acquired database of EEAs for resection of ECs over 8 years at Weill Cornell, NewYork-Presbyterian Hospital. All procedures were performed by the senior authors. Standardized clinical and radiological parameters were assessed before and after surgery. Statistical tests were used to determine the impact of previous surgery and tumor volume on extent of resection and recurrence as well as the method of closure on rate of CSF leak.
Results:
Between January 2009 and February 2017, 7 patients (4 males and 3 females; age range 16-70 years) underwent a total of 8 surgeries for EC resection utilizing the EEA. Transplanum and transclival extensions were performed in 3 and 5 patients, respectively. Methods of closure incorporated a gasket seal in 6 of 8 procedures and a nasoseptal flap in 7 of 8 procedures. Gross-total resection (GTR) was achieved in 43% of patients, and near-total resection (> 95%) was obtained in another 43%. Complications included diabetes insipidus (n = 2), postoperative CSF leak (n = 2), transient third cranial nerve palsy (n = 1), and epistaxis (n = 1). With a mean follow-up of 43.5 months, recurrence has been observed in 2 of 7 patients. In 1 case, reoperation for recurrence was required 71 months following the initial surgery. Use of the gasket-seal technique with nasoseptal flap coverage significantly correlated with the absence of postoperative CSF leakage (p = 0.018). GTR was achieved in 25% of the patients who had prior surgeries and in 50% of patients without previous resections. The mean volume of cysts in which GTR was achieved (4.3 ± 1.8 cm3) was smaller than that in which subtotal or near-total resection was achieved (12.2 ± 11 cm3, p = 0.134).
Conclusions:
The EEA for resection of ECs of the ventral cranial base is a safe and effective operative strategy that avoids crossing the plane of the cranial nerves. In the authors' experience, gasket-seal closure with nasoseptal flap coverage has been associated with a decreased risk of postoperative CSF leakage.

Related Concept Videos
 01:19
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:14
Cranial Nerves: Types Part I
Olfactory Nerve (Cranial Nerve I)
The olfactory nerve, or cranial nerve I, is unique as it is purely sensory and dedicated to the sense of smell. This nerve originates in the olfactory epithelium of the...
 01:22
Cranial Nerves: Types Part II
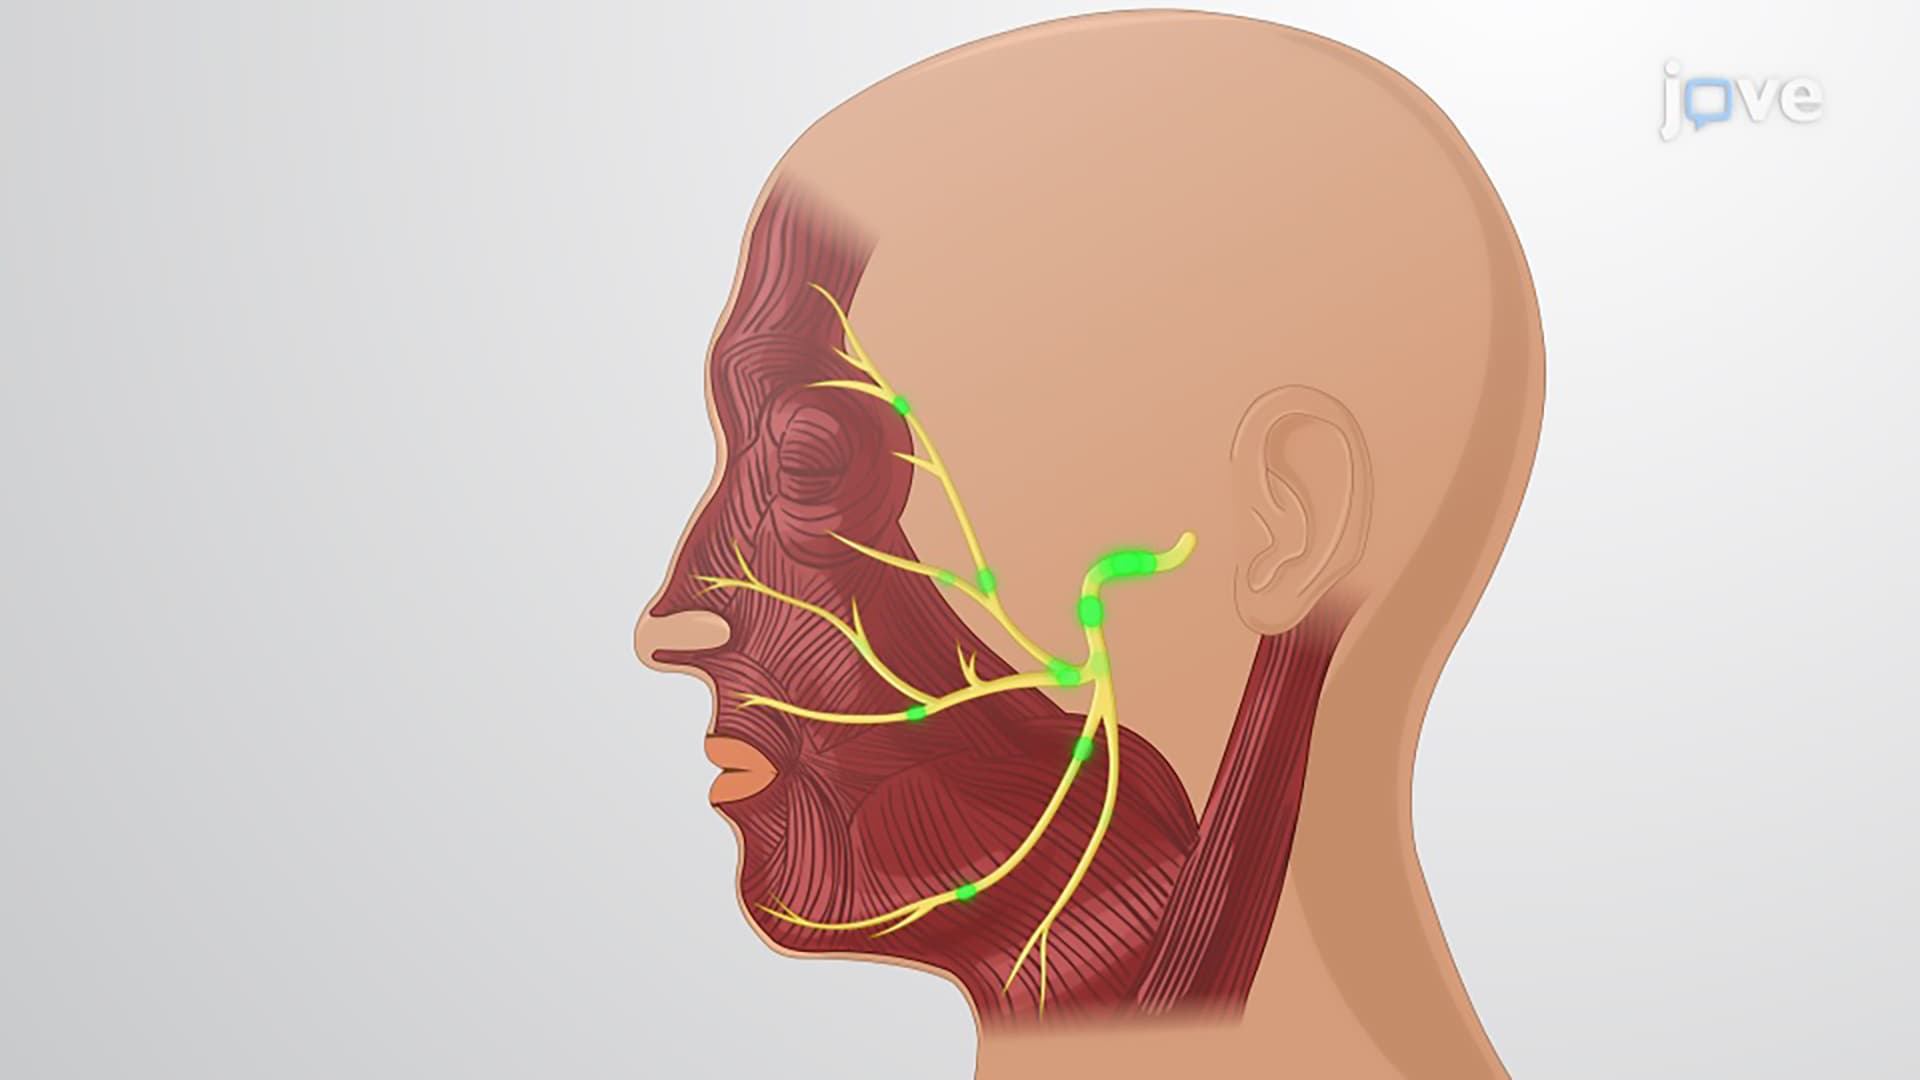
Facial Nerve (Cranial Nerve VII)
Cranial nerve VII, or the facial nerve,...
 01:18
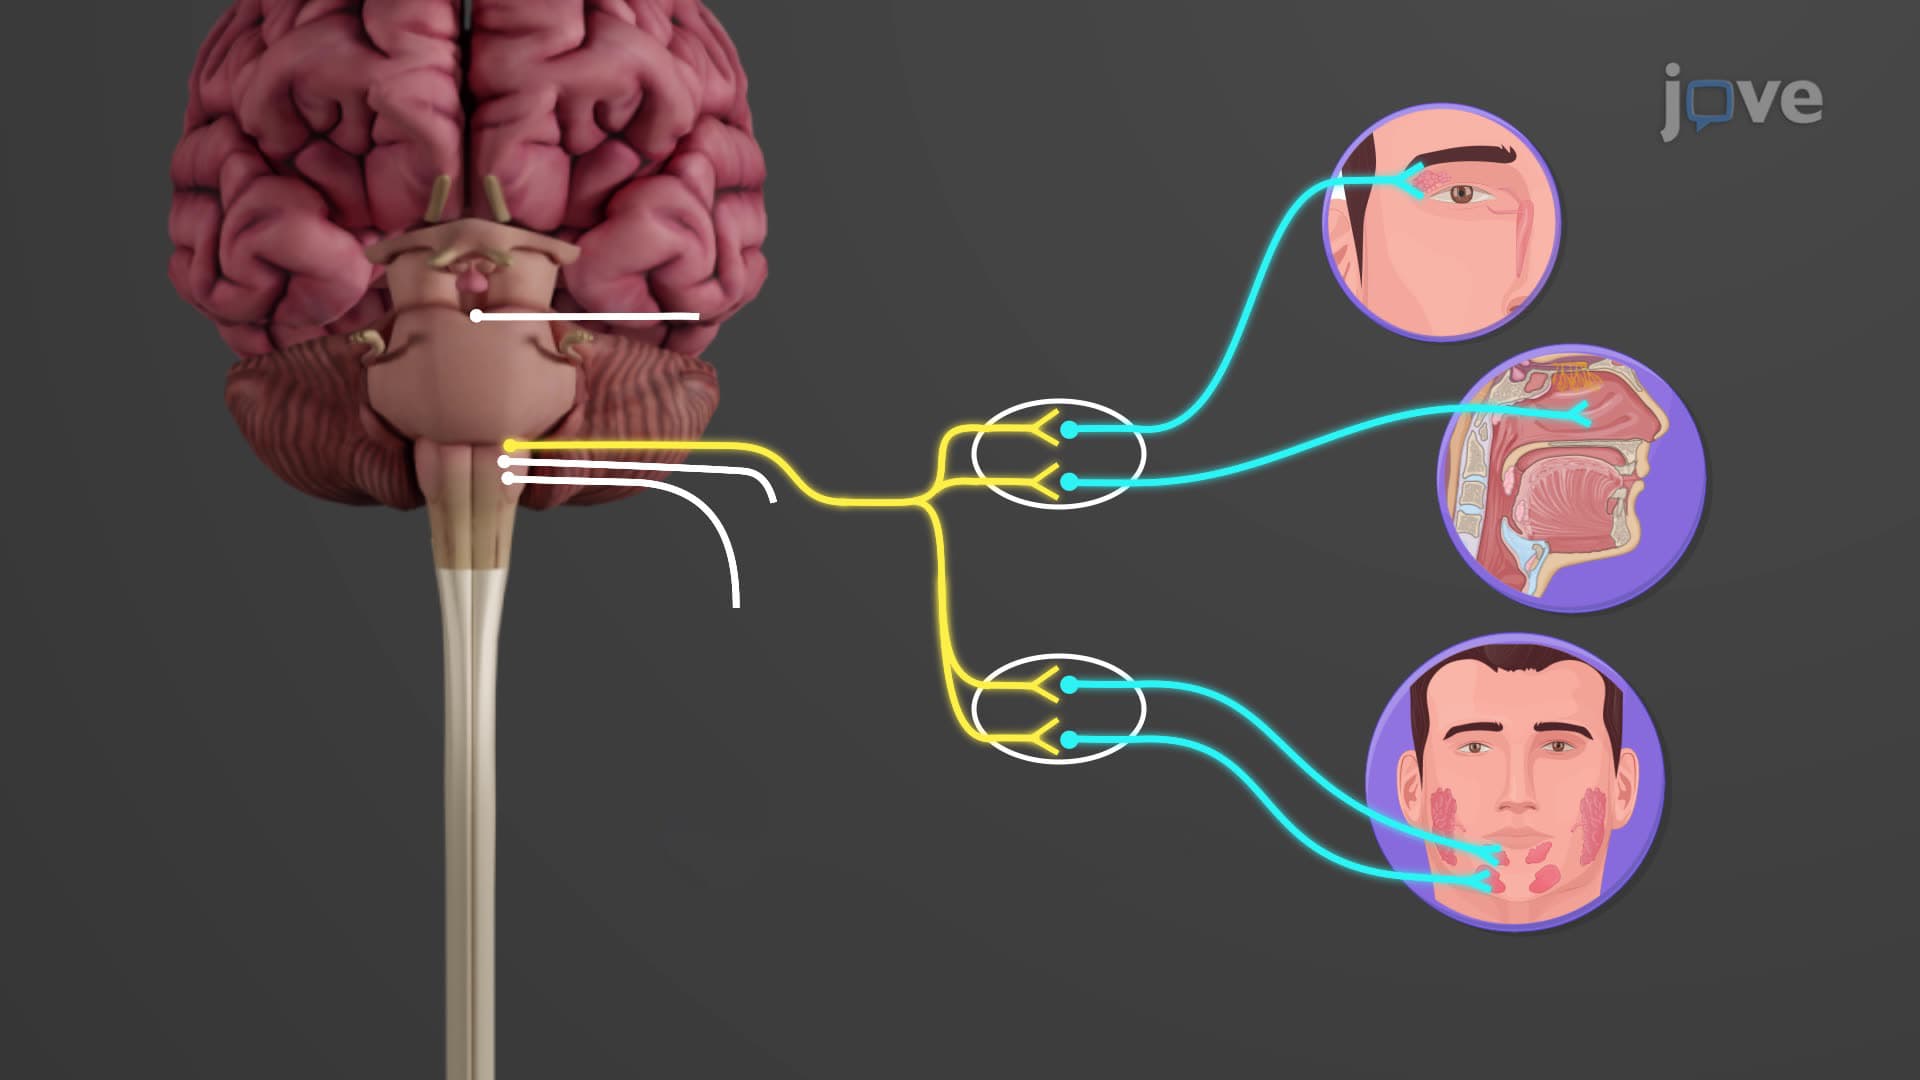
Cranial Part of Parasympathetic Division
The vagus nerve (cranial nerve X) alone accounts for approximately 75...
 01:26
Antigens Involved in Adaptive Immunity
Complete Antigens
Complete antigens possess both immunogenicity and...
 01:19
Cranial Nerves: Overview and Anatomy