Related Experiment Video
Updated: Feb 9, 2026
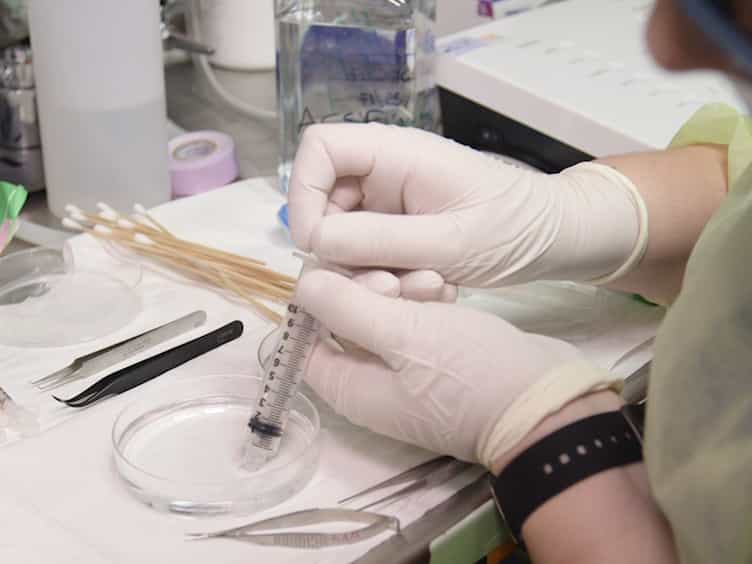

Piezo High Accuracy Surgical Osteal Removal PHASOR: A Technique for Improved Cranial Window Surgery in Mice
Published on: March 2, 2018
Improving the Power of the American Society of Anesthesiology Classification System to Risk Stratify Vascular Surgery
Alexander I Kraev1, Joseph McGinn1, Yana Etkin1
1Division of Vascular and Endovascular Surgery, Northwell Health System, New Hyde Park, NY.

Background:
Recently published reports have shown that the American Society of Anesthesiology (ASA) classification system has limited applicability in vascular surgery patients. Most patients undergoing vascular procedures are designated as ASA class III, limiting discrimination in preoperative risk assessment. The 2006 National Surgical Quality Improvement Project (NSQIP), containing over 170,000 surgical cases, demonstrated that functional status is an important predictor of mortality. We propose that dividing ASA class III into 2 subgroups, based on NSQIP-defined functional status, improves the predictive value of the ASA scheme.
Methods:
The 2006 NSQIP database was queried for ASA class III patients undergoing vascular surgery procedures. Patients were divided into groups IIIA and IIIB based on independent or dependent (partial or complete) functional status, respectively. Difference in 30-day survival between subgroups was evaluated using Kaplan-Meier and logistic regression analyses. Differences in postoperative morbidity and length of stay were compared using the unpaired t-test.
Results:
ASA class III patients having undergone vascular surgery procedures numbered 11,555 (68%). Of those 9,913 (85.7%) patients were independent (IIIA), and 1,642 (14.3%) were dependent (IIIB). Mean 30-day mortality was 1.3% in subgroup IIIA, and 6.5% in IIIB (logrank P < 0.001, χ2, 137.8). Mean lengths of stay between subgroups IIIA and IIIB were 5.4 and 13.2 days (P < 0.001). The risk of NSQIP-defined postoperative complications was 0.16 in IIIA and 0.32 in IIIB (P < 0.001).
Conclusions:
A 5-fold difference in mortality was observed between patients who were functionally independent and dependent. A significant increase in length of stay and incidence of postoperative complications was also observed in subgroup IIIB. Subdividing ASA class III vascular surgery patients markedly improves the value of the ASA classification system. Given the "high-risk" nature of patients with vascular disease, the addition of functional status to the preoperative assessment will assist in predicting outcomes in this patient population.
More Related Videos


Related Concept Videos
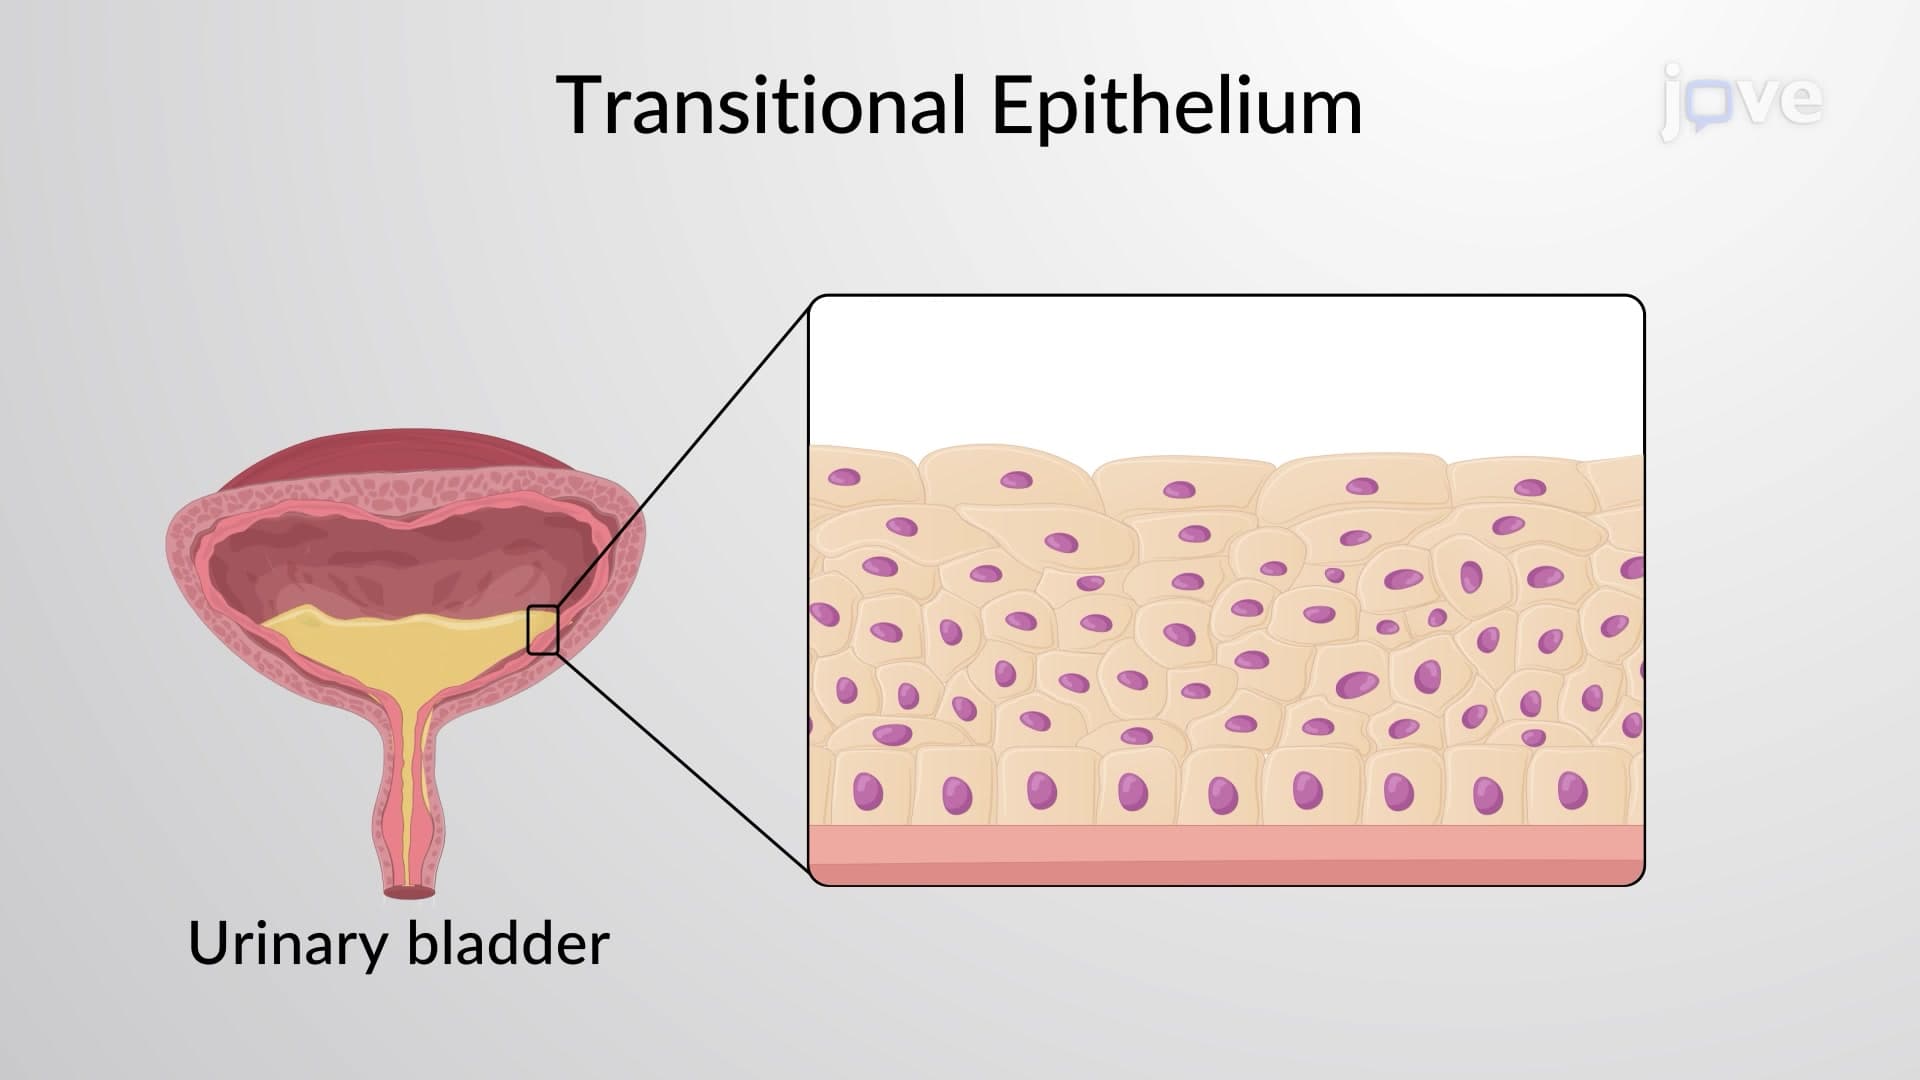 01:29
Classification of Epithelial Tissues: Stratified Epithelium
 02:07
Improving Translational Accuracy
02:07Improving Translational Accuracy
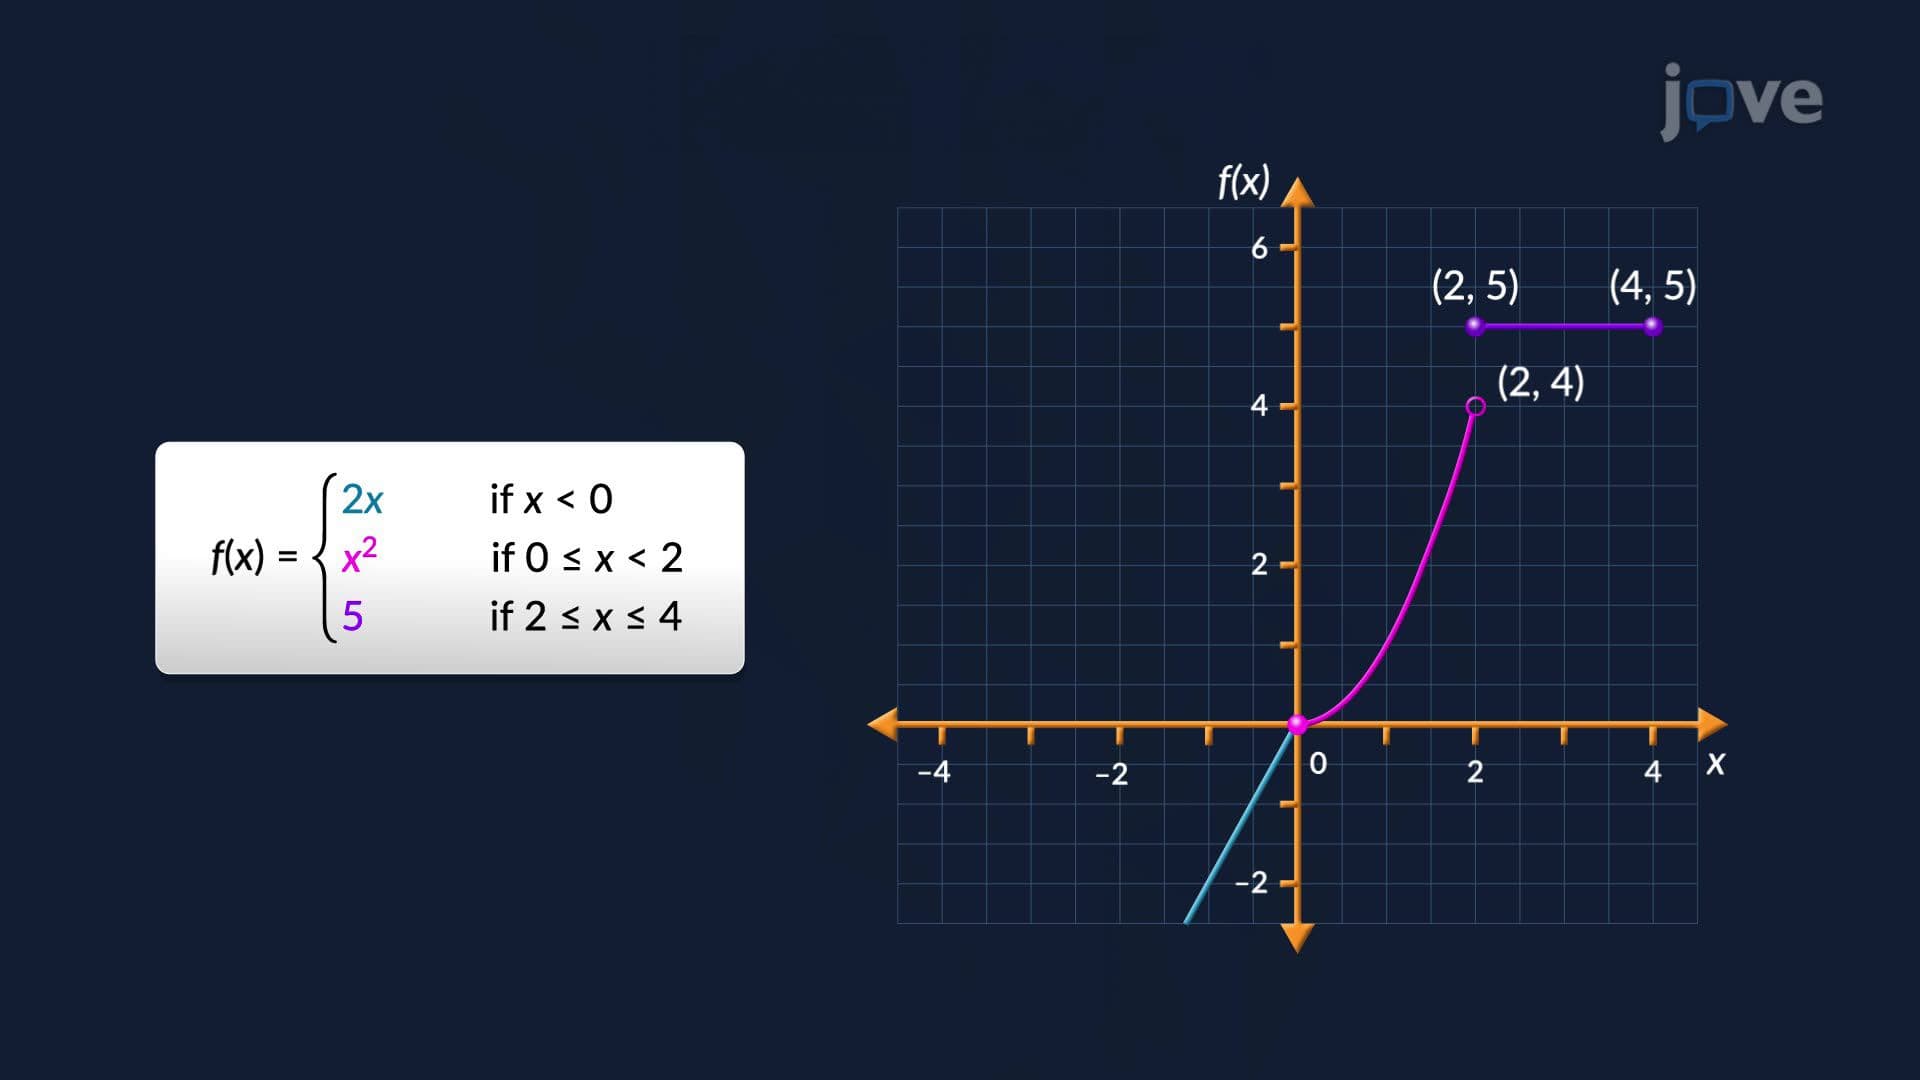 01:28
Piecewise-Defined Functions
 01:29
Rules for Defining Functions
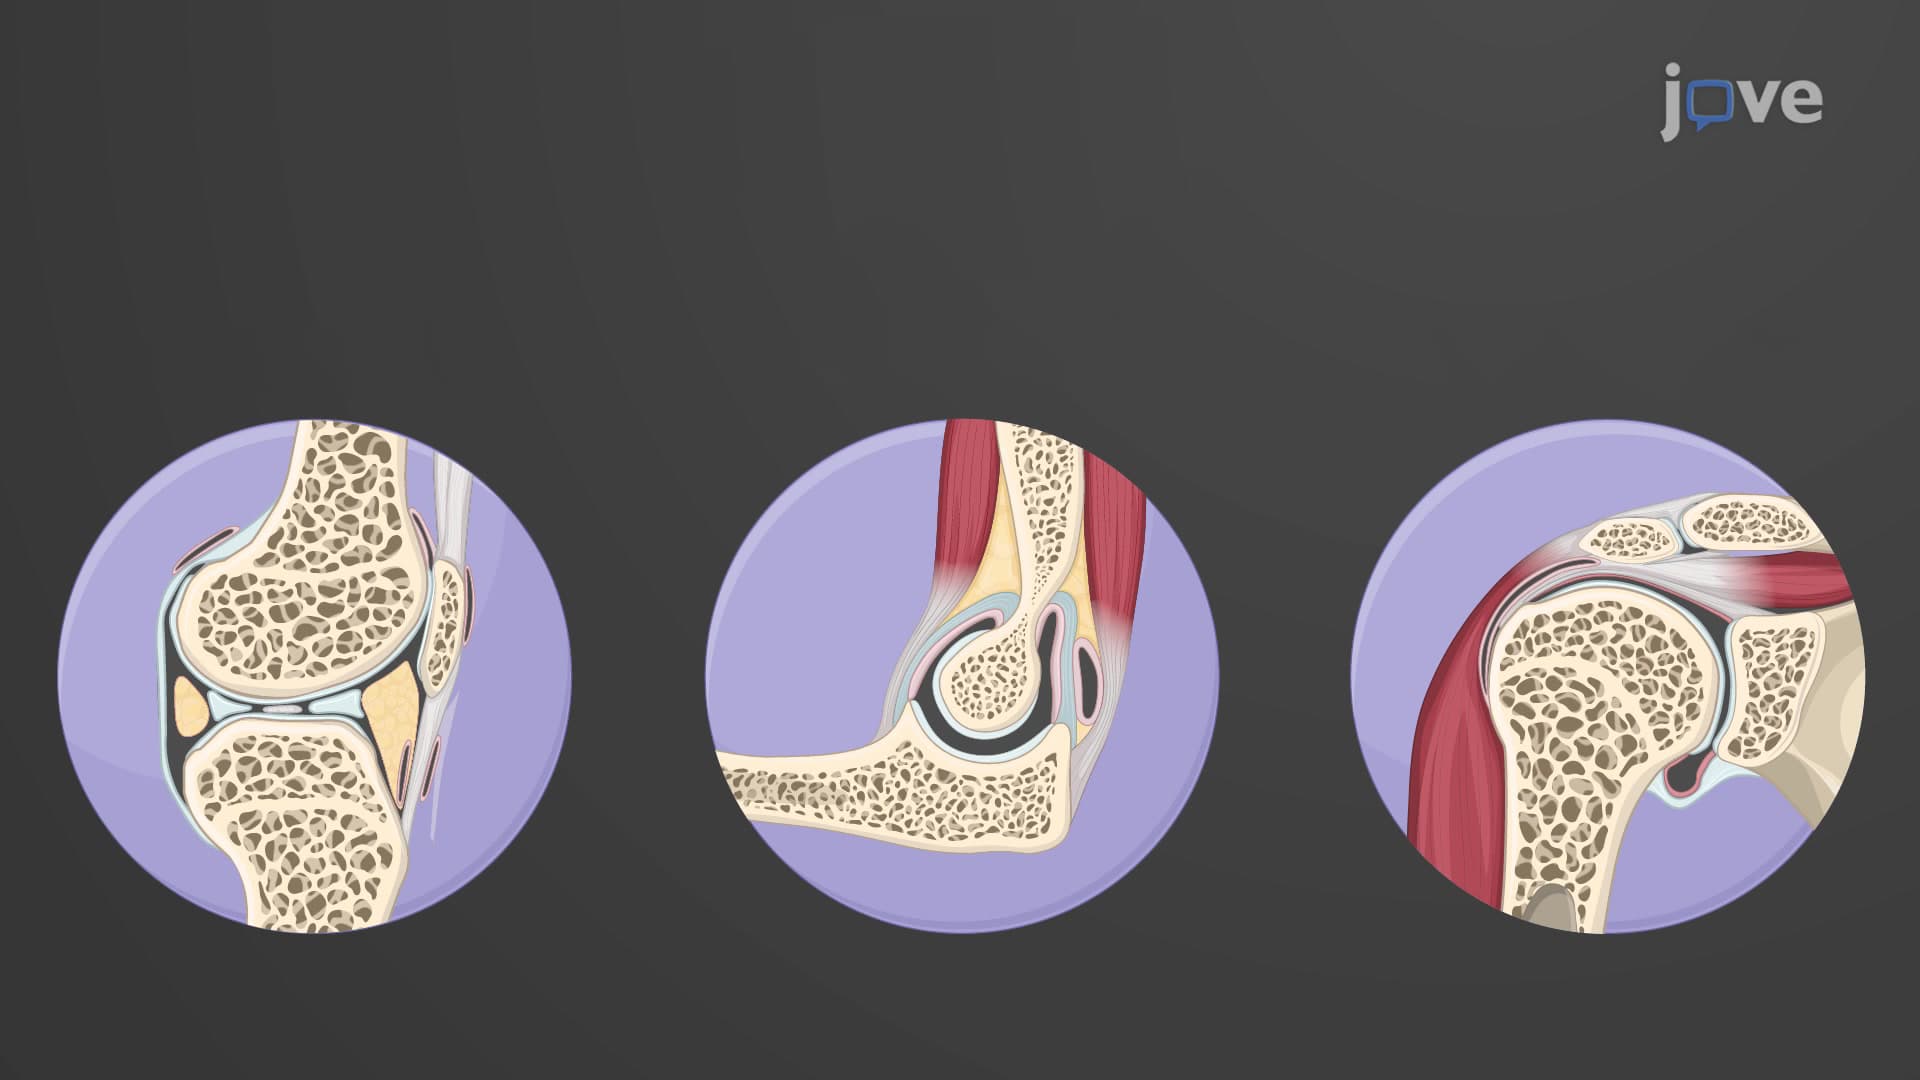 01:09
Functional Classification of Joints
The functional classification of joints is determined by the amount of mobility between the adjacent bones. Joints are functionally classified as a synarthrosis or immobile joint, an amphiarthrosis or slightly moveable joint, or as a diarthrosis, a freely moveable joint. Fibrous and cartilaginous joints can be functionally classified as either synarthroses or amphiarthroses, whereas all synovial joints are classified as diarthroses.
Synarthrosis
An...