Related Experiment Video
Updated: Feb 9, 2026

Catheter-based Endovascular Angioplasty for Fibrosing Mediastinitis-associated Pulmonary Vein Stenosis
Published on: August 26, 2025
[Prenatal interventional therapy in two cases with critical pulmonary stenosis or pulmonary atresia with intact
1Department of Maternal-Fetal Cardiology, Guangdong Cardiovascular Institute, Guangdong General Hospital, Guangdong Academy of Medical Sciences, Guangdong Province Key Laboratory of Structural Heart Disease, Guangzhou 510080, China.

Insights
Fetal pulmonary valvuloplasty (FPV) is a safe and effective procedure for fetuses with pulmonary atresia or stenosis, improving heart development and potentially preventing postnatal surgeries.
Area of Science:
- Cardiology
- Fetal Medicine
- Interventional Cardiology
Background:
- Pulmonary atresia with intact ventricular septum (PA-IVS) and critical pulmonary stenosis with intact ventricular septum (CPS-IVS) are severe congenital heart defects.
- Early intervention may improve outcomes by promoting right ventricular development.
Purpose of the Study:
- To explore criteria for case selection, technical aspects, and outcomes of fetal pulmonary valvuloplasty (FPV).
- To evaluate the impact of FPV on fetal cardiac development and hemodynamics.
Main Methods:
- Two cases (PA-IVS and CPS-IVS) underwent ultrasound-guided trans-abdominal FPV at 28 weeks gestation.
- Echocardiography monitored pulmonary valve function, right ventricular development, and hemodynamics post-procedure.
Main Results:
- FPV was technically successful, improving pulmonary valve opening in both cases.
- One case experienced restenosis, while the other showed significant improvement in cardiac function and hemodynamics post-FPV and postnatal intervention.
- Both fetuses were born alive, with one requiring further postnatal procedures.
Conclusions:
- FPV is safe and effective in the second and third trimesters, promoting fetal heart development.
- FPV may reduce the need for postnatal single-ventricle palliation and prevent fetal heart failure or death.
Abstract:
Objectives: Two cases who underwent fetal pulmonary valvuloplasty (FPV) for pulmonary atresia with intact ventricular septum (PA-IVS) or critical pulmonary stenosis with intact ventricular septum (CPS-IVS) successfully were reported. The aim of the report was to explore the criteria for case selection, the technical essentials of FPV, and the postpartum outcome of the fetus. Methods: One case with PA-IVS and the other with CPS-IVS were enrolled in September 2016 and February 2017 in Guangdong General Hospital, and both cases were diagnosed with severe right ventricular dysplasia and tricuspid regurgitation by fetal echocardiogram. Parameters of right ventricle development and hemodynamics from echocardiography included tricuspid/mitral annulus (TV/MV), right ventricle/left ventricle long-axis (RV/LV), pulmonary/aortic annulus (PV/AV), tricuspid inflow duration/cardiac cycle, degree of tricuspid regurgitation (TR), blood flow direction of arterial duct and ductus venosus. Multidisciplinary team including the maternal-fetal cardiology, pediatric cardiology, cardiac surgery, obstetrics, neonatology and anesthesiology was summoned to discuss the indications and timing of PFV. Two cases underwent ultrasound-guiding trans-abdominal PFV at the 28 weeks of gestational age. Echocardiography was performed to observe the opening and closing of the pulmonary valve, and to evaluate the development of right ventricle and improvement in hemodynamics every 2-4 weeks until delivery. Results: From the technical perspective, pulmonary balloon valvuloplasty was successfully performed in these two cases. The opening of pulmonary valve improved in these two cases at 2-4 weeks after FPV. However, an obvious restenosis was detected in the first case at 5-8 weeks after FPV. In the first case, the echocardiography parameters including TV/MV, RV/LV, PV/AV and tricuspid inflow duration/cardiac cycle increased from 0.56, 0.42, 0.85,0.26 to 0.59, 0.51, 0.87, 0.32 at 5-8 weeks after FPV, respectively. However, the direction of blood flow through the arterial duct was still reverse. In the second case, TV/MV, RV/LV, PV/AV and tricuspid inflow duration/cardiac cycle ratio increased from 0.70, 0.63, 0.91,0.35 to 0.80, 0.80, 0.97, 0.42 at 5-8 weeks after FPV, respectively. The direction of blood flow through the arterial duct changed to bidirectional. Both fetuses were born alive. The first case underwent pulmonary valve commissurotomy and modified Blalock-Taussig shunt on the 8(th) day after delivery and received follow-up for 6 months. The strategy for the next-step therapy was still pending. The second case underwent transcutaneous pulmonary balloon valvuloplasty on the 19(th) day after delivery and received follow-up for 3 months. The opening of pulmonary valve improved obviously and the cardiac function was normal in the second case. Conclusions: FPV is safe and effective for fetus during the second and third trimester of pregnancy, and FPV is beneficial for the development of fetal ventricle, valve and large artery. In addition, FPV may help to avoid the postnatal surgery for isolated single ventricle, improve fetal heart failure and prevent fetal death.

Related Concept Videos
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the...
 01:17
Other Pulmonary Disorders
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue,...
 01:19
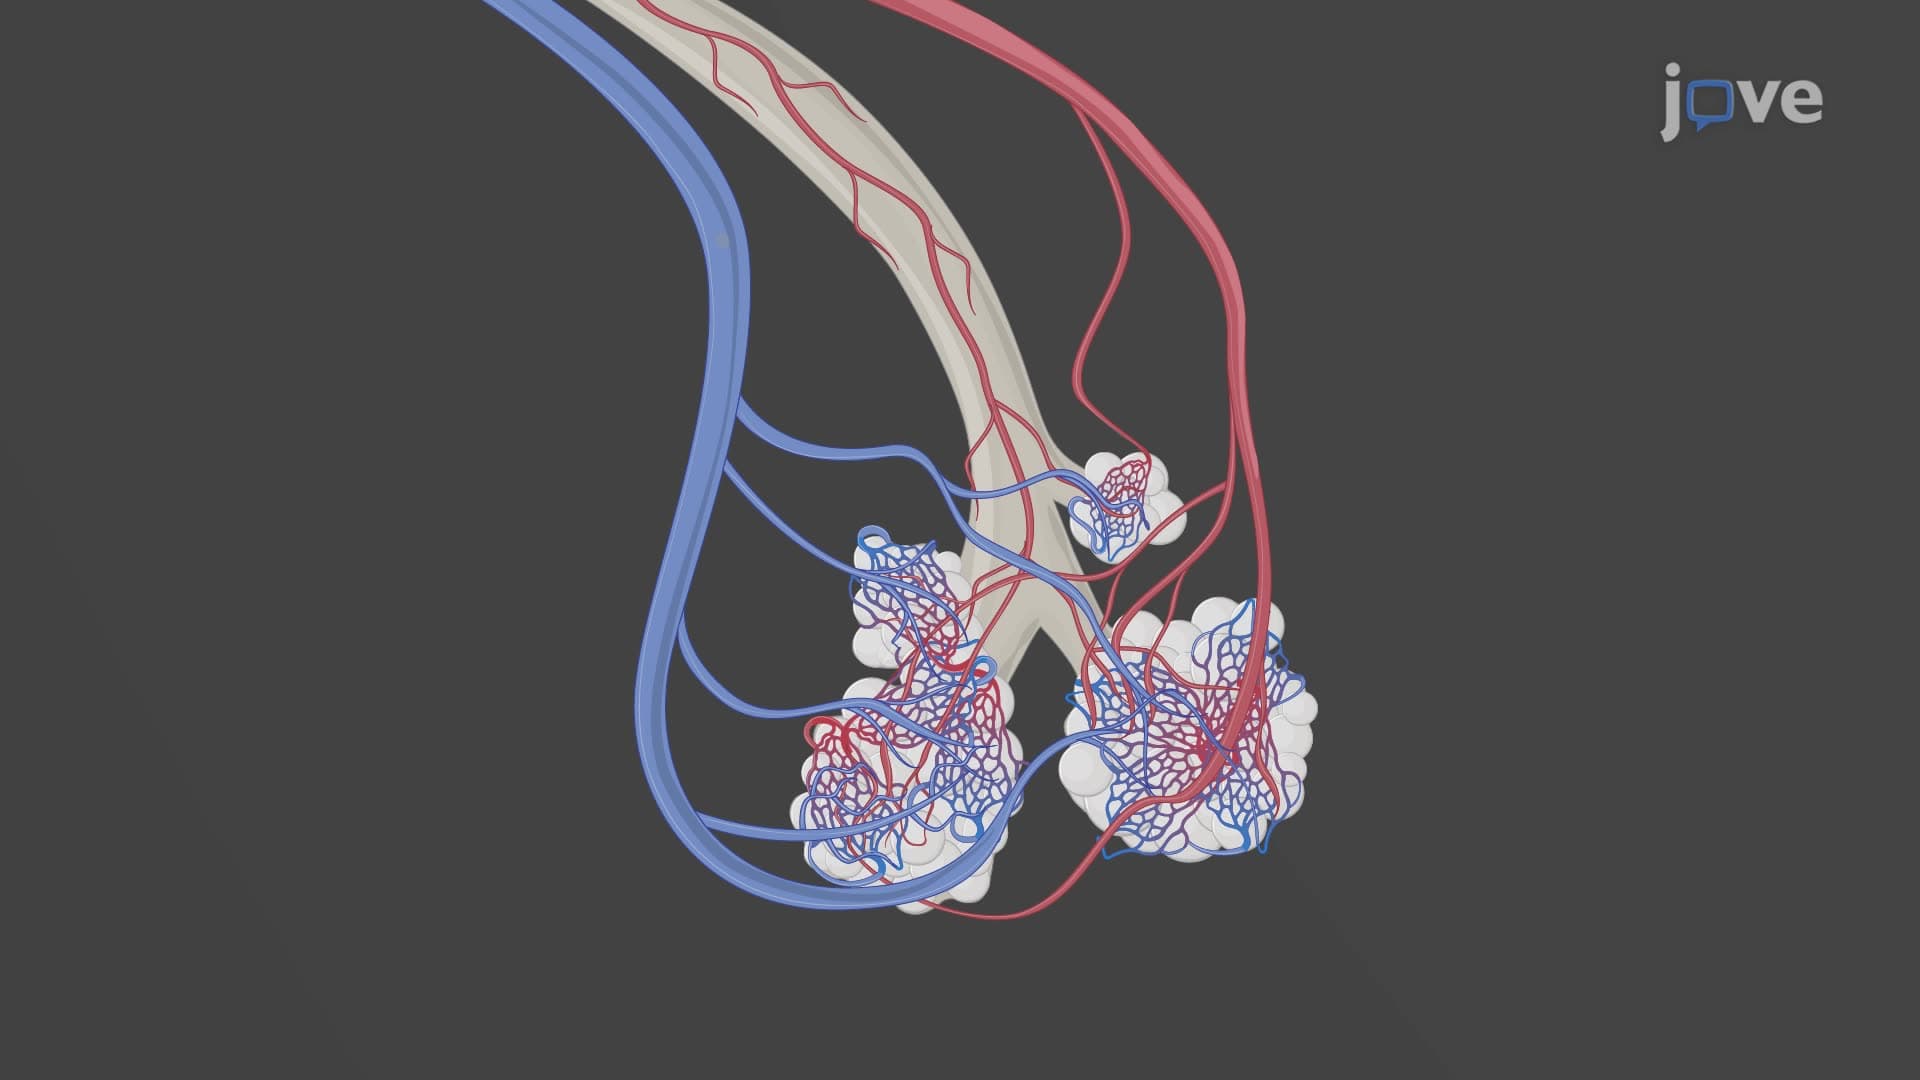
Overview of Pulmonary Circulation
The process begins with the right ventricle of the heart pumping deoxygenated blood into the pulmonary trunk. This large vessel extends about 5 centimeters before splitting into the left and right pulmonary arteries. These arteries...