Related Experiment Video
Updated: Feb 8, 2026

A Zebrafish Model of Diabetes Mellitus and Metabolic Memory
Published on: February 28, 2013
Lixisenatide Versus Insulin Glulisine on Fasting and Postbreakfast Systemic Hemodynamics in Type 2 Diabetes Mellitus
Lennart Tonneijck1, Marcel H A Muskiet2, Jos W Twisk3
1From the Department of Internal Medicine, Diabetes Center (L.T., M.H.A.M., M.H.H.K., M.M.S., D.H.v.R.) l.tonneijck@vumc.nl.

Abstract:
The prolonged treatment effects of a short-acting GLP-1RA (glucagon-like peptide-1 receptor agonist), such as lixisenatide, on fasting and postprandial systemic hemodynamics in type 2 diabetes mellitus patients are unknown. In this secondary analysis, we included 34 overweight insulin glargine-treated type 2 diabetes mellitus patients (mean±SD age, 62±7 years; HbA1c, 8.0±0.9%; systolic blood pressure [BP], 133.9±16.1 mm Hg; diastolic BP, 75.4±8.39 mm Hg) that were randomized to once-daily lixisenatide 20 μg or once-daily titrated insulin glulisine for 8 weeks. Systemic hemodynamics (oscillometric device and finger photoplethysmography), arterial stiffness (applanation tonometry), and cardiac sympathovagal balance (heart rate variability) were measured in the fasting state and repetitively (up to minute 175) after a standardized mixed breakfast. Acetaminophen was given orally to estimate gastric emptying rate. Lixisenatide did not affect fasting systemic hemodynamics compared with insulin glulisine from baseline to week 8. Postbreakfast overall, lixisenatide compared with insulin glulisine tended to increase systolic BP by 5.2±2.9 mm Hg (P=0.087) and increased diastolic BP by 5.4±1.4 mm Hg (P<0.001), with respective maximal differences of +10.2±3.7 mm Hg (P=0.007) and +7.2±1.5 mm Hg (P<0.001). Lixisenatide increased systemic vascular resistance (P<0.001) and arterial stiffness (P=0.007). No between-group differences in overall postbreakfast heart rate, cardiac output, or cardiac sympathovagal balance, and circulating catecholamines, angiotensin II, or aldosterone were observed. Both treatments lowered HbA1c similarly, whereas lixisenatide achieved greater reductions in postbreakfast plasma glucose excursions. Lixisenatide slowed gastric emptying rate, which statistically explained changes in postbreakfast BP. Lixisenatide compared with once-daily titrated insulin glulisine for 8 weeks does not affect fasting but increases postbreakfast BP in insulin glargine-treated type 2 diabetes mellitus patients. This effect could, at least in part, be explained by reduced passage rate of nutrients and water and activation of the gastrovascular reflex.
Related Concept Videos
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:27
Insulin Formulations: Types and Delivery
Short-acting insulins are divided into...
 02:13
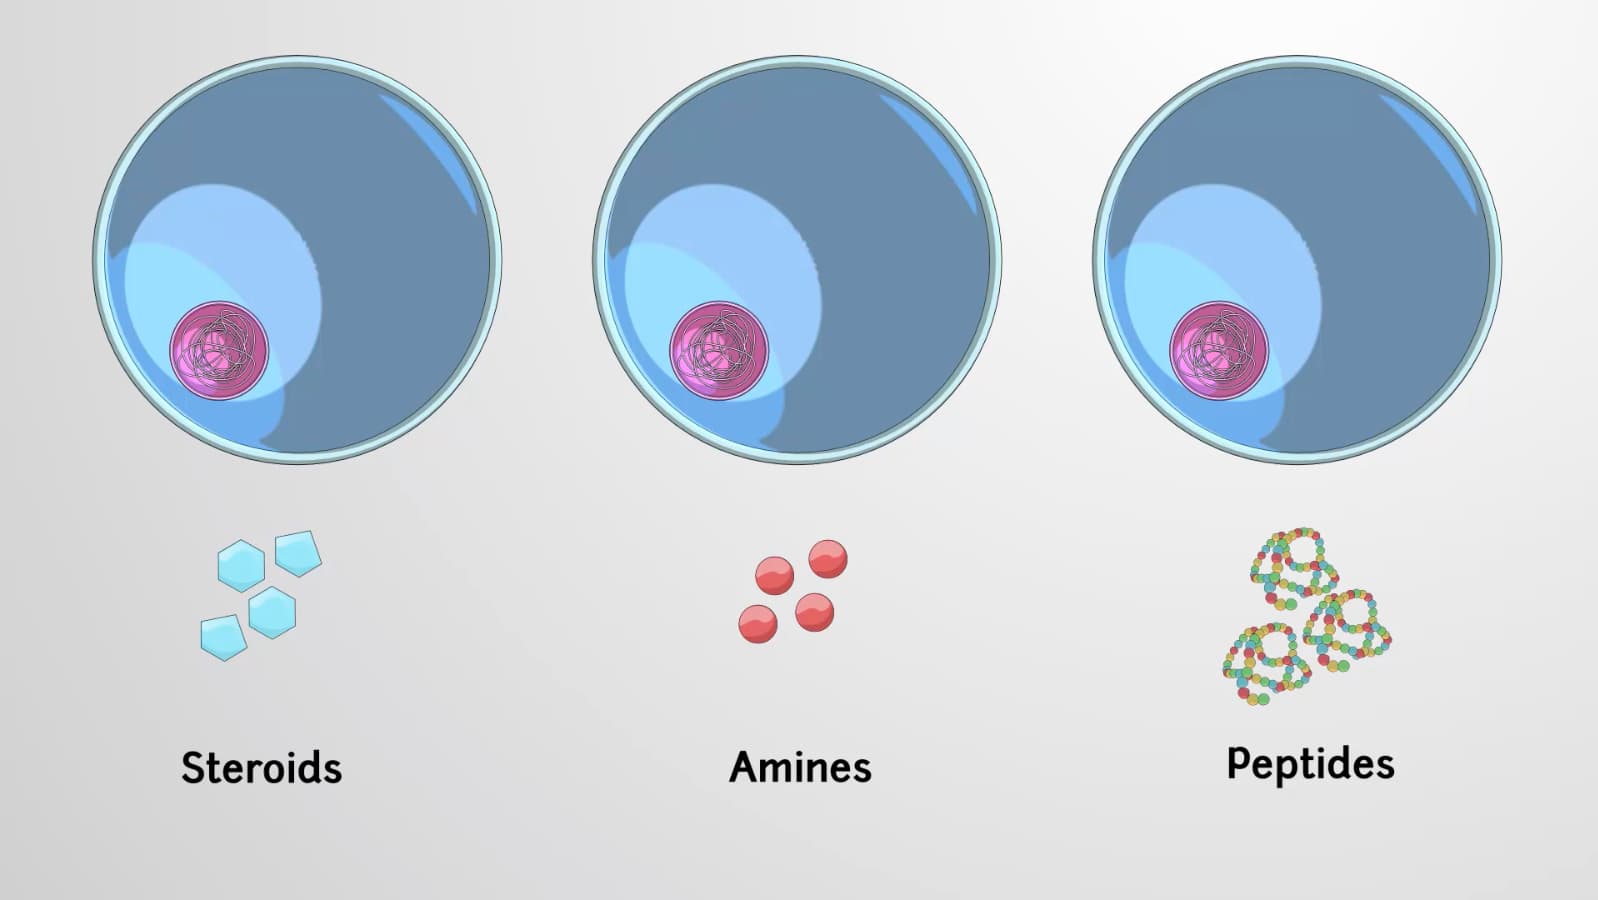
Types of Hormones
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility,...
 01:05
Insulin Secretory Vesicles