Related Experiment Video
Updated: Feb 8, 2026

Tissue Preparation and Immunostaining of Mouse Sensory Nerve Fibers Innervating Skin and Limb Bones
Published on: January 26, 2012
Validity of Clinical Small-Fiber Sensory Testing to Detect Small-Nerve Fiber Degeneration

Background:
Small-nerve fiber, or small-fiber, degeneration commonly occurs in patients with peripheral neuropathies, resulting in a deterioration of nerve function. Currently, the gold standard to identify small-fiber degeneration is through skin biopsy. Simple clinical tests aim to identify small-fiber degeneration, but their validity remains unknown.
Objectives:
To examine the validity of clinical tests to assess small-nerve fiber degeneration, using carpal tunnel syndrome as a model neuropathy.
Methods:
One hundred seven participants (22 healthy, 85 with carpal tunnel syndrome) in this prospective, cross-sectional diagnostic accuracy study underwent pinprick testing of the index finger and were assessed for cold detection threshold and warm detection threshold using quantitative sensory testing. In a subgroup of patients with carpal tunnel syndrome (n = 51), cold and warm sensations were also tested, using coins at room and body temperature, respectively. The validity of these clinical tests was established against intra-epidermal nerve fiber density measured in skin biopsies from the index finger.
Results:
Optimal validity occurred with clusters of tests. Specifically, normal warm or cold sensation is highly sensitive to rule out small-fiber degeneration (sensitivity, 0.98; 95% confidence interval [CI]: 0.85, 0.99), but has a low specificity (0.20; 95% CI: 0.03, 0.52). By contrast, a reduction in pinprick is highly specific (0.88; 95% CI: 0.72, 0.95), and so can be used to rule in small-fiber degeneration. For quantitative sensory testing, the highest specificity (0.83) occurs for warm detection threshold and the highest sensitivity (0.84; 95% CI: 0.72, 0.91) for cold detection threshold or warm detection threshold.
Conclusion:
Pinprick testing, followed by warm and cold tests if pinprick is normal, is a valid and cost-effective method to detect small-fiber degeneration. For quantitative sensory testing, warm detection threshold is useful for ruling in small-fiber degeneration. To rule out small-fiber degeneration, both cold detection threshold and warm detection threshold must be negative.
Level Of Evidence:
Diagnosis, level 2. J Orthop Sports Phys Ther 2018;48(10):767-774. Epub 22 Jun 2018. doi:10.2519/jospt.2018.8230.
Related Concept Videos
 01:48
Classification of Skeletal Muscle Fibers
Slow-Twitch Muscle Fibers
Slow oxidative, muscle fibers appear red due to large numbers of capillaries and high levels of...
 01:24
Local Anesthetics: Differential Sensitivity of Nerve Fibers
 01:22
Fiber Reinforced Concrete
 01:32
Types of Skeletal Muscle Fibers
Fast-twitch fibers
Fast-twitch fibers, or Type II fibers, are designed for quick, powerful bursts of speed and strength. They reach peak tension within approximately 0.01 seconds following stimulation. Characterized by a large diameter and densely packed myofibrils, these fibers contain...
 01:13
Formation of Muscle Fibers from Myoblasts
Muscle progenitor cells (MPCs) are formed from the myotomes. MPCs express genes that encode the transcription factors Pax3 and Pax7. Along with Pax 3/7, other transcription...
 01:17
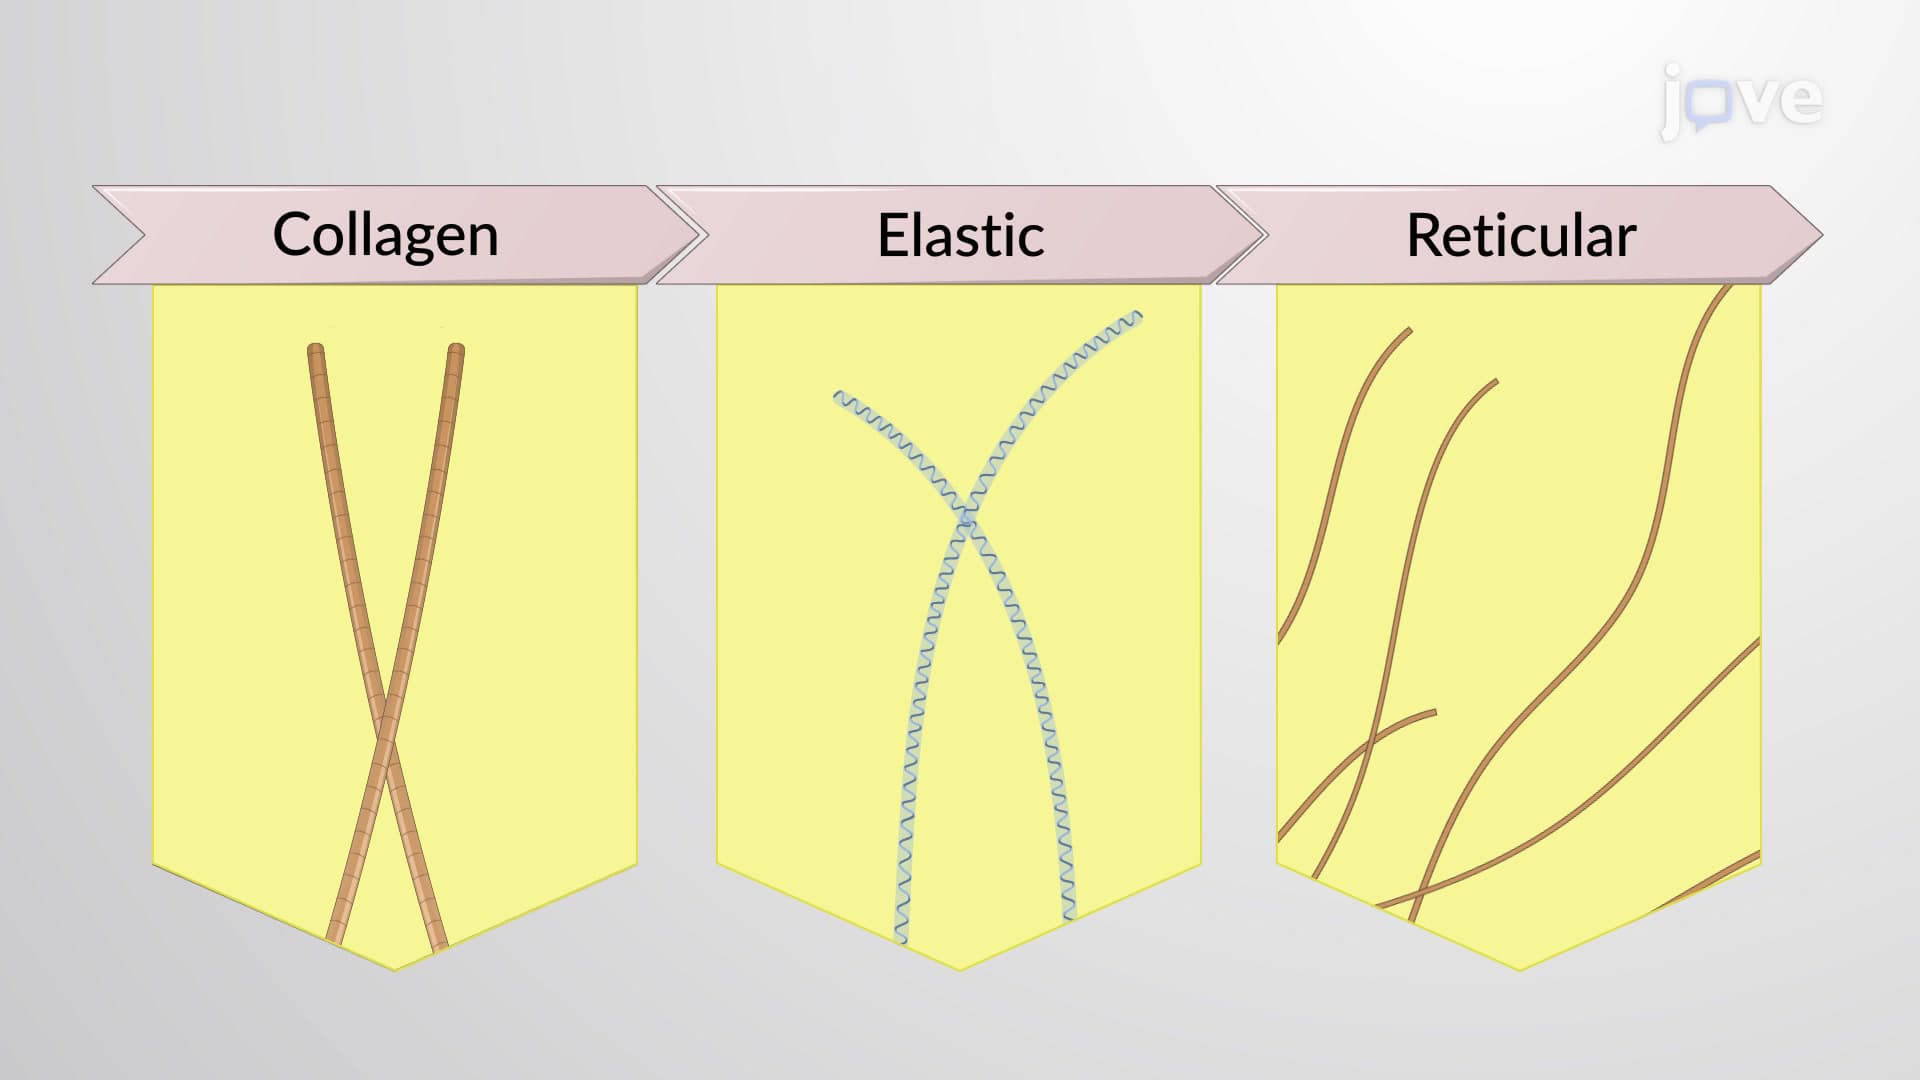
Connective Tissue Fibers and Ground Substance