Related Experiment Video
Updated: Feb 8, 2026
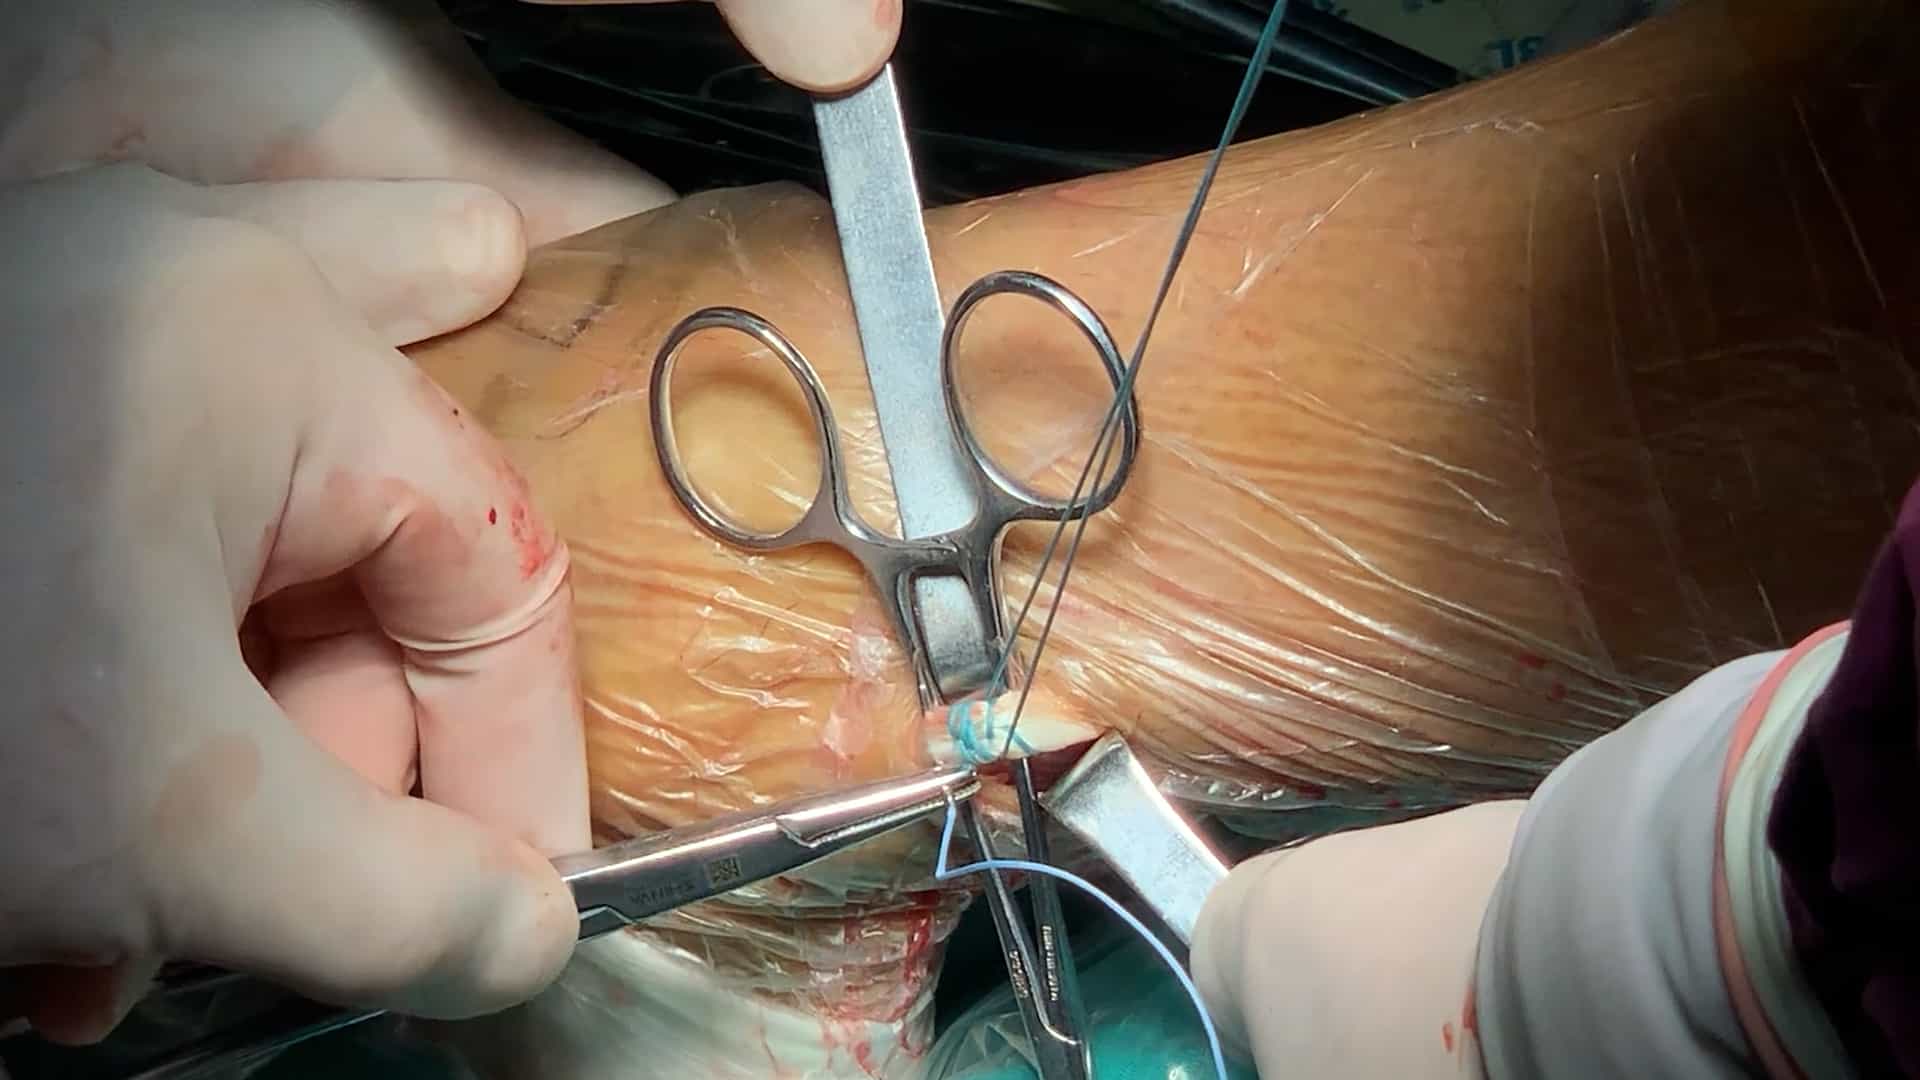
Harvesting of Peroneus Longus Tendon Autograft
Published on: September 2, 2025
Muscle Shortening and Spastic Cocontraction in Gastrocnemius Medialis and Peroneus Longus in Very Young Hemiparetic
M Vinti1,2, N Bayle1,2, A Merlo3
1EA 7377 BIOTN, Université Paris Est Créteil (UPEC), Créteil, France.

Insights
In young children with cerebral palsy (CP), the gastrosoleus complex (GSC) may shorten early. Excessive gastrocnemius medialis (GM) and peroneus longus (PL) cocontraction during gait contributes to dynamic equinovalgus.
Area of Science:
- Neurology
- Pediatrics
- Orthopedics
Background:
- Muscle shortening and spastic cocontraction in ankle plantar flexors are common in early childhood cerebral palsy (CP).
- These issues can significantly alter gait patterns from a young age.
Purpose of the Study:
- To evaluate gastrosoleus complex (GSC) length and gastrocnemius medialis (GM) and peroneus longus (PL) muscle activity during the swing phase of gait.
- To assess these parameters in very young hemiparetic children diagnosed with equinovalgus.
Main Methods:
- An observational, retrospective study involving ten very young hemiparetic children (3 ± 1 years) with CP.
- Muscle extensibility of the GSC was assessed using the Tardieu scale (XV1).
- Electromyography (EMG) of GM and PL was monitored during the gait swing phase, with cocontraction index (CCI) calculated for different phases.
Main Results:
- The paretic GSC showed reduced extensibility (mean XV1 = 100°) compared to the nonparetic side (p = 0.032).
- GSC extensibility decreased with age in children between 2 and 5 years.
- Higher CCI for both GM (0.32 vs 0.15) and PL (0.52 vs 0.24) was observed on the paretic side during swing phase, with a significant early difference for PL.
Conclusions:
- The paretic GSC can shorten rapidly in the initial years of life in children with CP.
- Excessive GM and PL cocontraction during the swing phase contributes to dynamic equinovalgus.
- Monitoring and preserving muscle extensibility, alongside cocontraction measurements, is crucial for early intervention in CP.
Objectives:
Muscle shortening and spastic cocontraction in ankle plantar flexors may alter gait since early childhood in cerebral palsy (CP). We evaluated gastrosoleus complex (GSC) length, and gastrocnemius medialis (GM) and peroneus longus (PL) activity during swing phase, in very young hemiparetic children with equinovalgus.
Methods:
This was an observational, retrospective, and monocentric outpatient study in a pediatric hospital. Ten very young hemiparetic children (age 3 ± 1 yrs) were enrolled. These CP children were assessed for muscle extensibility (Tardieu scale XV1) in GSC (angle of arrest during slow-speed passive ankle dorsiflexion with the knee extended) and monitored for GM and PL electromyography (EMG) during the swing phase of gait. The swing phase was divided into three periods (T1, T2, and T3), in which we measured a cocontraction index (CCI), ratio of the Root Mean Square EMG (RMS-EMG) from each muscle during that period to the peak 500 ms RMS-EMG obtained from voluntary plantar flexion during standing on tiptoes (from several 5-second series, the highest RMS value was computed over 500 ms around the peak).
Results:
On the paretic side: (i) the mean XV1-GSC was 100° (8°) (median (SD)) versus 106° (3°) on the nonparetic side (p = 0.032, Mann-Whitney); (ii) XV1-GSC diminished with age between ages of 2 and 5 (Spearman, ρ = 0.019); (iii) CCIGM and CCIPL during swing phase were higher than on the nonparetic side (CCIGM, 0.32 (0.20) versus 0.15 (0.09), p < 0.01; CCIPL, 0.52 (0.30) versus 0.24 (0.17), p < 0.01), with an early difference significant for PL from T1 (p = 0.03).
Conclusions:
In very young hemiparetic children, the paretic GSC may rapidly shorten in the first years of life. GM and PL cocontraction during swing phase are excessive, which contributes to dynamic equinovalgus. Muscle extensibility (XV1) may have to be monitored and preserved in the first years of life in children with CP. Additional measurements of cocontraction may further help target treatments with botulinum toxin, especially in peroneus longus.


Related Concept Videos
 01:29
Drug Dosing: Infants and Children
 01:48
Classification of Skeletal Muscle Fibers
Slow-Twitch Muscle Fibers
Slow oxidative, muscle fibers appear red due to large numbers of capillaries and high levels of...
 01:20
Muscles of the Eye
Extraocular Muscles
The six extraocular muscles surround the eyeball and control its movements. They are responsible for a wide range of eye motions, including looking up, down, left, right, and...
 01:19
Muscles that Move the Head
The bilateral sternocleidomastoid, or SCM, and the suprahyoid and infrahyoid muscles are significant head flexors. The SCM muscles originate at the sternum and clavicle and attach to the mastoid process of the temporal bone. The SCM contracts bilaterally to bend the head forward, whereas...
 01:21
Muscles of the Abdomen
Anterolateral Region
The anterolateral region comprises five paired muscles classified into the lateral and...
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...