Related Experiment Video
Updated: Feb 8, 2026


Detection of Low Copy Number Integrated Viral DNA Formed by In Vitro Hepatitis B Infection
Published on: November 7, 2018
Sustained Virologic Response and Costs Associated with Direct-Acting Antivirals for Chronic Hepatitis C Infection in
Timothy T Pham1, Shellie L Keast1, Kevin C Farmer1
11 University of Oklahoma College of Pharmacy, Oklahoma City.

Insights
Direct-acting antiviral (DAA) treatment for hepatitis C virus (HCV) shows high success in Oklahoma Medicaid members with reported outcomes. Cirrhosis increases treatment failure risk, highlighting the need for better follow-up and care access.
Area of Science:
- Hepatology
- Pharmacoeconomics
- Public Health
Background:
- Direct-acting antiviral (DAA) hepatitis C virus (HCV) treatment outcomes are understudied in Medicaid populations.
- This study examines clinical and economic impacts of DAAs for Oklahoma Medicaid members with chronic HCV.
Purpose of the Study:
- Assess treatment failure and costs associated with DAA therapy in Oklahoma Medicaid members.
- Identify patient, treatment, and clinical factors influencing sustained virological response (SVR12) and healthcare costs.
Main Methods:
- Cross-sectional analysis of Oklahoma Medicaid claims data (2014-2016) for adult HCV patients treated with DAAs.
- Multivariable logistic and gamma regressions evaluated predictors of SVR12 failure and costs, controlling for demographics, DAA type, adherence, and comorbidities.
Main Results:
- Of 906 DAA-treated members, 40.6% had reported SVR12 outcomes; 8.4% experienced treatment failure.
- Cirrhosis (compensated and decompensated) significantly increased odds of SVR12 failure (ORs 3.52-6.69).
- Ledipasvir/sofosbuvir was linked to lower costs, while decompensated cirrhosis and treatment failure increased costs.
Conclusions:
- Nearly 60% of treated members lacked reported SVR12 outcomes, indicating significant loss to follow-up.
- Among those with outcomes, DAA treatment success was high, but cirrhosis predicted failure.
- Interventions improving access to care and treatment completion are crucial for enhancing HCV treatment success.
Background:
Outcomes involving newer direct-acting antiviral (DAA) hepatitis C virus (HCV) regimens have not been studied extensively among the Medicaid population.
Objective:
To assess clinical (treatment failure) and economic outcomes for chronic HCV-infected Oklahoma Medicaid members following treatment with DAAs and to measure associations with patient, treatment, and clinical characteristics.
Methods:
This cross-sectional study used Oklahoma Medicaid pharmacy and medical claims data for adult members who used a newer DAA agent and had reported a successful or failed sustained virological response rate 12 weeks after therapy completion (SVR12) from January 1, 2014, to June 30, 2016. Multivariable logistic and gamma regressions assessed predictors of SVR12 failure and costs controlling for member demographics (i.e., age, sex, race, rural residence); type of DAA and adherence; clinical characteristics (e.g., comorbid conditions, advanced liver disease); and the implementation of changes to a prior authorization program.
Results:
Of 934 Medicaid members eligible for treatment with DAAs between January 1, 2014, and June 30, 2016, 906 received DAA treatment, 40.6% (368/906) had reported SVR12 outcomes, and 59.4% (n = 538) did not have a reported SVR recorded. Of those with reported SVR12 outcomes, patients were 53.1 ± 9.7 years of age, 51.1% were male, 8.4% had SVR12 failure, and each member had mean costs of $140,283 ± $52,779. Multivariable analyses indicated higher odds of SVR12 failure was independently associated with cirrhosis (OR [decompensated] = 6.69 and OR [compensated] = 3.52, P < 0.001), while males had higher odds of failure than females (OR = 3.34, P < 0.010). No significant difference in SVR12 failure was noted, according to DAA type or a medication adherence threshold of > 95%. Ledipasvir/sofosbuvir was independently associated with lower costs (exp[b] = 0.81; P < 0.001) compared with sofosbuvir, while higher costs were associated with decompensated cirrhosis (exp[b] = 1.22; P < 0.001) and treatment failure (exp[b] = 1.18, P < 0.010). In an analysis including members without reported SVR12 outcomes, decompensated and compensated cirrhosis had lower odds (P < 0.001) of no reported SVR12 from ambulatory clinic settings.
Conclusions:
Almost 60% of Medicaid members receiving DAA treatment did not have a final reported SVR12 outcome. Among those with viral load measurements, treatment success was high and both decompensated and compensated cirrhosis were independently associated with significantly higher odds of treatment failure. Addressing a loss to follow-up among HCV patients and curtailing the development of cirrhosis to improve treatment success may warrant interventions that improve access to care and remove barriers that impede treatment initiation and completion.
Disclosures:
No outside funding supported this study. Pham, Keast, Holderread, Nesser, and Skrepnek disclose either employment by the Oklahoma Health Care Authority or contractual work for this employer. Pham discloses fellowship funding from Purdue Pharma unrelated to this study. Keast and Skrepnek disclose research grant funding from Gilead Sciences and Abbvie. Holderread also reports grant funding from Gilead Sciences and fees from PRIME Education. Thompson, Farmer, and Rathbun have nothing to disclose.


Related Concept Videos
 01:31
Direct-Acting Cholinergic Agonists: Pharmacokinetics
 01:11
Direct-Acting Cholinergic Agonists: Therapeutic Uses
 01:30
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
 01:43
Sustainable Development
 00:59
Direct-Acting Cholinergic Agonists: Pharmacological Actions
 01:22
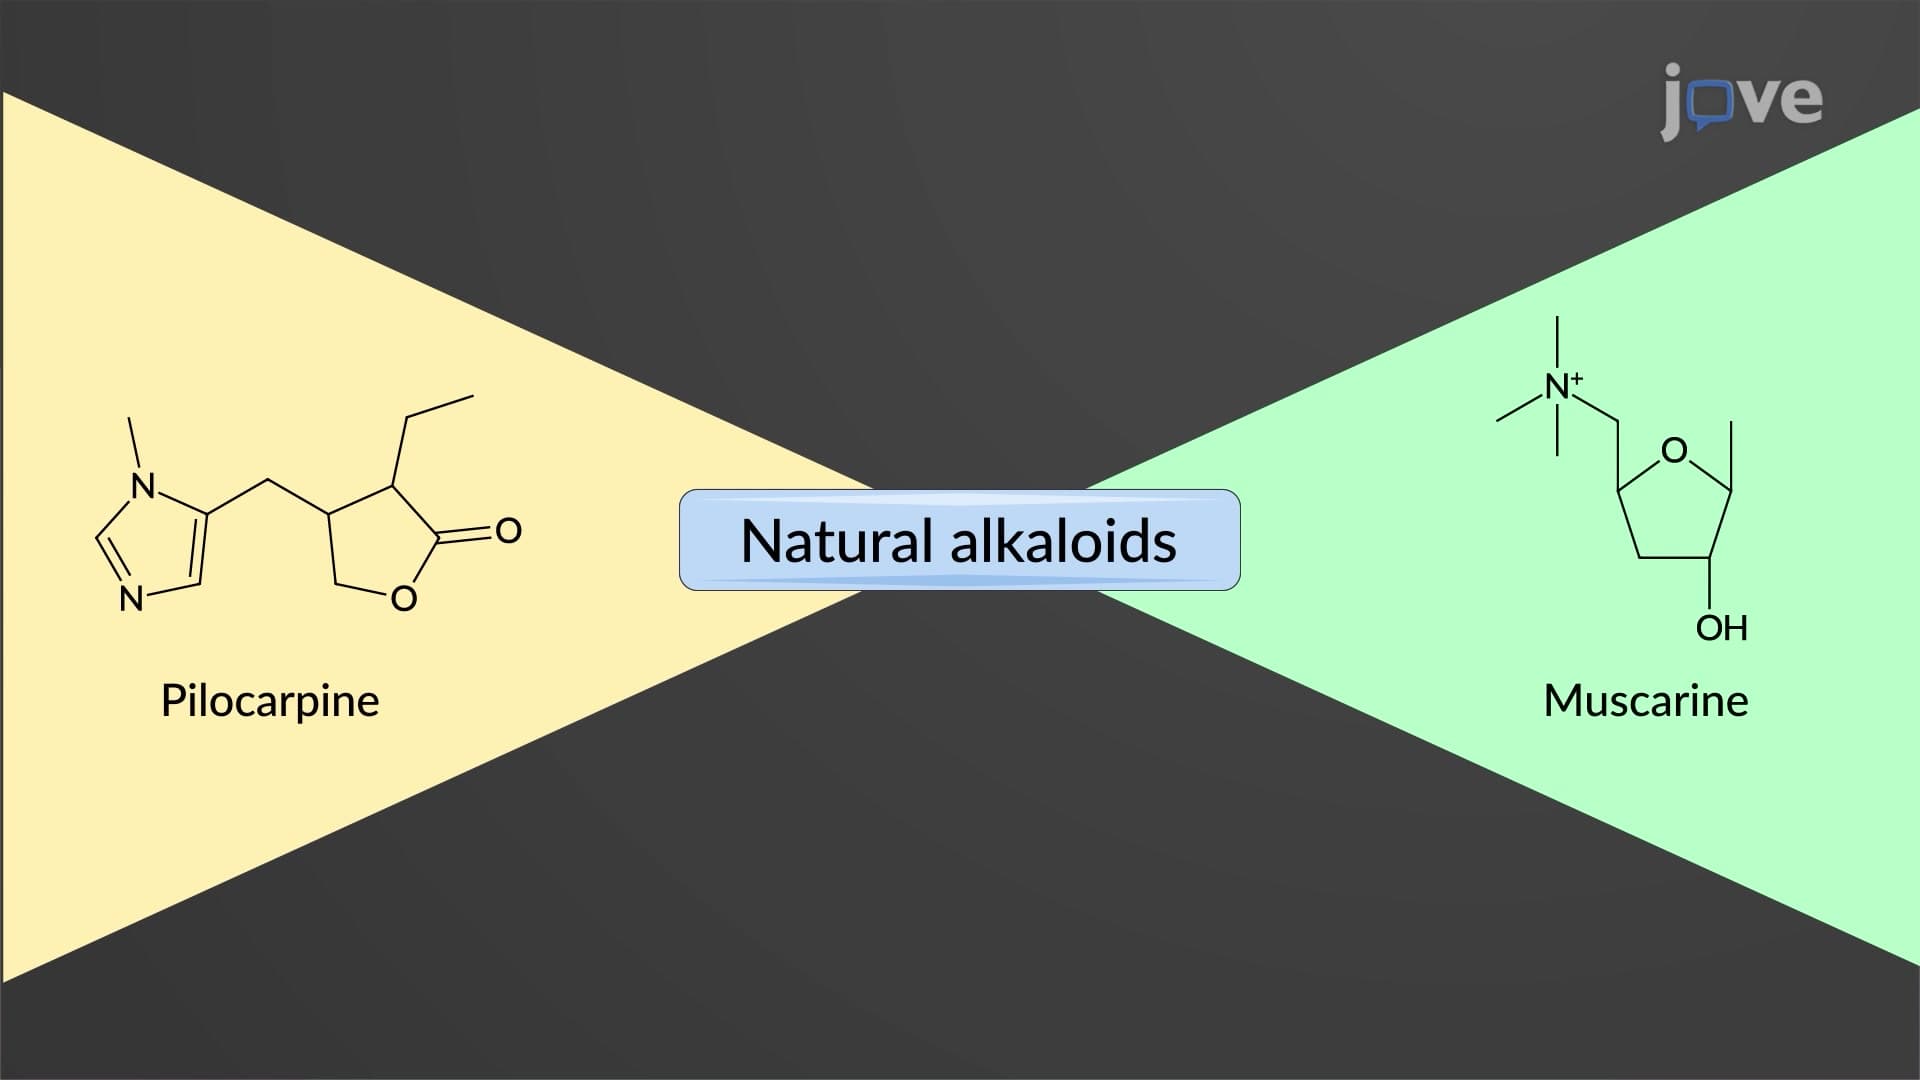
Direct-Acting Cholinergic Agonists: Chemistry and Structure-Activity Relationship
The direct-acting...