Related Experiment Video
Updated: Feb 8, 2026

Surgical Swine Model of Chronic Cardiac Ischemia Treated by Off-Pump Coronary Artery Bypass Graft Surgery
Published on: March 27, 2018
Outcomes After Coronary Stenting or Bypass Surgery for Men and Women With Unprotected Left Main Disease: The EXCEL
Patrick W Serruys1, Rafael Cavalcante2, Carlos Collet3
1Imperial College London, London, United Kingdom.

Insights
In patients with unprotected left main disease, sex was not an independent predictor of outcomes after revascularization. However, women treated with percutaneous coronary intervention (PCI) showed a trend toward worse results, influenced by comorbidities and procedural complications.
Area of Science:
- Cardiovascular Medicine
- Interventional Cardiology
- Clinical Trials
Background:
- Previous studies, including the SYNTAX trial, suggested a significant interaction between sex and revascularization strategy, with women experiencing higher mortality with percutaneous coronary intervention (PCI) compared to coronary artery bypass grafting (CABG).
- Unprotected left main disease poses a significant challenge in cardiovascular interventions, necessitating careful consideration of treatment strategies based on patient characteristics.
Purpose of the Study:
- To evaluate the outcomes of coronary artery bypass grafting surgery (CABG) versus percutaneous coronary intervention (PCI) stratified by sex in patients with unprotected left main disease within the EXCEL trial.
- To determine if sex is an independent predictor of adverse outcomes following revascularization in this patient population.
Main Methods:
- The EXCEL trial was a multinational randomized trial comparing PCI with everolimus-eluting stents to CABG in patients with unprotected left main disease.
- The primary endpoint was a composite of all-cause death, myocardial infarction, or stroke assessed at 3 years post-intervention.
Main Results:
- While sex was not an independent predictor of the primary endpoint at 3 years (HR 1.10; P=0.53), significant interaction effects were observed at 30 days (P=0.003) and a trend at 3 years (P=0.06).
- Women undergoing PCI had higher rates of all-cause death, myocardial infarction, or stroke at 30 days (8.9%) and 3 years (19.7%) compared to women undergoing CABG (6.2% and 14.6%, respectively).
- These differences were attributed to higher periprocedural myocardial infarction rates in women after PCI and in men after CABG, alongside higher comorbidity burden in women.
Conclusions:
- Sex is not an independent predictor of adverse outcomes after revascularization for unprotected left main disease in the EXCEL trial.
- Women treated with PCI demonstrated a trend towards worse outcomes, linked to comorbidities and increased periprocedural complications.
- Further research is needed to establish the optimal revascularization strategy for women with complex coronary artery disease.
Objectives:
The aim of the present study was to assess outcomes after coronary artery bypass grafting surgery (CABG) and percutaneous coronary intervention (PCI) according to sex in a large randomized trial of patients with unprotected left main disease.
Background:
In the SYNTAX (Synergy Between Percutaneous Coronary Intervention With Taxus and Cardiac Surgery) trial, sex had a significant interaction effect with revascularization strategy, and women had an overall higher mortality when treated with PCI than CABG.
Methods:
The EXCEL (Evaluation of XIENCE Versus Coronary Artery Bypass Surgery for Effectiveness of Left Main Revascularization) trial was a multinational randomized trial that compared PCI with everolimus-eluting stents and CABG in patients with unprotected left main disease. The primary endpoint was the composite of all-cause death, myocardial infarction, or stroke at 3 years.
Results:
Of 1,905 patients randomized, 1,464 (76.9%) were men and 441 (23.1%) were women. Compared with men, women were older; had higher prevalence rates of hypertension, hyperlipidemia, and diabetes; and were less commonly smokers but had lower coronary anatomic burden and complexity (mean SYNTAX score 24.2 vs. 27.2, p < 0.001). By multivariate analysis, sex was not independently associated with either the primary endpoint (hazard ratio [HR]: 1.10; 95% confidence interval [CI]: 0.82 to 1.48; p = 0.53) or all-cause death (HR: 1.39; 95% CI: 0.92 to 2.10; p = 0.12) at 3 years. At 30 days, all-cause death, myocardial infarction, or stroke had occurred in 8.9% of woman treated with PCI, 6.2% of women treated with CABG, 3.6% of men treated with PCI, and 8.4% of men treated with CABG (p for interaction = 0.003). The 3-year rate of the composite primary endpoint was 19.7% in women treated with PCI, 14.6% in women treated with CABG, 13.8% in men treated with PCI, and 14.7% in men treated with CABG (p for interaction = 0.06). These differences were driven by higher periprocedural rates of myocardial infarction in women after PCI and in men after CABG.
Conclusions:
In patients with unprotected left main disease in the EXCEL trial, sex was not an independent predictor of adverse outcomes after revascularization. However, women undergoing PCI had a trend toward worse outcomes, a finding related to associated comorbidities and increased periprocedural complications. Further studies are required to determine the optimal revascularization modality in women with complex coronary artery disease.
More Related Videos
 13:10
Direct Re-implantation of Left Coronary Artery into the Aorta in Adults with Anomalous Origin of Left Coronary Artery from the Pulmonary Artery ALCAPA
Published on: April 24, 2017
 12:00
Evaluation of a Novel Laser-assisted Coronary Anastomotic Connector - the Trinity Clip - in a Porcine Off-pump Bypass Model
Published on: November 24, 2014
Related Concept Videos
 01:30
Coronary Artery Disease I: Introduction
 01:26
Coronary Artery Disease II: Pathophysiology
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:18
Microsoft Excel: Plotting Mean, SD, and SE
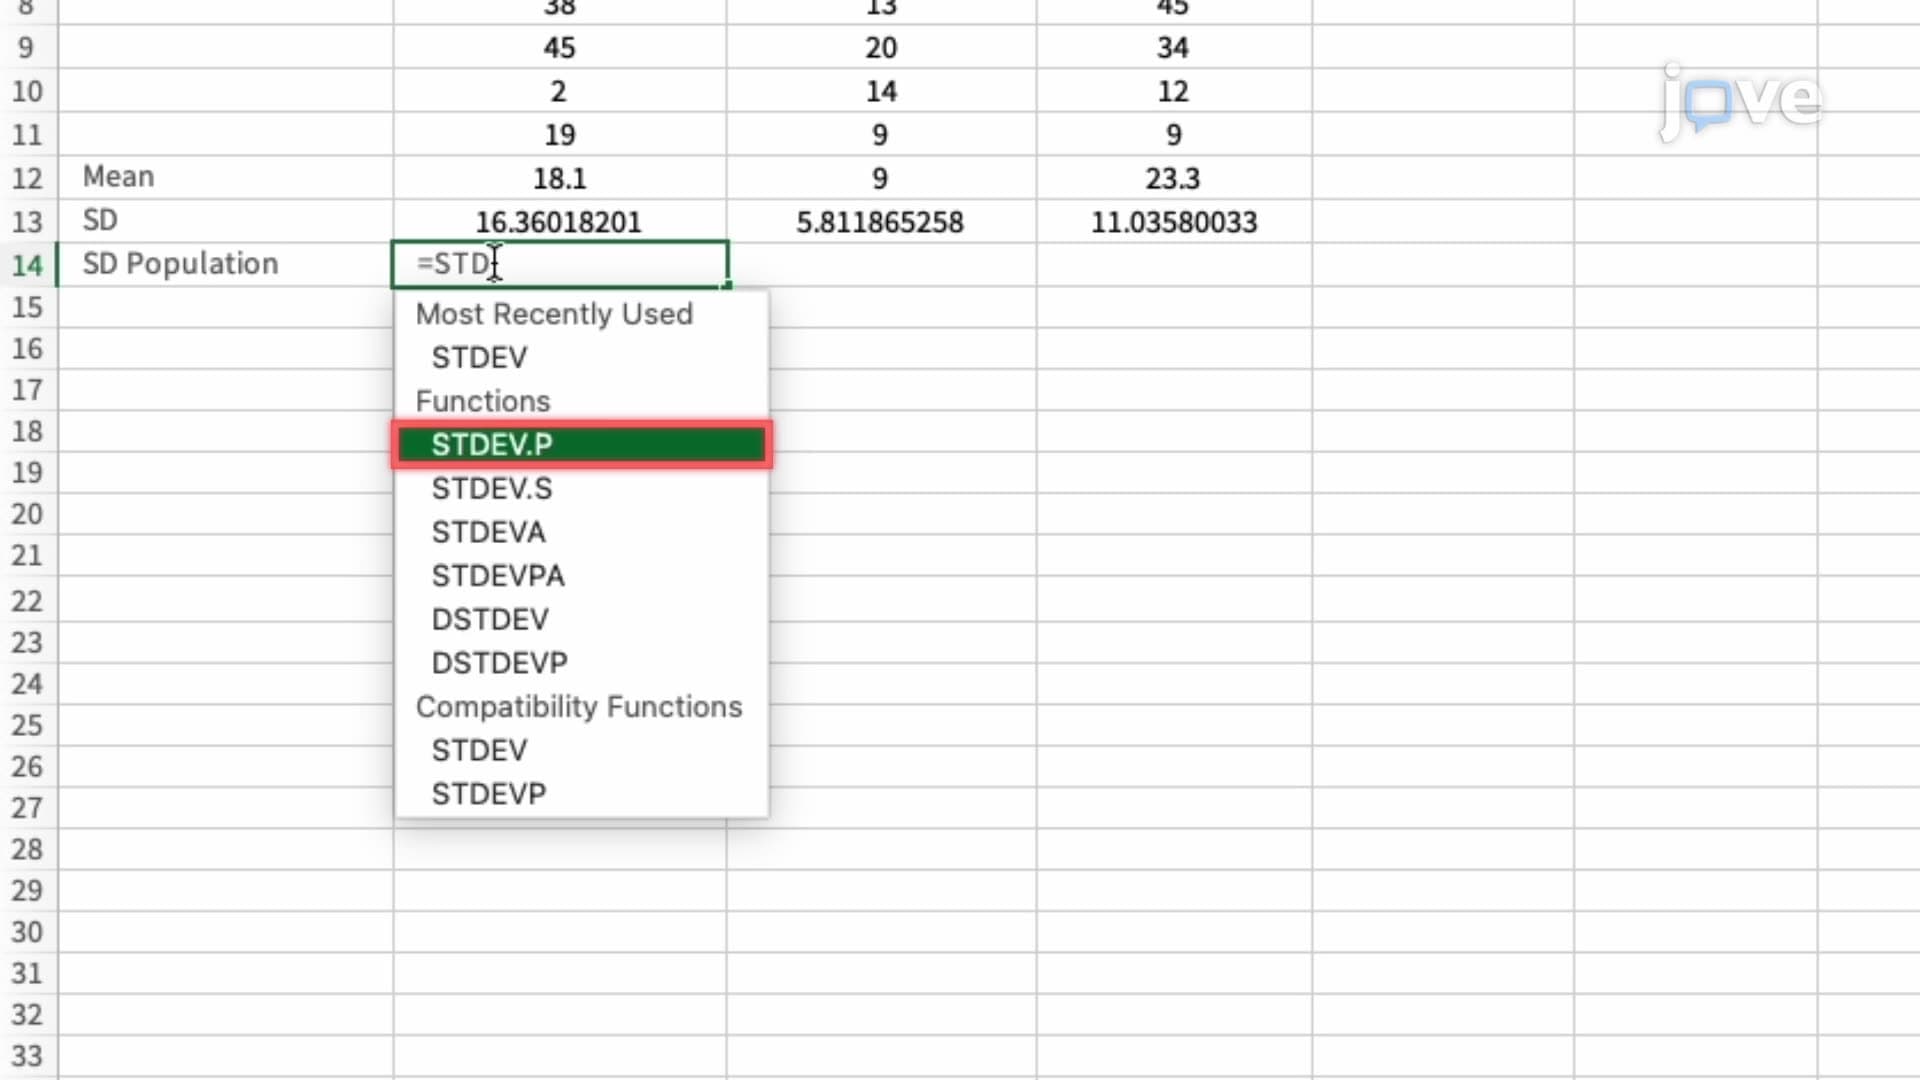
First, calculate the mean, SD, and SE of your data. The mean is obtained using the formula `=AVERAGE(range)`, while SD can be calculated with `=STDEV.P(range)` for a population or `=STDEV.S(range)` for a sample. SE is calculated as `=SD/SQRT(n)`, where `n` is the sample size.
To plot these values, use a bar...
 01:30
Coronary Artery Disease III: Clinical Manifestations
 01:26
Coronary Artery Disease IV: Preventive Measures