Related Experiment Video
Updated: Feb 8, 2026
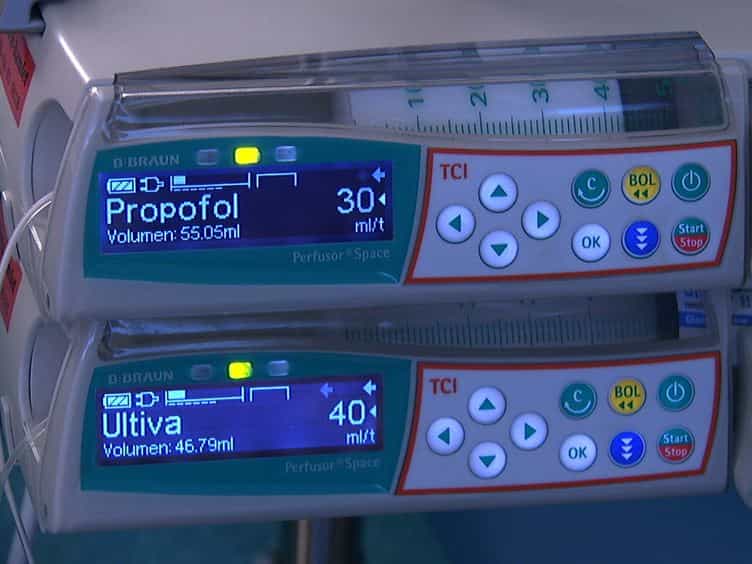

Deep Neuromuscular Blockade Leads to a Larger Intraabdominal Volume During Laparoscopy
Published on: June 25, 2013
Variation in Sedation and Neuromuscular Blockade Regimens on Outcome After Cardiac Arrest
Teresa L May1,2, Richard R Riker1, Gilles L Fraser1
1Department of Critical Care, Maine Medical Center, Portland, ME.

Objectives:
Sedation and neuromuscular blockade protocols in patients undergoing targeted temperature management after cardiac arrest address patient discomfort and manage shivering. These protocols vary widely between centers and may affect outcomes.
Design:
Consecutive patients admitted to 20 centers after resuscitation from cardiac arrest were prospectively entered into the International Cardiac Arrest Registry between 2006 and 2016. Additional data about each center's sedation and shivering management practice were obtained via survey. Sedation and shivering practices were categorized as escalating doses of sedation and minimal or no neuromuscular blockade (sedation and shivering practice 1), sedation with continuous or scheduled neuromuscular blockade (sedation and shivering practice 2), or sedation with as-needed neuromuscular blockade (sedation and shivering practice 3). Good outcome was defined as Cerebral Performance Category score of 1 or 2. A logistic regression hierarchical model was created with two levels (patient-level data with standard confounders at level 1 and hospitals at level 2) and sedation and shivering practices as a fixed effect at the hospital level. The primary outcome was dichotomized Cerebral Performance Category at 6 months.
Setting:
Cardiac arrest receiving centers in Europe and the United states from 2006 to 2016 PATIENTS:: Four-thousand two-hundred sixty-seven cardiac arrest patients 18 years old or older enrolled in the International Cardiac Arrest Registry.
Interventions:
None.
Measurements And Main Results:
The mean age was 62 ± 15 years, 36% were female, 77% out-of-hospital arrests, and mean ischemic time was 24 (± 18) minutes. Adjusted odds ratio (for age, return of spontaneous circulation, location of arrest, witnessed, initial rhythm, bystander cardiopulmonary resuscitation, defibrillation, medical history, country, and size of hospital) was 1.13 (0.74-1.73; p = 0.56) and 1.45 (1.00-2.13; p = 0.046) for sedation and shivering practice 2 and sedation and shivering practice 3, respectively, referenced to sedation and shivering practice 1.
Conclusion:
Cardiac arrest patients treated at centers using as-needed neuromuscular blockade had increased odds of good outcomes compared with centers using escalating sedation doses and avoidance of neuromuscular blockade, after adjusting for potential confounders. These findings should be further investigated in prospective studies.

Related Concept Videos
 01:29
Neuromuscular Junction And Blockade
 02:53
Conservative Site-specific Recombination and Phase Variation
The recognition sites for Cre recombinase called LoxP...
 01:14
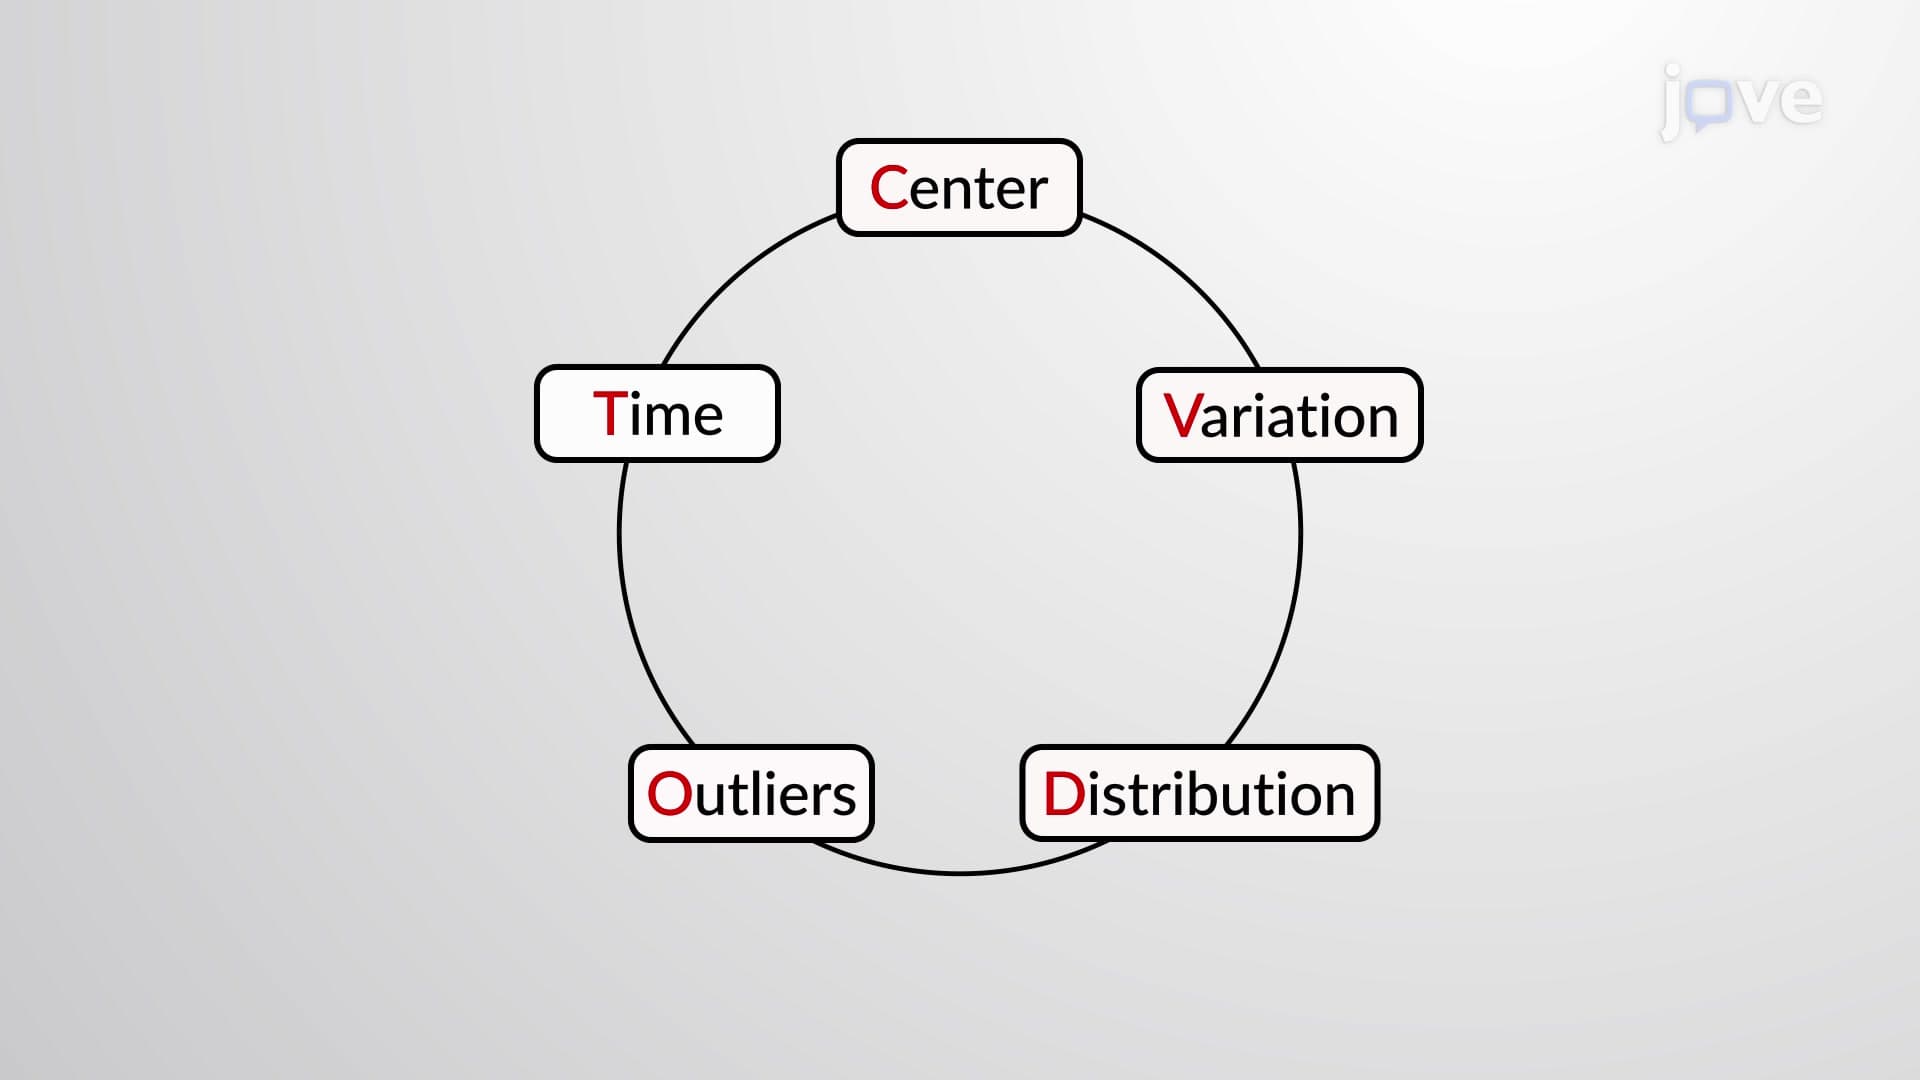
What is Variation?
The range, standard deviation, standard error, and variance are the different measures of variation.
Range: The range is the difference between its maximum and...
 01:23
Sedatives and Hypnotics: Overview
Sedative-hypnotics are categorized into barbiturates, benzodiazepines (BZDs), and non-benzodiazepines or Z-drugs. These drugs work by suppressing central nervous system activity, and this suppression is dose-dependent. Older sedative medications, like barbiturates, follow a linear curve in...
 01:19
Variation
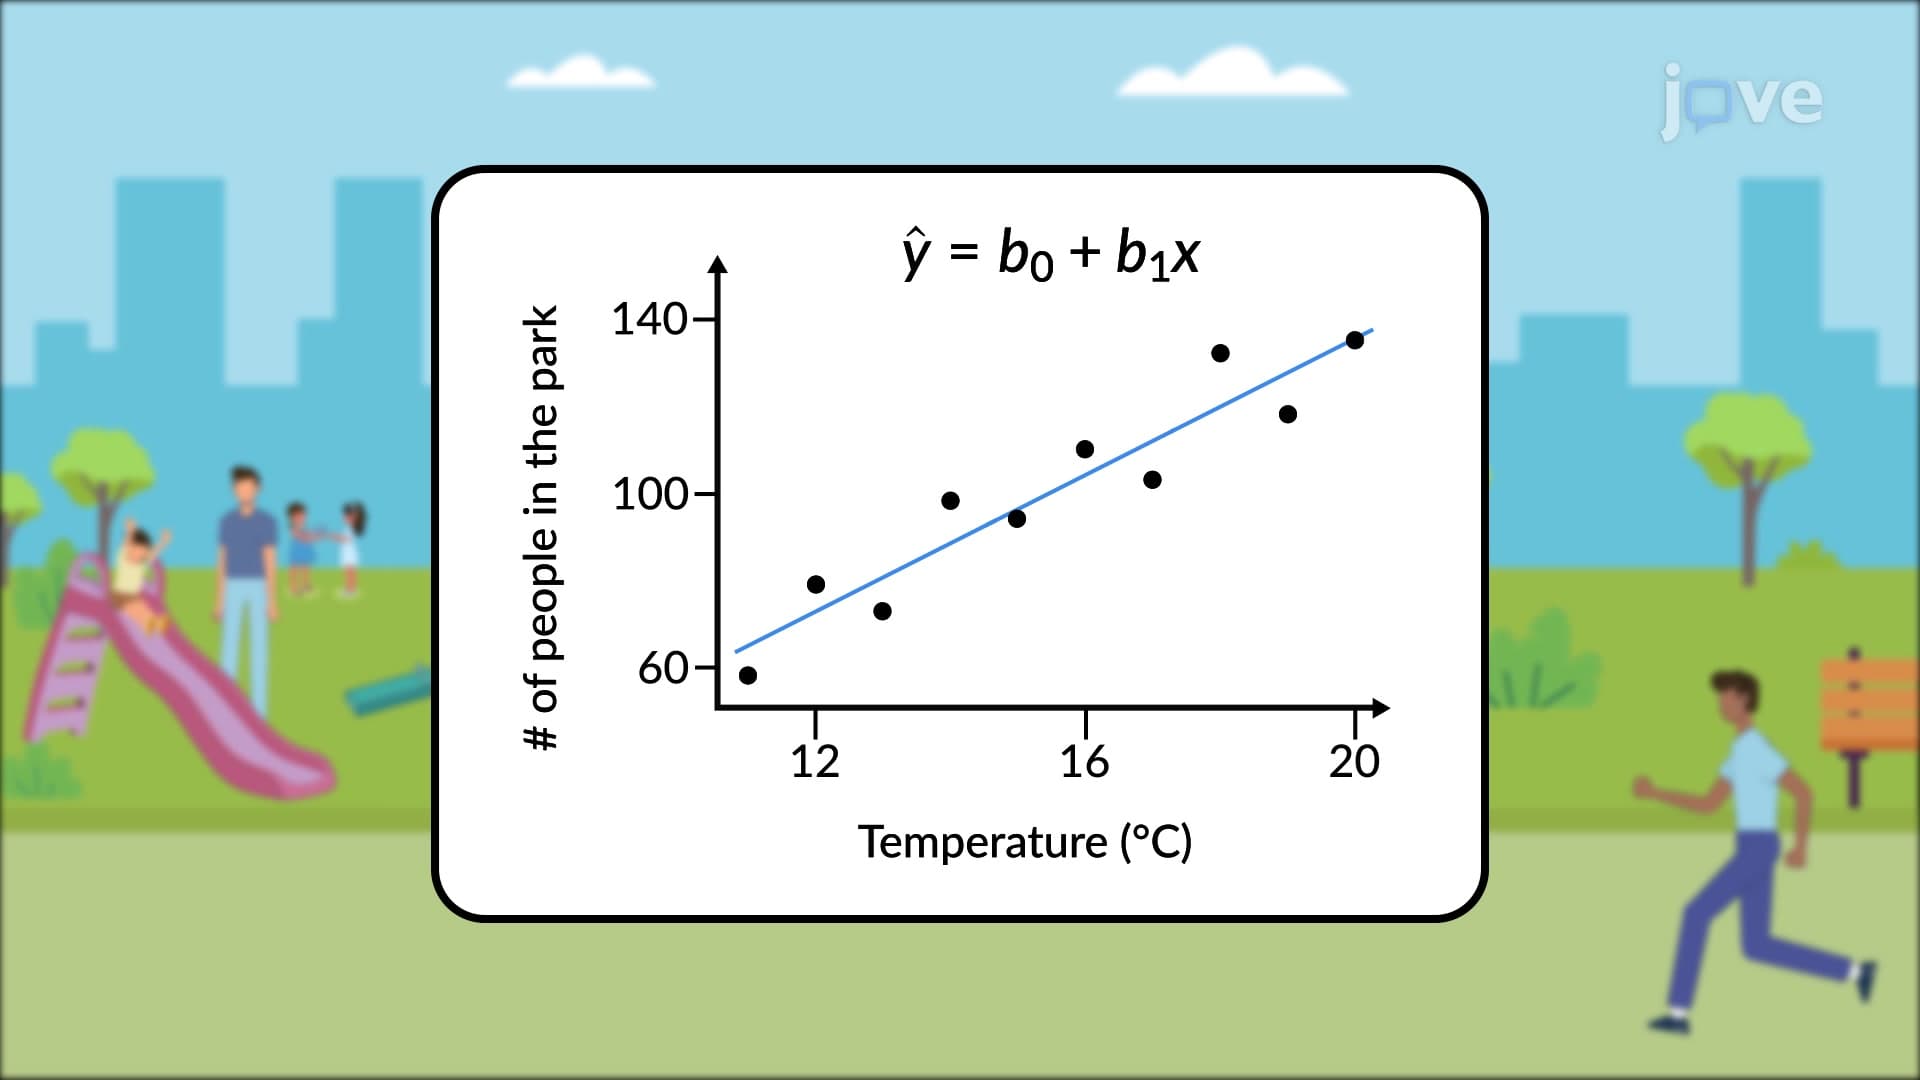
When independent and dependent variables are plotted on a scatter plot, the slope of a line is a value that describes the rate of change between the two...
 01:20
Sedatives and Hypnotics Drugs: Barbiturates