Related Experiment Video
Updated: Feb 8, 2026
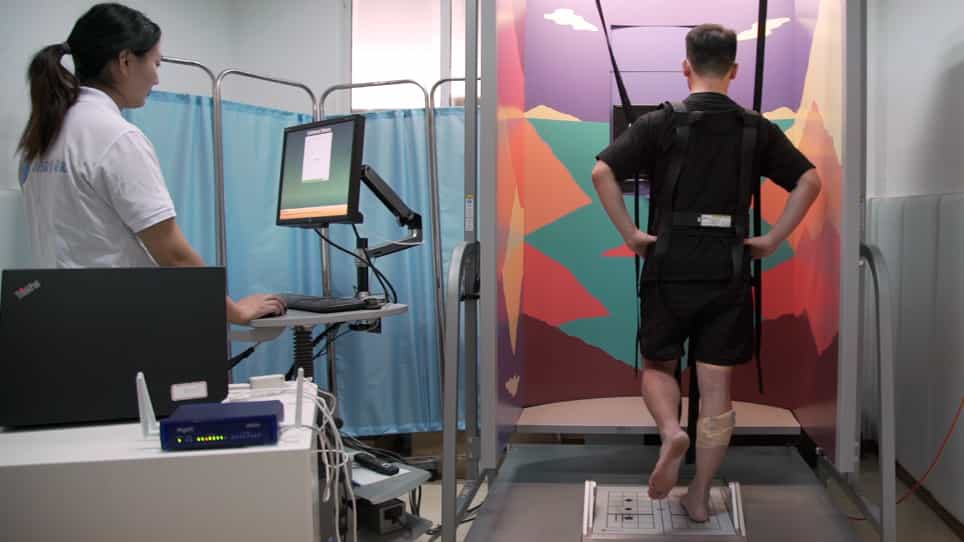
Evaluating Postural Control and Lower-extremity Muscle Activation in Individuals with Chronic Ankle Instability
Published on: September 18, 2020
Foot impairments contribute to functional limitation in individuals with ankle sprain and chronic ankle instability
John J Fraser1,2, Rachel M Koldenhoven3, Abbis H Jaffri3
1Department of Kinesiology, University of Virginia, 210 Emmet Street South, Charlottesville, VA, 22904-4407, USA. john.j.fraser8.mil@mail.mil.

Purpose:
To investigate the clinical measures of foot posture and morphology, multisegmented joint motion and play, strength, and dynamic balance in recreationally active young adults with and without a history of a lateral ankle sprain (LAS), copers, and chronic ankle instability (CAI).
Methods:
Eighty recreationally active individuals (healthy: n = 22, coper: n = 21, LAS: n = 17, CAI: n = 20) were included. Foot posture index (FPI), morphologic measures, joint motion (weight-bearing dorsiflexion (WBDF), rearfoot dorsiflexion, plantar flexion, inversion, eversion; forefoot inversion, eversion; hallux flexion, extension), joint play (proximal and distal tibiofibular; talocrural and subtalar, forefoot; 1st tarsometatarsal and metatarsophalangeal), strength (dorsiflexion, plantar flexion, inversion, eversion, hallux flexion, lesser toe flexion), and Star Excursion Balance Test (SEBT) (anterior, posteromedial, posterolateral) were assessed.
Results:
There were no group differences in FPI or morphological measures. LAS and CAI groups had decreased ankle dorsiflexion (p = 0.001) and greater frontal plane motion (p < 0.001), first MT plantar flexion, and sagittal excursion (p < 0.001); increased talocrural glide (p = 0.02) and internal rotation (p < 0.001) and decreased forefoot inversion joint play (p < 0.001); and decreased strength in all measures (p < 0.001) except dorsiflexion compared to healthy controls. The LAS group also demonstrated decreased distal tibiofibular (p = 0.04) and forefoot general laxity (p = 0.05) and SEBT performance (anterior: p = 0.02; posteromedial: p < 0.001; posterolateral: p < 0.001).
Conclusion:
Individuals with LAS or CAI have increased pain, impaired physiologic and accessory joint motion, ligamentous tenderness, and strength in the foot and ankle. Clinicians should assess the multiple segments of the ankle-foot complex when caring for individuals with an LAS or CAI.
Level Of Evidence:
II.

Related Concept Videos
 01:10
Ankle Joint
 01:25
Limits on Trigonometric Functions
 02:17
Microtubule Instability
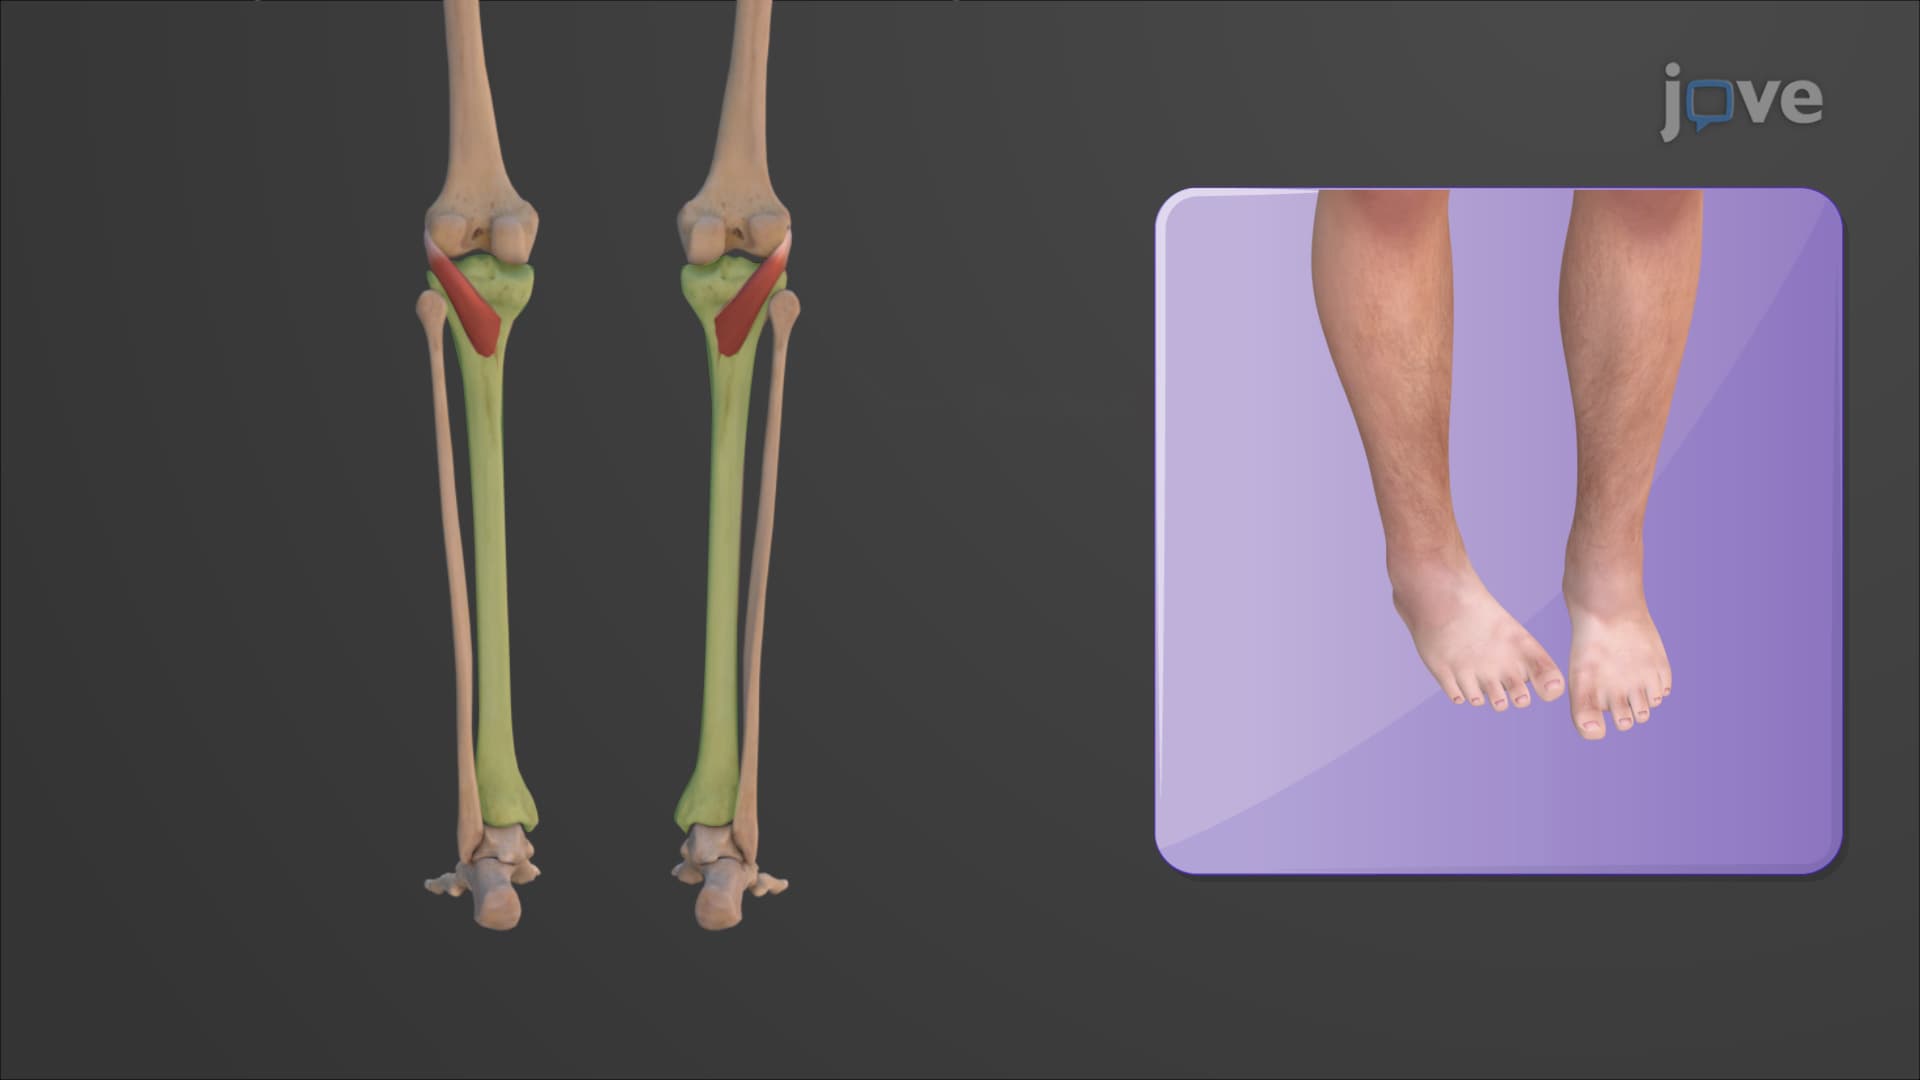 01:28
Muscles of the Leg that Move the Foot and Toes
Anterior Compartment
The anterior compartment includes muscles that contribute to the dorsiflexion of the foot. This compartment houses the tibialis anterior, extensor hallucis longus, and extensor digitorum longus muscles....
 02:27
Limiting Reactant
 01:23
Binet's Contribution to Measures of Intelligence