Related Experiment Video
Updated: Feb 8, 2026


Dynamic Multiparameter Platelet Function Assessment Using a Capacitive Biosensor
Published on: May 2, 2025
Comparison of nine platelet function tests used to determine responses to different aspirin dosages in people with
Paul Harrison1, M Angelyn Bethel2, Irene Kennedy2,3
1a Institute of Inflammation and Ageing , University of Birmingham Medical School , Birmingham , UK.

Abstract:
The antiplatelet efficacy of aspirin (ASA) is reduced in type 2 diabetes (T2D). As the best ex vivo method of measuring ASA efficacy remains uncertain, we compared nine platelet function tests to assess responsiveness to three ASA dosing regimens in 24 T2D patients randomized in a three-treatment crossover design to ASA 100 mg/day, 200 mg/day, or 100 mg twice daily for 2-week treatment periods. Platelet function tests compared were as follows: light transmission aggregometry (LTA)-0.5 mg/mL of arachidonic acid (AA) and 10 µM adenosine diphosphate (ADP); multiplate whole blood aggregometry (WBA)-0.5 mM AA and 6.5 µM ADP; platelet function analyzer (PFA)-100™-collagen and ADP (CADP) and collagen and epinephrine (CEPI); VerifyNow™-ASA; and urinary 11-dehydro-thromboxane B2 (TxB2) and serum TxB2. All cyclo-oxygenase (COX-1)-dependent tests and some COX-1-independent tests (PFA-CEPI, LTA-ADP) demonstrated significant reductions in platelet reactivity with all ASA doses. Two COX-1-independent tests (WBA-ADP and PFA-CADP) showed no overall reduction in platelet reactivity. Overall classifications for detecting all ASA doses, compared to baseline, were as follows: very good-LTA-AA (k = 0.95) and VerifyNow™-ASA (k = 0.85); good-serum TxB2 (k = 0.79); moderate-LTA-ADP (k = 0.59), PFA-100™-CEPI (k = 0.56), urinary TxB2 (k = 0.55), WBA-AA (k = 0.47); and poor-PFA-100™-CADP (k = -0.02) and WBA-ADP (k = -0.07). No significant kappa statistic differences were seen for each test for each ASA dose. Correlations for each test with serum TxB2 measurements were as follows: very good-VerifyNow™-ASA (k = 0.81, R2 = 0.56) and LTA-AA (k = 0.85, R2 = 0.65); good-PFA-100TM-CEPI (k = 0.62, R2 = 0.30); moderate-urinary TxB2 (k = 0.57, R2 = 0.51) and LTA-ADP (k = 0.47, R2 = 0.56); fair-WBA-AA (k = 0.31, R2 = 0.31); and poor-PFA-100™-CADP (k = 0.04, R2 = 0.003) and WBA-ADP (k = -0.04, R2 = 0.0005). The platelet function tests we assessed were not equally effective in measuring the antiplatelet effect of ASA and correlated poorly amongst themselves, but COX-1-dependent tests performed better than non-COX-1-dependent tests.
More Related Videos
 11:31
High-Efficiency Generation of Antigen-Specific Primary Mouse Cytotoxic T Cells for Functional Testing in an Autoimmune Diabetes Model
Published on: August 16, 2019
 07:41
Behavioral Assessment of Visual Function via Optomotor Response and Cognitive Function via Y-Maze in Diabetic Rats
Published on: October 23, 2020
Related Concept Videos
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:13
Multiple Comparison Tests
It would be easy to compare two samples using a significance alpha level of 0.05. In other words, there is only one sample pair to be compared. However, it would be difficult to identify a significantly different sample if the number...
 01:18
Structure and Function of Platelets
Platelets are continually replenished, circulating in the bloodstream for 9-12 days before being removed by phagocytes, primarily in the spleen. A microliter of circulating blood contains between 150,000 and 450,000...
 01:19
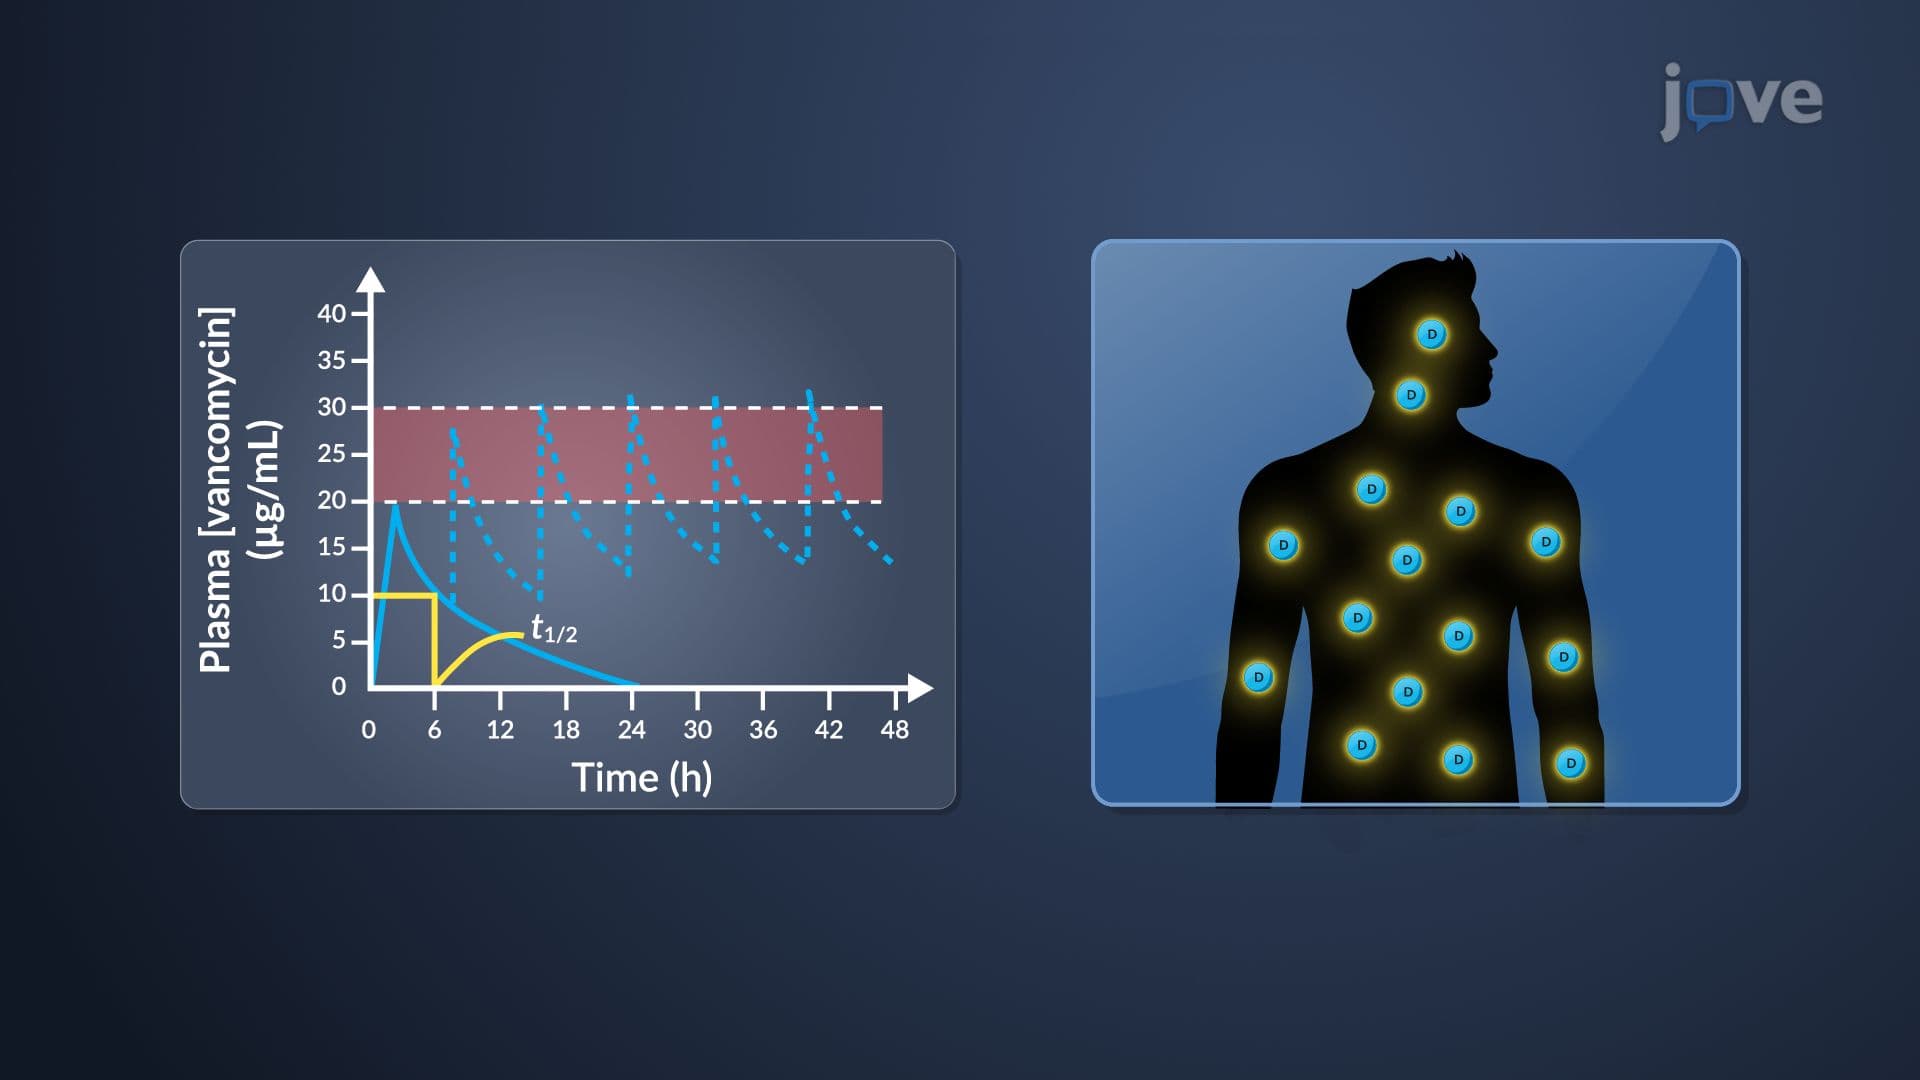
Dosage Interval and Administration Route: Determination Methods
 02:57
The Sense of Self: Reflected Self-Appraisal and Social Comparison
 01:26
Types of Functions I